Chapter 7: Human Health and Disease
In the late 1890s, a British army doctor named Ronald Ross was working in India, determined to solve a mystery that had puzzled people for centuries: what actually caused malaria? For a long time, many believed the disease came from “bad air” rising off marshes — in fact, the word malaria itself comes from the Italian for “bad air.” Ross suspected something different. He had a hunch that mosquitoes were involved, and he spent long, frustrating months dissecting the insects under a microscope in the heat, examining their stomachs one by one.
Then came the breakthrough. Inside the gut of a particular mosquito that had fed on a malaria patient’s blood, Ross found tiny developing forms of the malarial parasite. Here was proof that the parasite lived and grew inside the mosquito, and that the insect carried it from one person to the next. Malaria was not caused by foul air at all — it was a living parasite passed on by a mosquito bite.
That single observation changed public health forever. If you know how a disease spreads, you know how to stop it: drain the stagnant water, use nets, control the mosquito. Ross’s work marks a turning point in this chapter’s central idea — that understanding a disease at the level of its cause is the first step to defeating it.
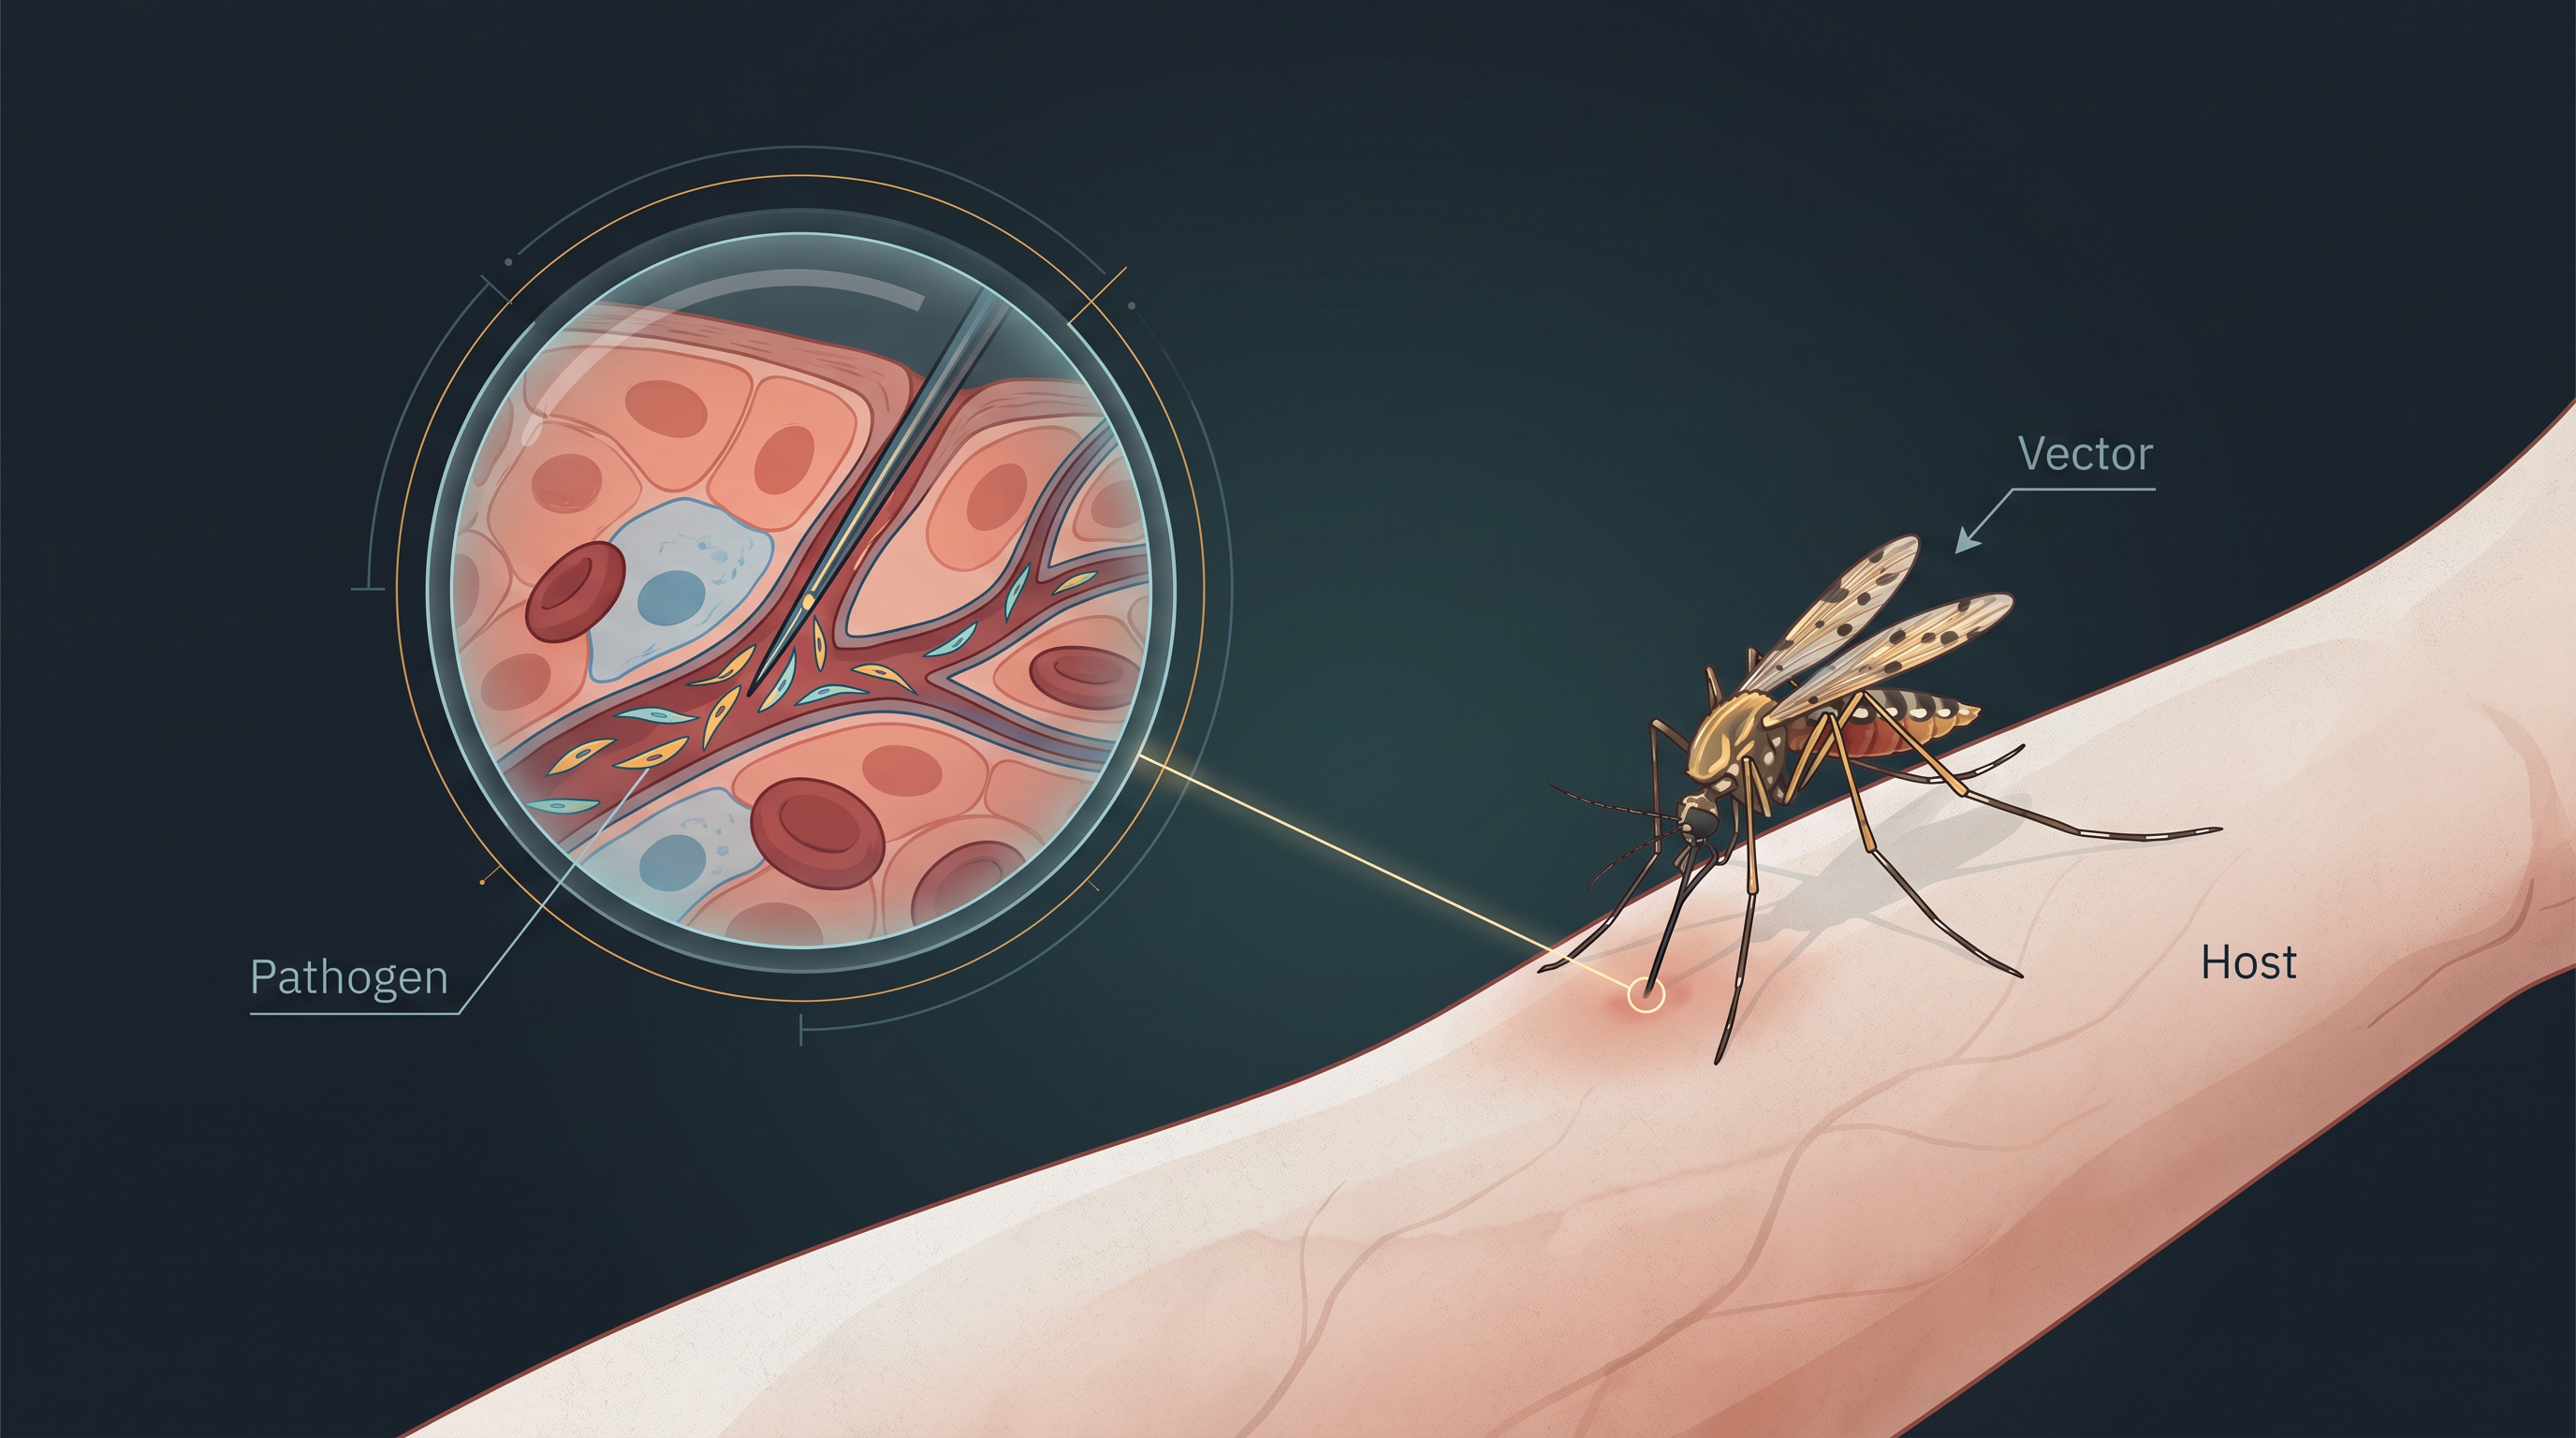
Fig. 7.0 – The mosquito as a vector for pathogens.
By the end of this chapter, you will be able to answer each of these questions yourself.
7.1 Common Diseases in Humans
Before we look at the diseases that trouble us, it helps to be clear about what “health” actually is and how disease is the opposite side of the same coin. This section first defines health and the two broad kinds of disease, and then introduces the common infectious diseases of humans, the organisms that cause them, and how we can prevent them.
What Health Really Means
We use the word health almost every day, but defining it is not as simple as it sounds. Health does not merely mean the “absence of disease,” nor does it only mean “physical fitness.” It is much broader than either of these.
Health is best understood as a state of complete physical, mental and social well-being. In other words, a truly healthy person is not just free of illness but is also emotionally stable and able to live and work comfortably within society.
Good health matters far beyond the individual. When people are healthy, they work more efficiently, which raises productivity and brings economic prosperity to a community. Good health also increases how long people live (longevity) and lowers the number of deaths among infants and mothers.
Habits and Measures That Protect Health
Certain everyday habits keep the body in good working order. A balanced diet, personal hygiene (keeping oneself clean), and regular exercise are all essential for maintaining good health. Yoga, practised in India since ancient times, has long been used to achieve both physical and mental health.
Health also depends on measures taken at the level of the whole community, not just the individual. Awareness about diseases and how they affect the body, vaccination (immunisation) against infectious diseases, proper disposal of wastes, control of vectors (disease-carrying organisms such as mosquitoes), and maintaining hygiene in our food and water supplies are all necessary for good health.
It is also worth remembering that the mind and the body are linked. Biology has shown that mental state can influence the immune system through the nervous and endocrine (hormone-producing) systems. This is why a calm, positive mind supports better health, while prolonged stress can weaken our defences.
Finally, health is affected by three broad factors: genetic disorders (deficiencies a child is born with or inherits from the parents), infections, and lifestyle (the food and water we take, the rest and exercise we allow our bodies, and the habits we keep or lack).
Two Broad Kinds of Disease
When the working of one or more organs or organ systems of the body is disturbed — shown by the appearance of various signs and symptoms — we say the person is not healthy, that is, the person has a disease.
Diseases are broadly grouped into two kinds: infectious and non-infectious. Diseases that spread easily from one person to another are called infectious diseases. These are extremely common, and every one of us falls ill with one or another at some point. Some infectious diseases, such as AIDS, can be fatal.
Non-infectious diseases do not spread from person to person. Among these, cancer is the leading cause of death. Drug and alcohol abuse, discussed later in this chapter, also harms our health seriously even though it is not an “infection.”
Pathogens: The Cause of Infectious Diseases
A wide range of organisms — belonging to bacteria, viruses, fungi, protozoans and helminths (parasitic worms) — can cause disease in humans. Any disease-causing organism is called a pathogen.
Most parasites are therefore pathogens, because they harm the host (the organism they live in or on) by feeding at its expense. Pathogens enter our body by various routes, multiply inside us, and interfere with our normal vital activities, resulting in both morphological (structural) and functional damage.
To survive, a pathogen must be adapted to the specific environment inside its host. For example, pathogens that infect the gut must be able to survive the low pH (high acidity) of the stomach and resist the various digestive enzymes waiting to break them down.
In the pages that follow, we meet representative pathogens from each major group, the disease each causes, and how these diseases can be prevented and controlled.
Flowchart
FC 7.1 – How a pathogen causes disease: pathogen enters body → survives host environment (e.g., low pH, enzymes) → multiplies → interferes with normal functions → morphological and functional damage → signs and symptoms (disease)
Bacterial Diseases
Salmonella typhi is a bacterium that causes typhoid fever in humans. These bacteria usually enter the small intestine through food and water contaminated with them, and from there migrate to other organs through the blood.
The typical signs of typhoid are a sustained high fever (39°C to 40°C), weakness, stomach pain, constipation, headache and loss of appetite. In severe cases, the intestine may be perforated (punctured), and death can occur. Typhoid is confirmed in the laboratory by the Widal test.
Pneumonia is another bacterial disease, caused by bacteria such as Streptococcus pneumoniae and Haemophilus influenzae. It infects the alveoli — the tiny air-filled sacs of the lungs where gas exchange happens. When the alveoli become filled with fluid due to the infection, breathing becomes very difficult.
The symptoms of pneumonia include fever, chills, cough and headache. In severe cases, the lips and finger nails may turn gray to bluish in colour because the blood is not getting enough oxygen. A healthy person catches pneumonia by inhaling the droplets or aerosols released by an infected person, or even by sharing glasses and utensils with them. Dysentery, plague and diphtheria are some other bacterial diseases of humans.
Protozoan Diseases
Some human diseases are caused by protozoans — single-celled organisms. Malaria is the disease people have battled for centuries. It is caused by Plasmodium, a tiny protozoan.
Different species of Plasmodium (P. vivax, P. malariae and P. falciparum) cause different types of malaria. Of these, the malignant malaria caused by Plasmodium falciparum is the most serious and can even be fatal.
Let us follow the life cycle of Plasmodium (Fig. 7.1). The parasite enters the human body as sporozoites — the infectious form — through the bite of an infected female Anopheles mosquito. Inside the human, the parasites first multiply within the liver cells, and then attack the red blood cells (RBCs), causing them to rupture.
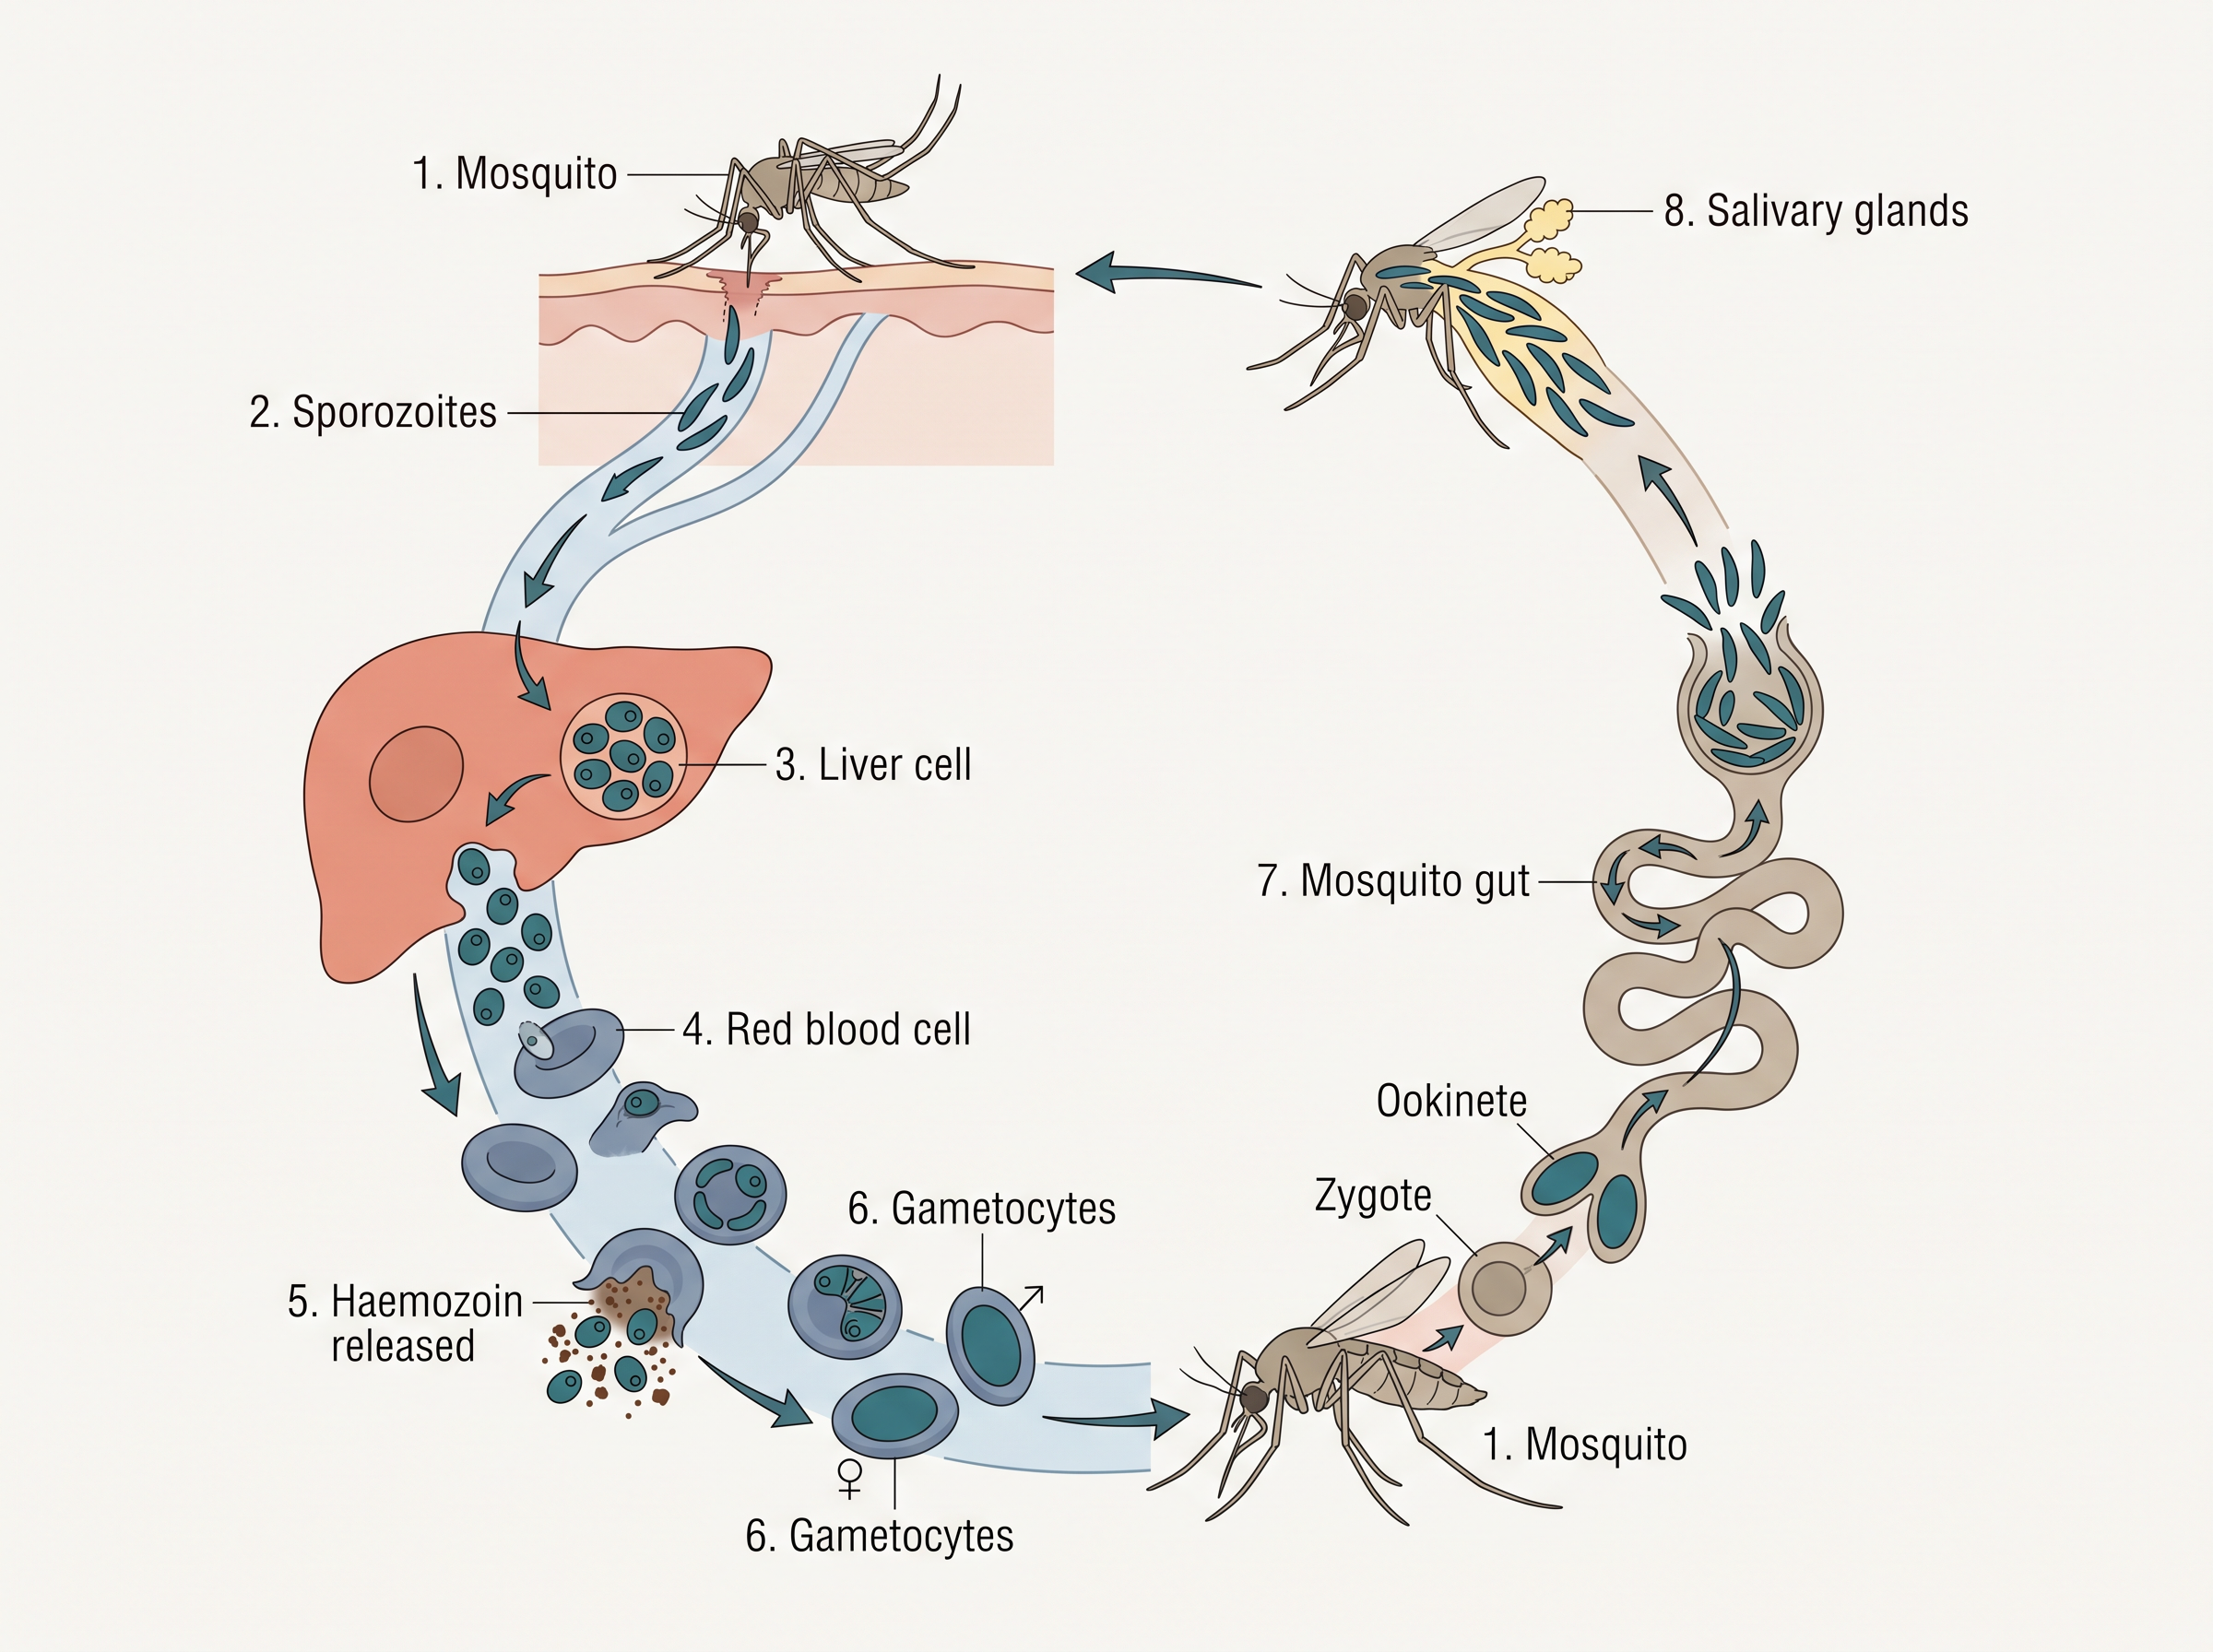
Fig. 7.1 – Life cycle of Plasmodium.
The bursting of the RBCs releases a toxic substance called haemozoin. This toxin is responsible for the chill and high fever that recur every three to four days — a hallmark of malaria.
The cycle continues when a female Anopheles mosquito bites the infected person: the parasites enter the mosquito’s body and develop further. Inside the mosquito they multiply to form sporozoites, which are stored in its salivary glands. When this mosquito bites another human, the sporozoites are injected, and the whole set of events begins again.
Notice that the malarial parasite needs two hosts — a human and a mosquito — to complete its life cycle. The female Anopheles mosquito is not just a host but also the vector, the agent that transmits the parasite from one human to another.
Another protozoan disease is amoebiasis, also called amoebic dysentery, caused by Entamoeba histolytica, a parasite that lives in the large intestine. Its symptoms include constipation, abdominal pain and cramps, and stools containing excess mucous and blood clots.
Here, houseflies act as mechanical carriers: they pick up the parasite from the faeces of an infected person and deposit it on food and food products, contaminating them. Drinking water and food contaminated with faecal matter are the main sources of infection.
Helminth (Worm) Diseases
Helminths are parasitic worms. Ascaris, the common round worm, and Wuchereria, the filarial worm, are two helminths that are pathogenic to humans.
Ascaris, an intestinal parasite, causes ascariasis. Its symptoms include internal bleeding, muscular pain, fever, anemia (a shortage of healthy red blood cells) and blockage of the intestinal passage. The eggs of the parasite pass out with the faeces of infected people and contaminate soil, water and plants. A healthy person picks up the infection through contaminated water, vegetables and fruits.
Wuchereria (the species W. bancrofti and W. malayi) are filarial worms that cause a slowly developing, chronic (long-lasting) inflammation of the organs in which they live for many years — usually the lymphatic vessels of the lower limbs. This disease is called elephantiasis or filariasis (Fig. 7.2), because the affected limb swells enormously. The genital organs are also often affected, leading to gross deformities. These worms are passed to a healthy person through the bite of female mosquito vectors.
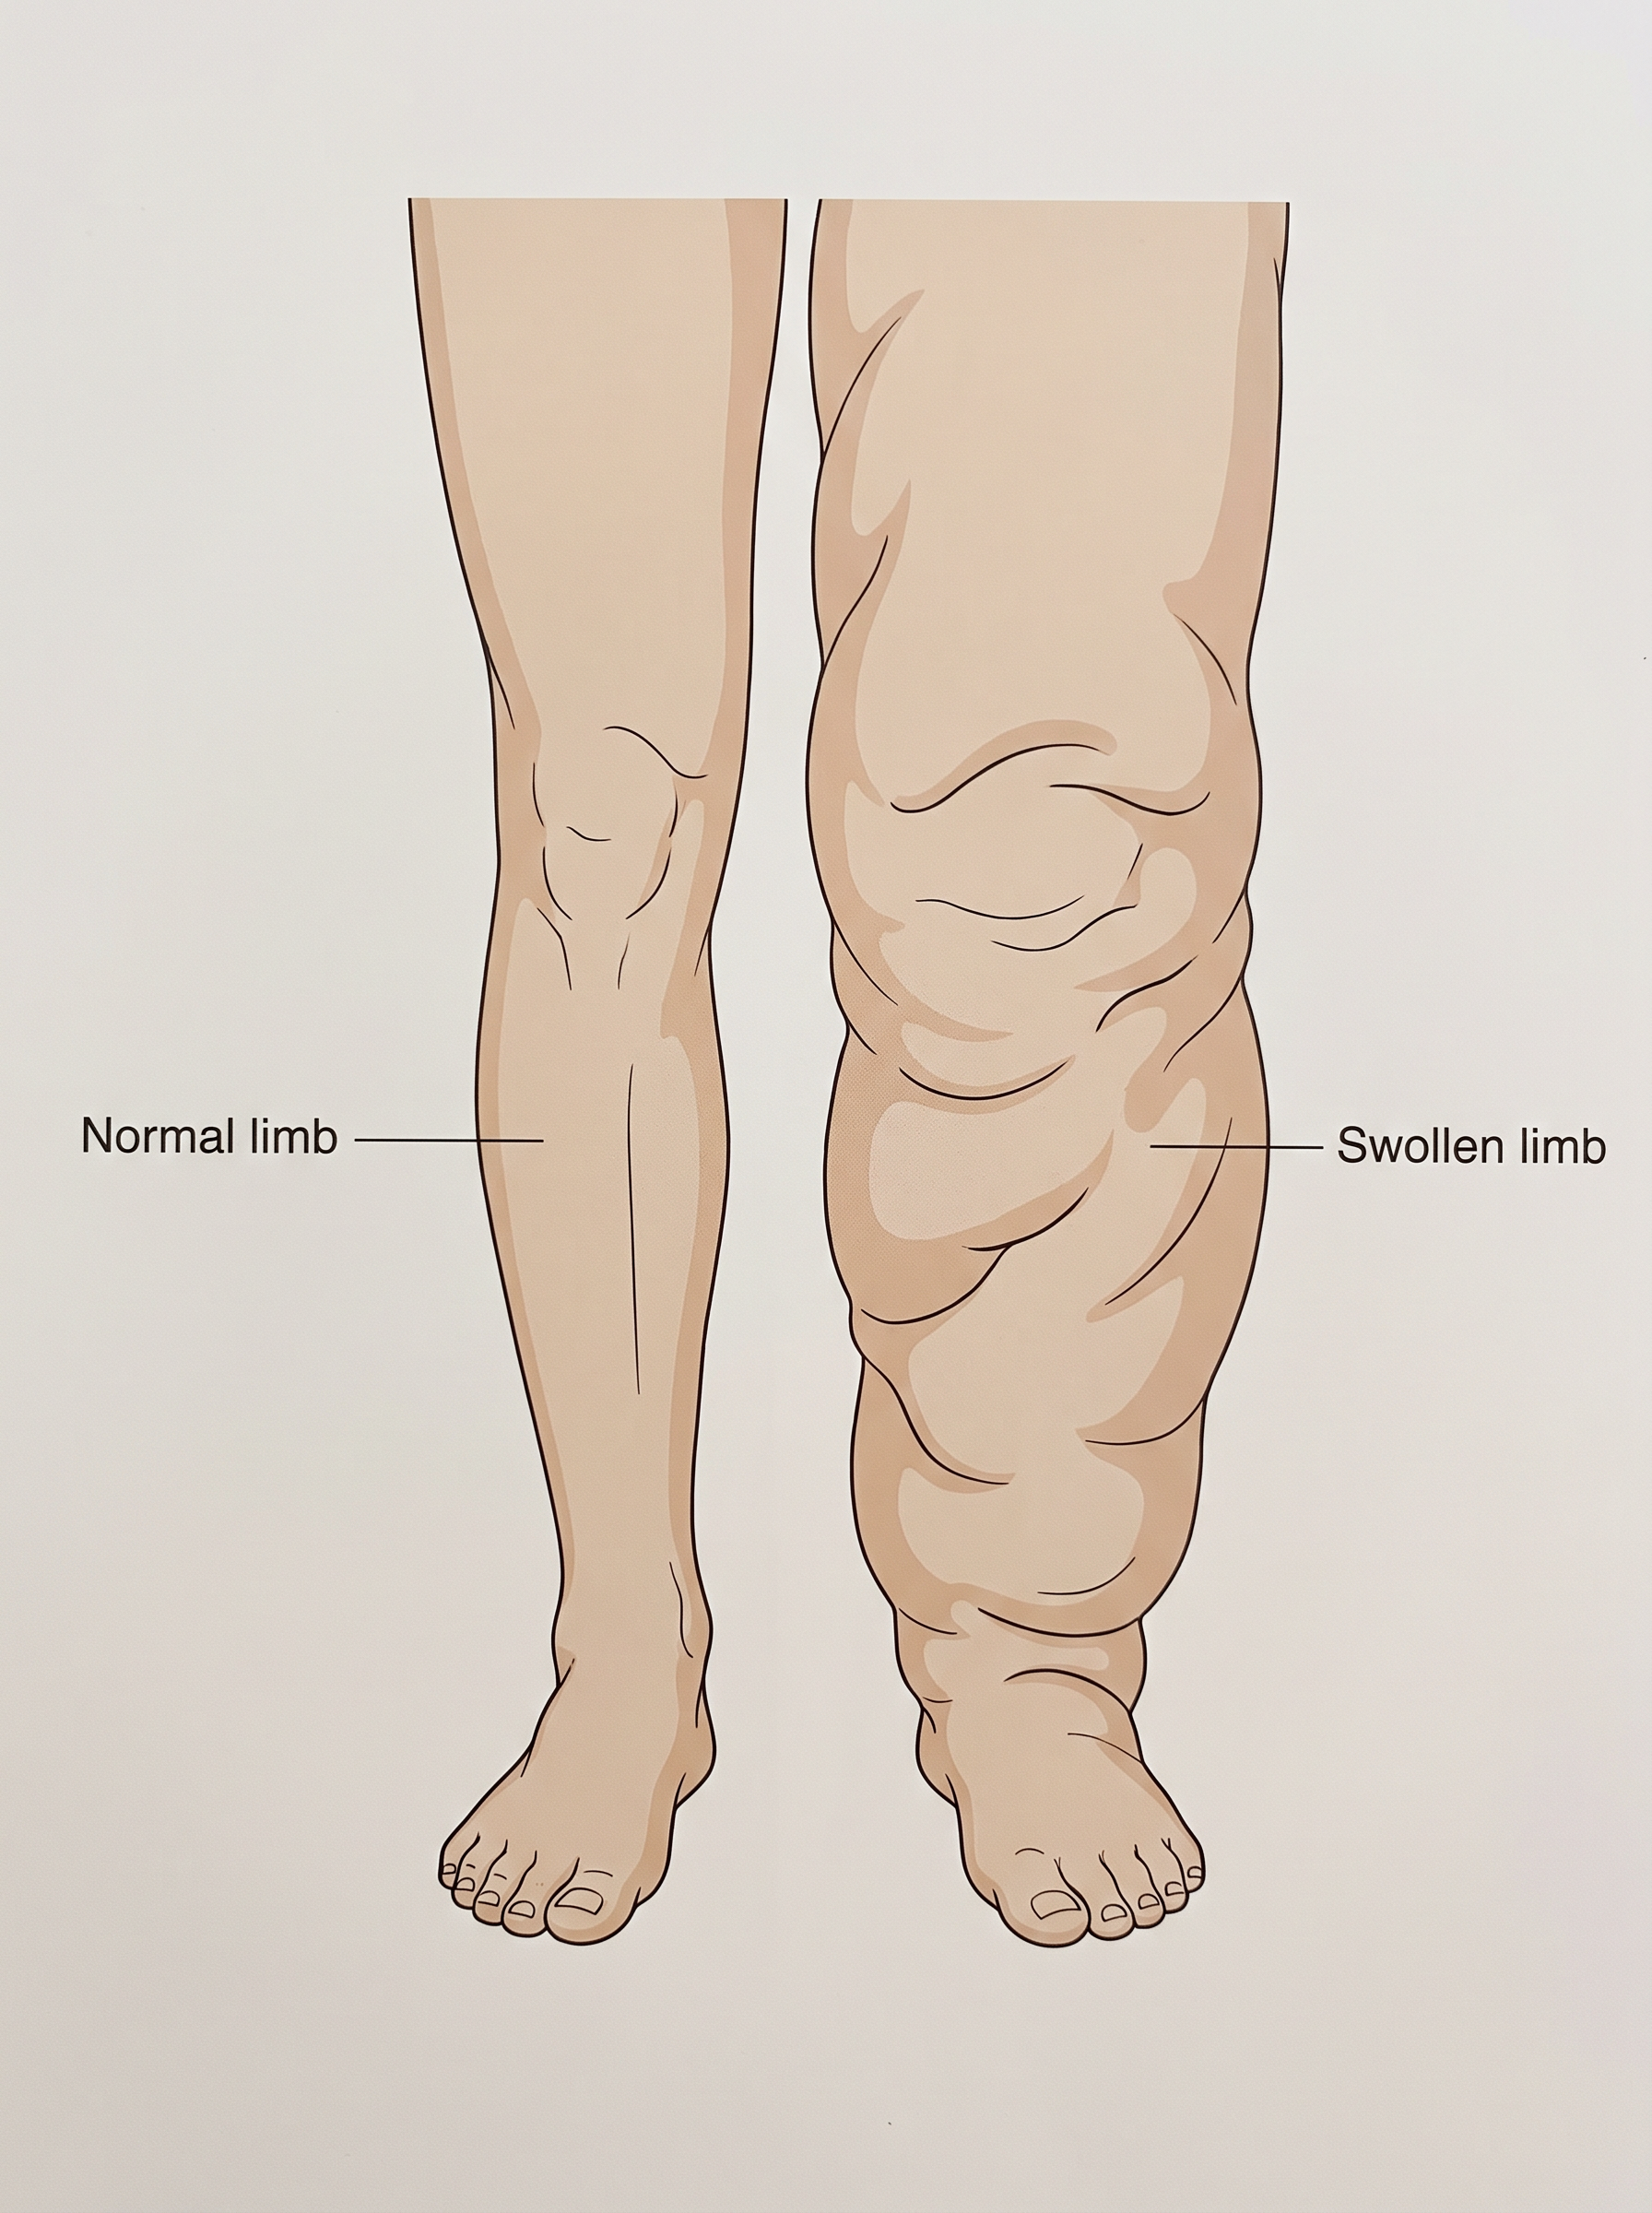
Fig. 7.2 – Lower limb inflammation in elephantiasis.
Fungal Diseases
Several fungi belonging to the genera Microsporum, Trichophyton and Epidermophyton cause ringworms, among the most common of all infectious diseases in humans.
The main symptoms are dry, scaly lesions on various parts of the body such as the skin, nails and scalp (Fig. 7.3), accompanied by intense itching. Heat and moisture help these fungi to grow, so they thrive in skin folds such as those in the groin or between the toes. Ringworms are usually acquired from soil, or by using the towels, clothes or even the comb of an infected person.
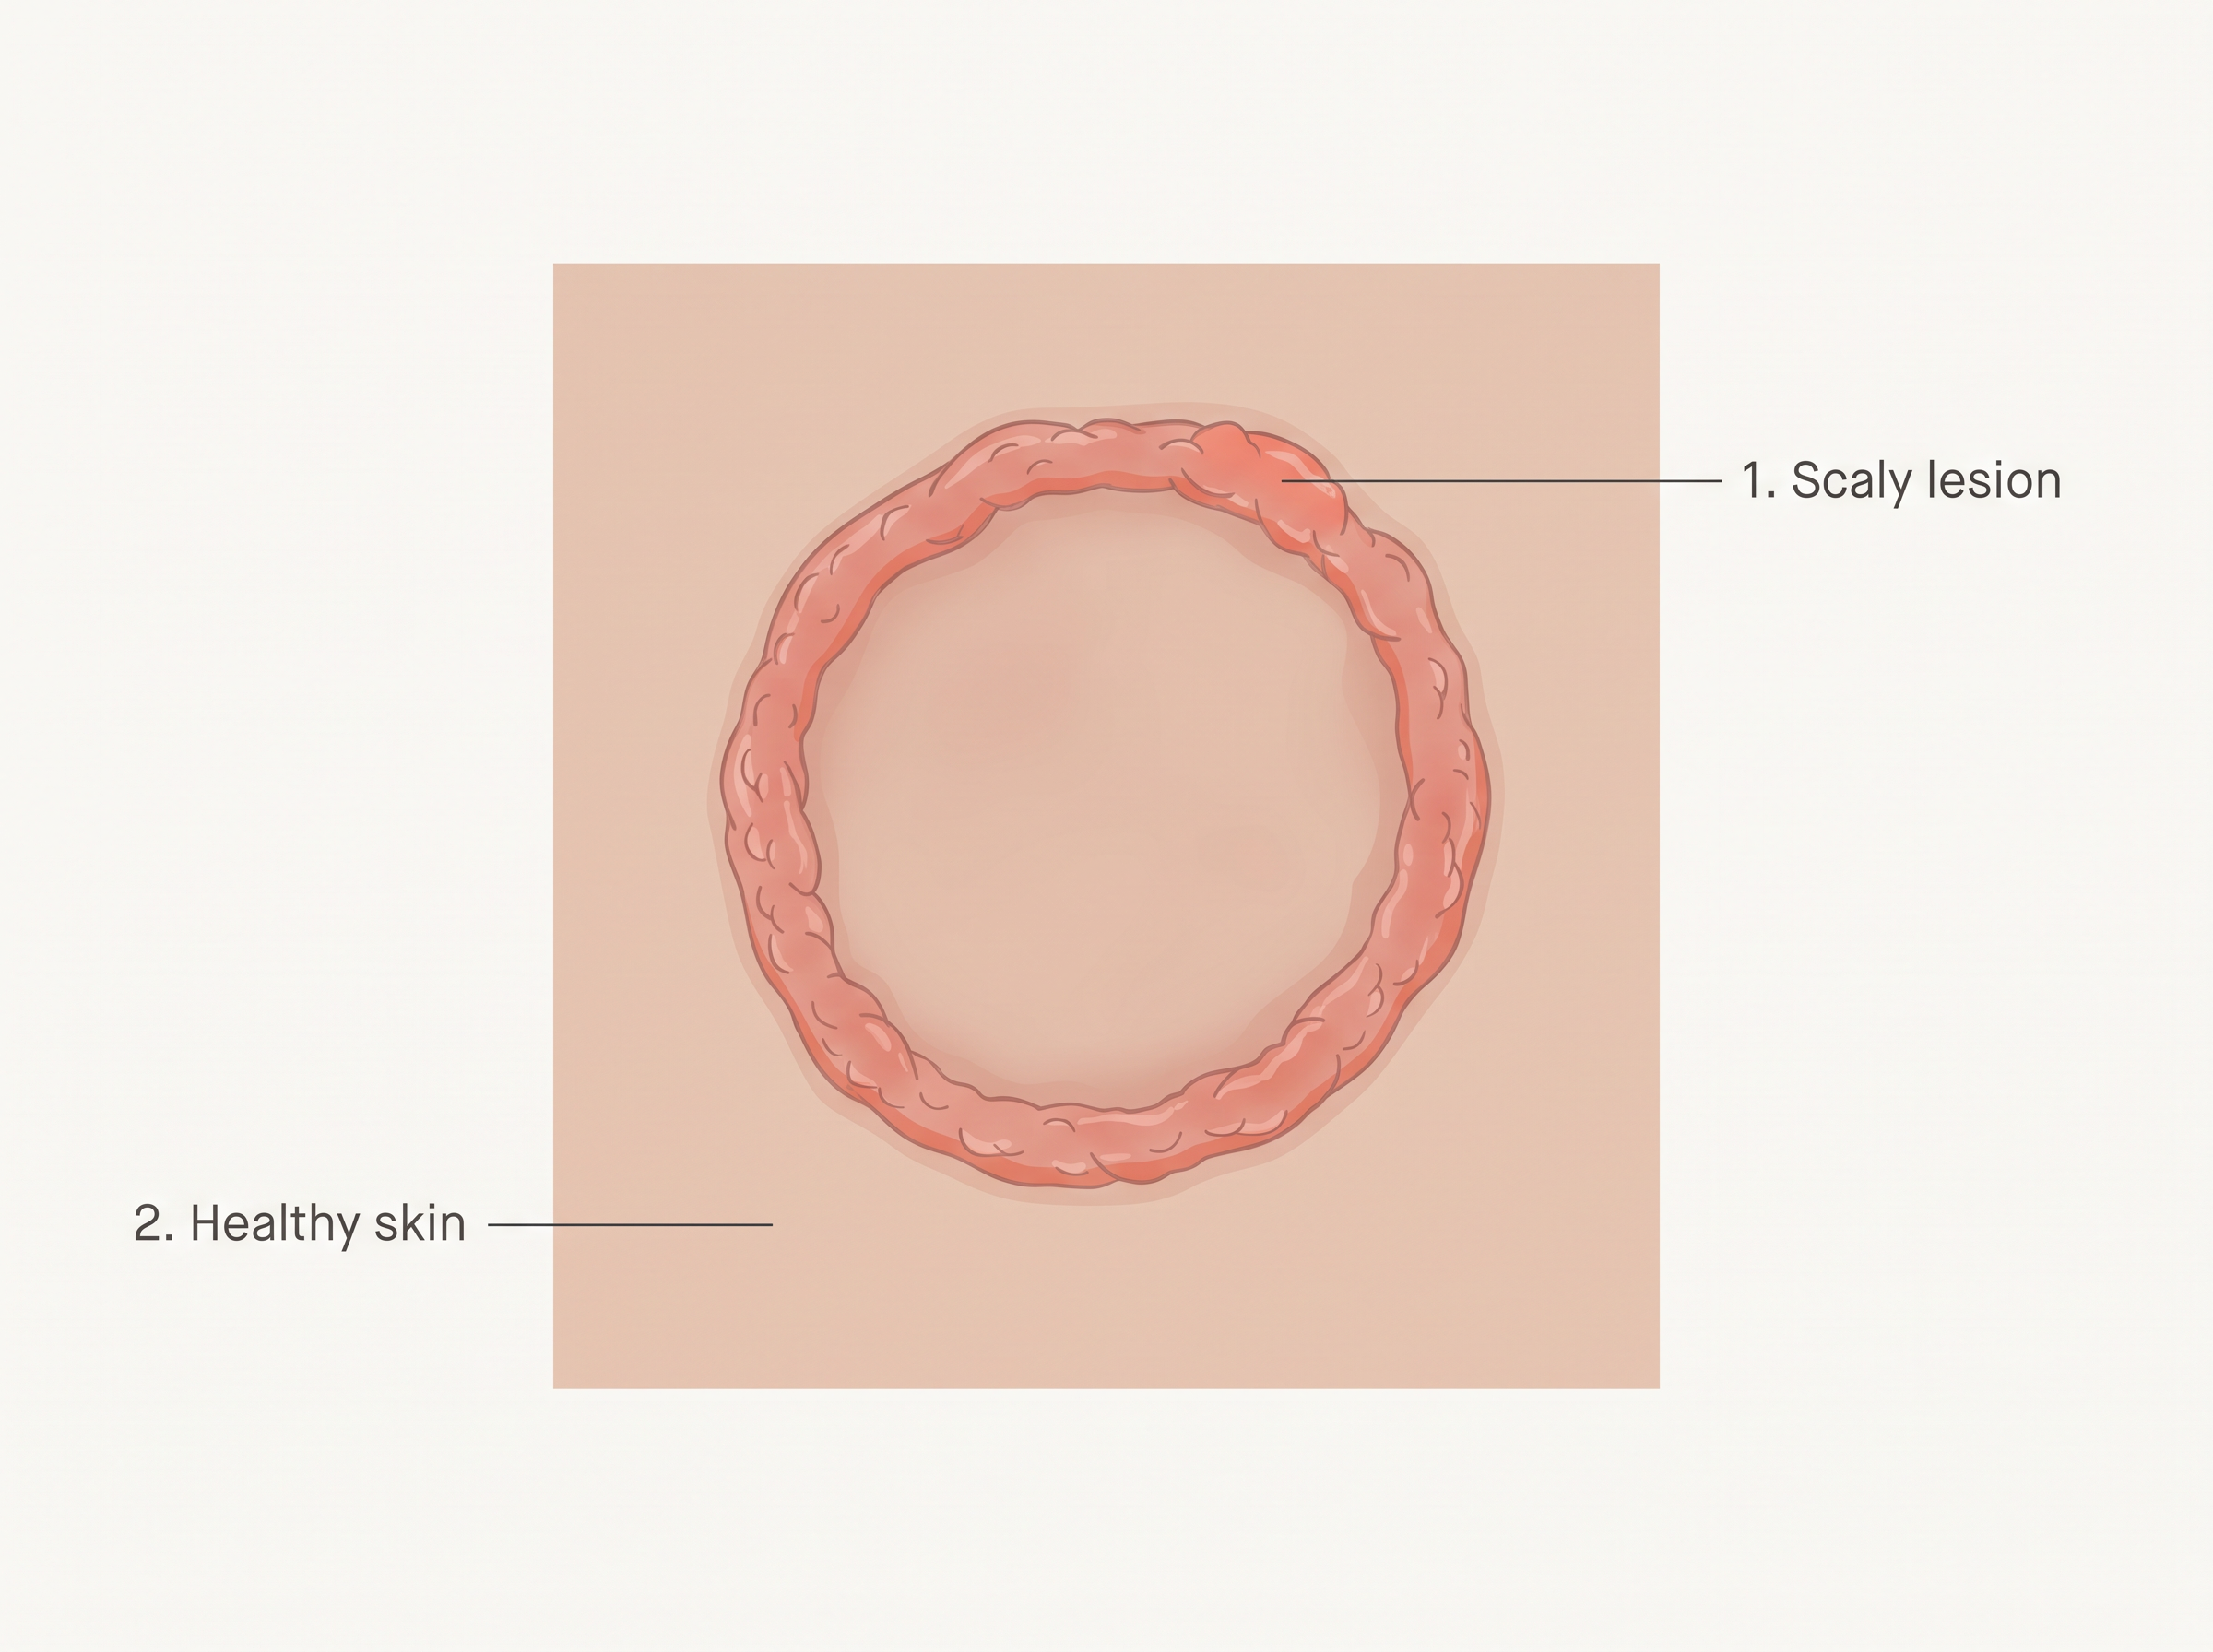
Fig. 7.3 – Ringworm lesion on the skin.
Because the different groups of pathogens and their diseases are a favourite of match-the-following and assertion–reason questions, it is worth linking each disease to its causative organism and its mode of spread as you read.
Preventing and Controlling Infectious Diseases
Maintaining personal and public hygiene is one of the most important ways to prevent and control many infectious diseases. Personal hygiene means keeping the body clean and consuming clean drinking water, food, vegetables and fruits. Public hygiene means proper disposal of waste and excreta; periodic cleaning and disinfection of water reservoirs, pools, cesspools and tanks; and following standard hygiene practices in public catering.
These measures matter most for diseases transmitted through food and water, such as typhoid, amoebiasis and ascariasis. For air-borne diseases such as pneumonia and the common cold, we must additionally avoid close contact with infected people or their belongings.
For vector-borne diseases such as malaria and filariasis, the single most important measure is to control or eliminate the vectors and their breeding places. This can be done by avoiding the stagnation of water in and around homes, regularly cleaning household coolers, using mosquito nets, and introducing larvae-eating fishes like Gambusia into ponds so they feed on mosquito larvae.
Additional steps include spraying insecticides in ditches, drainage areas and swamps, and fitting doors and windows with wire mesh to keep mosquitoes out. Such precautions have become even more important given the recent widespread outbreaks of vector-borne diseases like dengue and chikungunya — both spread by Aedes mosquitoes — in many parts of India.
How Science Has Helped Us Fight Disease
Advances in biological science have armed us to deal effectively with many infectious diseases. The use of vaccines and immunisation programmes has allowed us to completely eradicate a once-deadly disease like smallpox.
A large number of other infectious diseases — such as polio, diphtheria, pneumonia and tetanus — have been brought largely under control through vaccines. Biotechnology, which you will study in Chapter 10, is now on the verge of providing newer and safer vaccines. Alongside this, the discovery of antibiotics and various other drugs has enabled us to treat infectious diseases far more effectively than before.
7.2 Immunity
Every single day we are exposed to a large number of infectious agents — bacteria, viruses, fungi and more. Yet only a few of these exposures actually make us ill. Why is that?
The reason is that our body is able to defend itself against most of these foreign agents. This overall ability of the host to fight off disease-causing organisms, provided by a system of cells and molecules called the immune system, is known as immunity.
Immunity is of two broad types: innate immunity and acquired immunity. As we will see, one is a defence we are born with, while the other develops as we meet different pathogens through life.
Flowchart
FC 7.2 – Classification of immunity: Immunity → (a) Innate immunity (non-specific; present at birth; four barriers) and (b) Acquired immunity (pathogen-specific; has memory; humoral + cell-mediated)
7.2.1 Innate Immunity
Innate immunity is a non-specific type of defence — it acts against a wide range of invaders rather than targeting one particular pathogen — and it is present at the time of birth. It works by placing different kinds of barriers in the way of foreign agents trying to enter the body.
Innate immunity consists of four types of barriers.
The first are the physical barriers. The skin covering our body is the main barrier that prevents the entry of micro-organisms. In addition, the mucus coating of the epithelium (the lining layer) of the respiratory, gastrointestinal and urogenital tracts helps trap microbes that try to get in.
The second are the physiological barriers. The acid in the stomach, the saliva in the mouth, and the tears from the eyes all create conditions that prevent microbial growth.
The third are the cellular barriers. Certain types of leukocytes (white blood cells, WBCs) — such as polymorpho-nuclear leukocytes (PMNL–neutrophils) and monocytes, and natural killer cells (a type of lymphocyte) in the blood, along with macrophages in the tissues — can phagocytose (engulf and swallow) and destroy microbes.
The fourth are the cytokine barriers. When a cell is infected by a virus, it secretes proteins called interferons, which protect the neighbouring non-infected cells from further viral infection.
7.2.2 Acquired Immunity
Acquired immunity, unlike innate immunity, is pathogen-specific — it is tailored to the particular pathogen it meets. Its defining feature is memory.
This means that when our body meets a pathogen for the very first time, it mounts a response called the primary response, which is of low intensity. When the same pathogen is encountered again later, the body produces a much stronger, highly intensified secondary or anamnestic response. This heightened second reaction happens because the body appears to “remember” the first encounter.
The Two Types of Lymphocytes
The primary and secondary immune responses are carried out with the help of two special types of lymphocytes present in our blood: B-lymphocytes and T-lymphocytes.
The B-lymphocytes produce an army of proteins, released into our blood in response to pathogens, that fight the invaders. These proteins are called antibodies. The T-cells do not themselves secrete antibodies, but they help the B-cells to produce them.
Each antibody molecule is made of four peptide chains: two shorter ones called light chains and two longer ones called heavy chains (Fig. 7.4). Because of this, an antibody is represented as \(H_2L_2\). Our body makes several different types of antibodies — IgA, IgM, IgE and IgG are some of them.
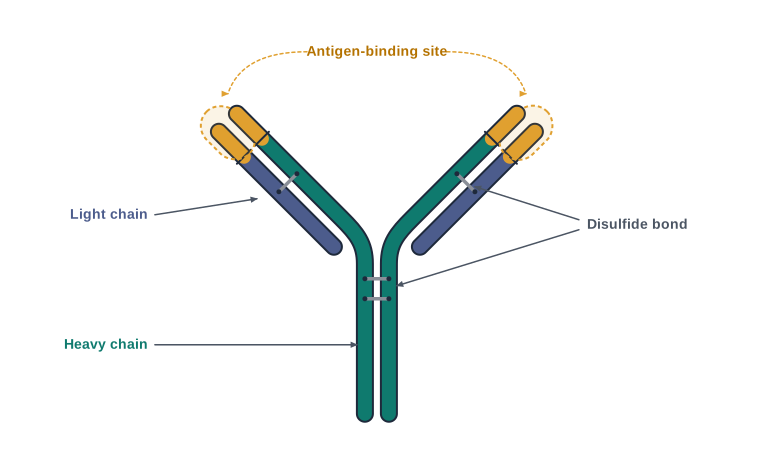
Fig. 7.4 – Structure of an antibody molecule.
Humoral and Cell-mediated Immunity
Because these antibodies are found in the blood — and “humor” is an old word for body fluid — the antibody-mediated response is called the humoral immune response. This is one of the two arms of our acquired immunity.
The second arm is the cell-mediated immune response, or cell-mediated immunity (CMI). This response is carried out by the T-lymphocytes and does not rely on circulating antibodies.
Organ Transplantation and Graft Rejection
Very often, when a human organ such as the heart, eye, liver or kidney fails to work properly, transplantation is the only remedy that lets the patient live a normal life. A search then begins for a suitable donor. But why can the organ not be taken from just anybody, and what do the doctors check?
Grafts (transplanted tissues or organs) from just any source — an animal, another primate, or any human being — cannot be used, because such grafts would be rejected by the body sooner or later. That is why tissue matching and blood group matching are essential before any graft or transplant. Even after a successful match, the patient has to take immuno-suppressants (drugs that suppress the immune response) all through their life.
The body is able to tell the difference between “self” and “nonself,” and it is the cell-mediated immune response that is responsible for the rejection of a graft.
7.2.3 Active and Passive Immunity
When a host is exposed to antigens — which may be living or dead microbes, or other foreign proteins — the host’s own body produces antibodies against them. This kind of immunity, built by the body itself, is called active immunity. Active immunity is slow and takes time to give its full protective effect.
Active immunity is induced either by deliberately injecting microbes during immunisation, or by infectious organisms entering the body during a natural infection.
Sometimes, instead of waiting for the body to make its own antibodies, ready-made antibodies are given directly to protect the body against foreign agents. This is called passive immunity.
A familiar example explains why mother’s milk is considered so essential for a newborn. The yellowish fluid called colostrum, secreted by the mother during the initial days of lactation, is rich in antibodies (IgA) that protect the infant. Even before birth, the foetus receives some antibodies from the mother through the placenta during pregnancy. Both of these are examples of passive immunity.
7.2.4 Vaccination and Immunisation
The principle behind immunisation or vaccination is based on the “memory” property of the immune system. In vaccination, a preparation of antigenic proteins of a pathogen, or an inactivated or weakened form of the pathogen (the vaccine), is introduced into the body.
The antibodies produced in the body against these antigens would then neutralise the actual pathogen during a real infection. Crucially, the vaccine also generates memory — B-cells and T-cells that recognise the pathogen quickly on later exposure and overwhelm the invaders with a massive production of antibodies.
In some situations there is no time to wait for the body to build its own response. If a person is infected by a deadly microbe that needs a quick immune reaction — as in tetanus — we directly inject preformed antibodies, or an antitoxin (a preparation containing antibodies against the toxin). Similarly, for snakebites, the injection given to the patient contains preformed antibodies against the snake venom. This type of protection is called passive immunisation.
Modern biotechnology has widened what vaccines can do. Recombinant DNA technology allows the antigenic polypeptides of a pathogen to be produced inside bacteria or yeast. Vaccines made this way can be produced on a large scale, making them more widely available for immunisation — for example, the hepatitis B vaccine produced from yeast.
7.2.5 Allergies
Have you ever gone to a new place and suddenly started sneezing and wheezing for no obvious reason, only for the symptoms to vanish once you left? Some of us are sensitive to particular particles in the environment, and such a reaction may be due to an allergy to pollen, mites and similar substances, which differ from place to place.
The exaggerated response of the immune system to certain antigens present in the environment is called an allergy. The substances that trigger such a response are called allergens, and the antibodies produced against them are of the IgE type. Common allergens include mites in dust, pollen and animal dander (tiny flakes of skin or hair).
The symptoms of allergic reactions include sneezing, watery eyes, a running nose, and difficulty in breathing. These symptoms arise because the allergy causes the release of chemicals like histamine and serotonin from the mast cells (a type of immune cell in tissues).
To find out the cause of an allergy, the patient is exposed to, or injected with, very small doses of possible allergens, and the reactions are studied. Drugs such as anti-histamine, adrenalin and steroids can quickly reduce the symptoms of allergy.
Interestingly, modern-day lifestyle seems to have lowered immunity and increased sensitivity to allergens. More and more children in the metro cities of India suffer from allergies and asthma due to sensitivity to the environment — possibly because of the very protected, clean environment they are given early in life.
7.2.6 Auto Immunity
Memory-based acquired immunity evolved in higher vertebrates from the ability to tell foreign organisms (such as pathogens) apart from the body’s own self-cells. Although we still do not fully understand the basis of this ability, two important consequences follow from it.
First, higher vertebrates can distinguish foreign molecules as well as whole foreign organisms — and much of experimental immunology is devoted to studying this. Second, sometimes, due to genetic and other unknown reasons, the body mistakenly attacks its own self-cells. This causes damage to the body and is called an auto-immune disease.
Rheumatoid arthritis, which affects many people in our society, is an example of an auto-immune disease.
7.2.7 Immune System in the Body
The human immune system is made up of lymphoid organs, tissues, cells and soluble molecules like antibodies. As we have seen, the immune system is unique in that it recognises foreign antigens, responds to them, and remembers them. It also plays a central role in allergic reactions, auto-immune diseases and organ transplantation.
Lymphoid Organs
Lymphoid organs are the organs where lymphocytes originate, and/or mature and multiply. They are grouped into primary and secondary lymphoid organs.
The primary lymphoid organs are the bone marrow and the thymus, where immature lymphocytes differentiate into antigen-sensitive lymphocytes. After they mature here, the lymphocytes migrate to the secondary lymphoid organs.
The secondary lymphoid organs are the spleen, lymph nodes, tonsils, Peyer’s patches of the small intestine, and the appendix. These provide the sites where lymphocytes meet the antigen, after which they multiply to become effector cells (the active cells that carry out the immune response). The location of the various lymphoid organs in the body is shown in Fig. 7.5.
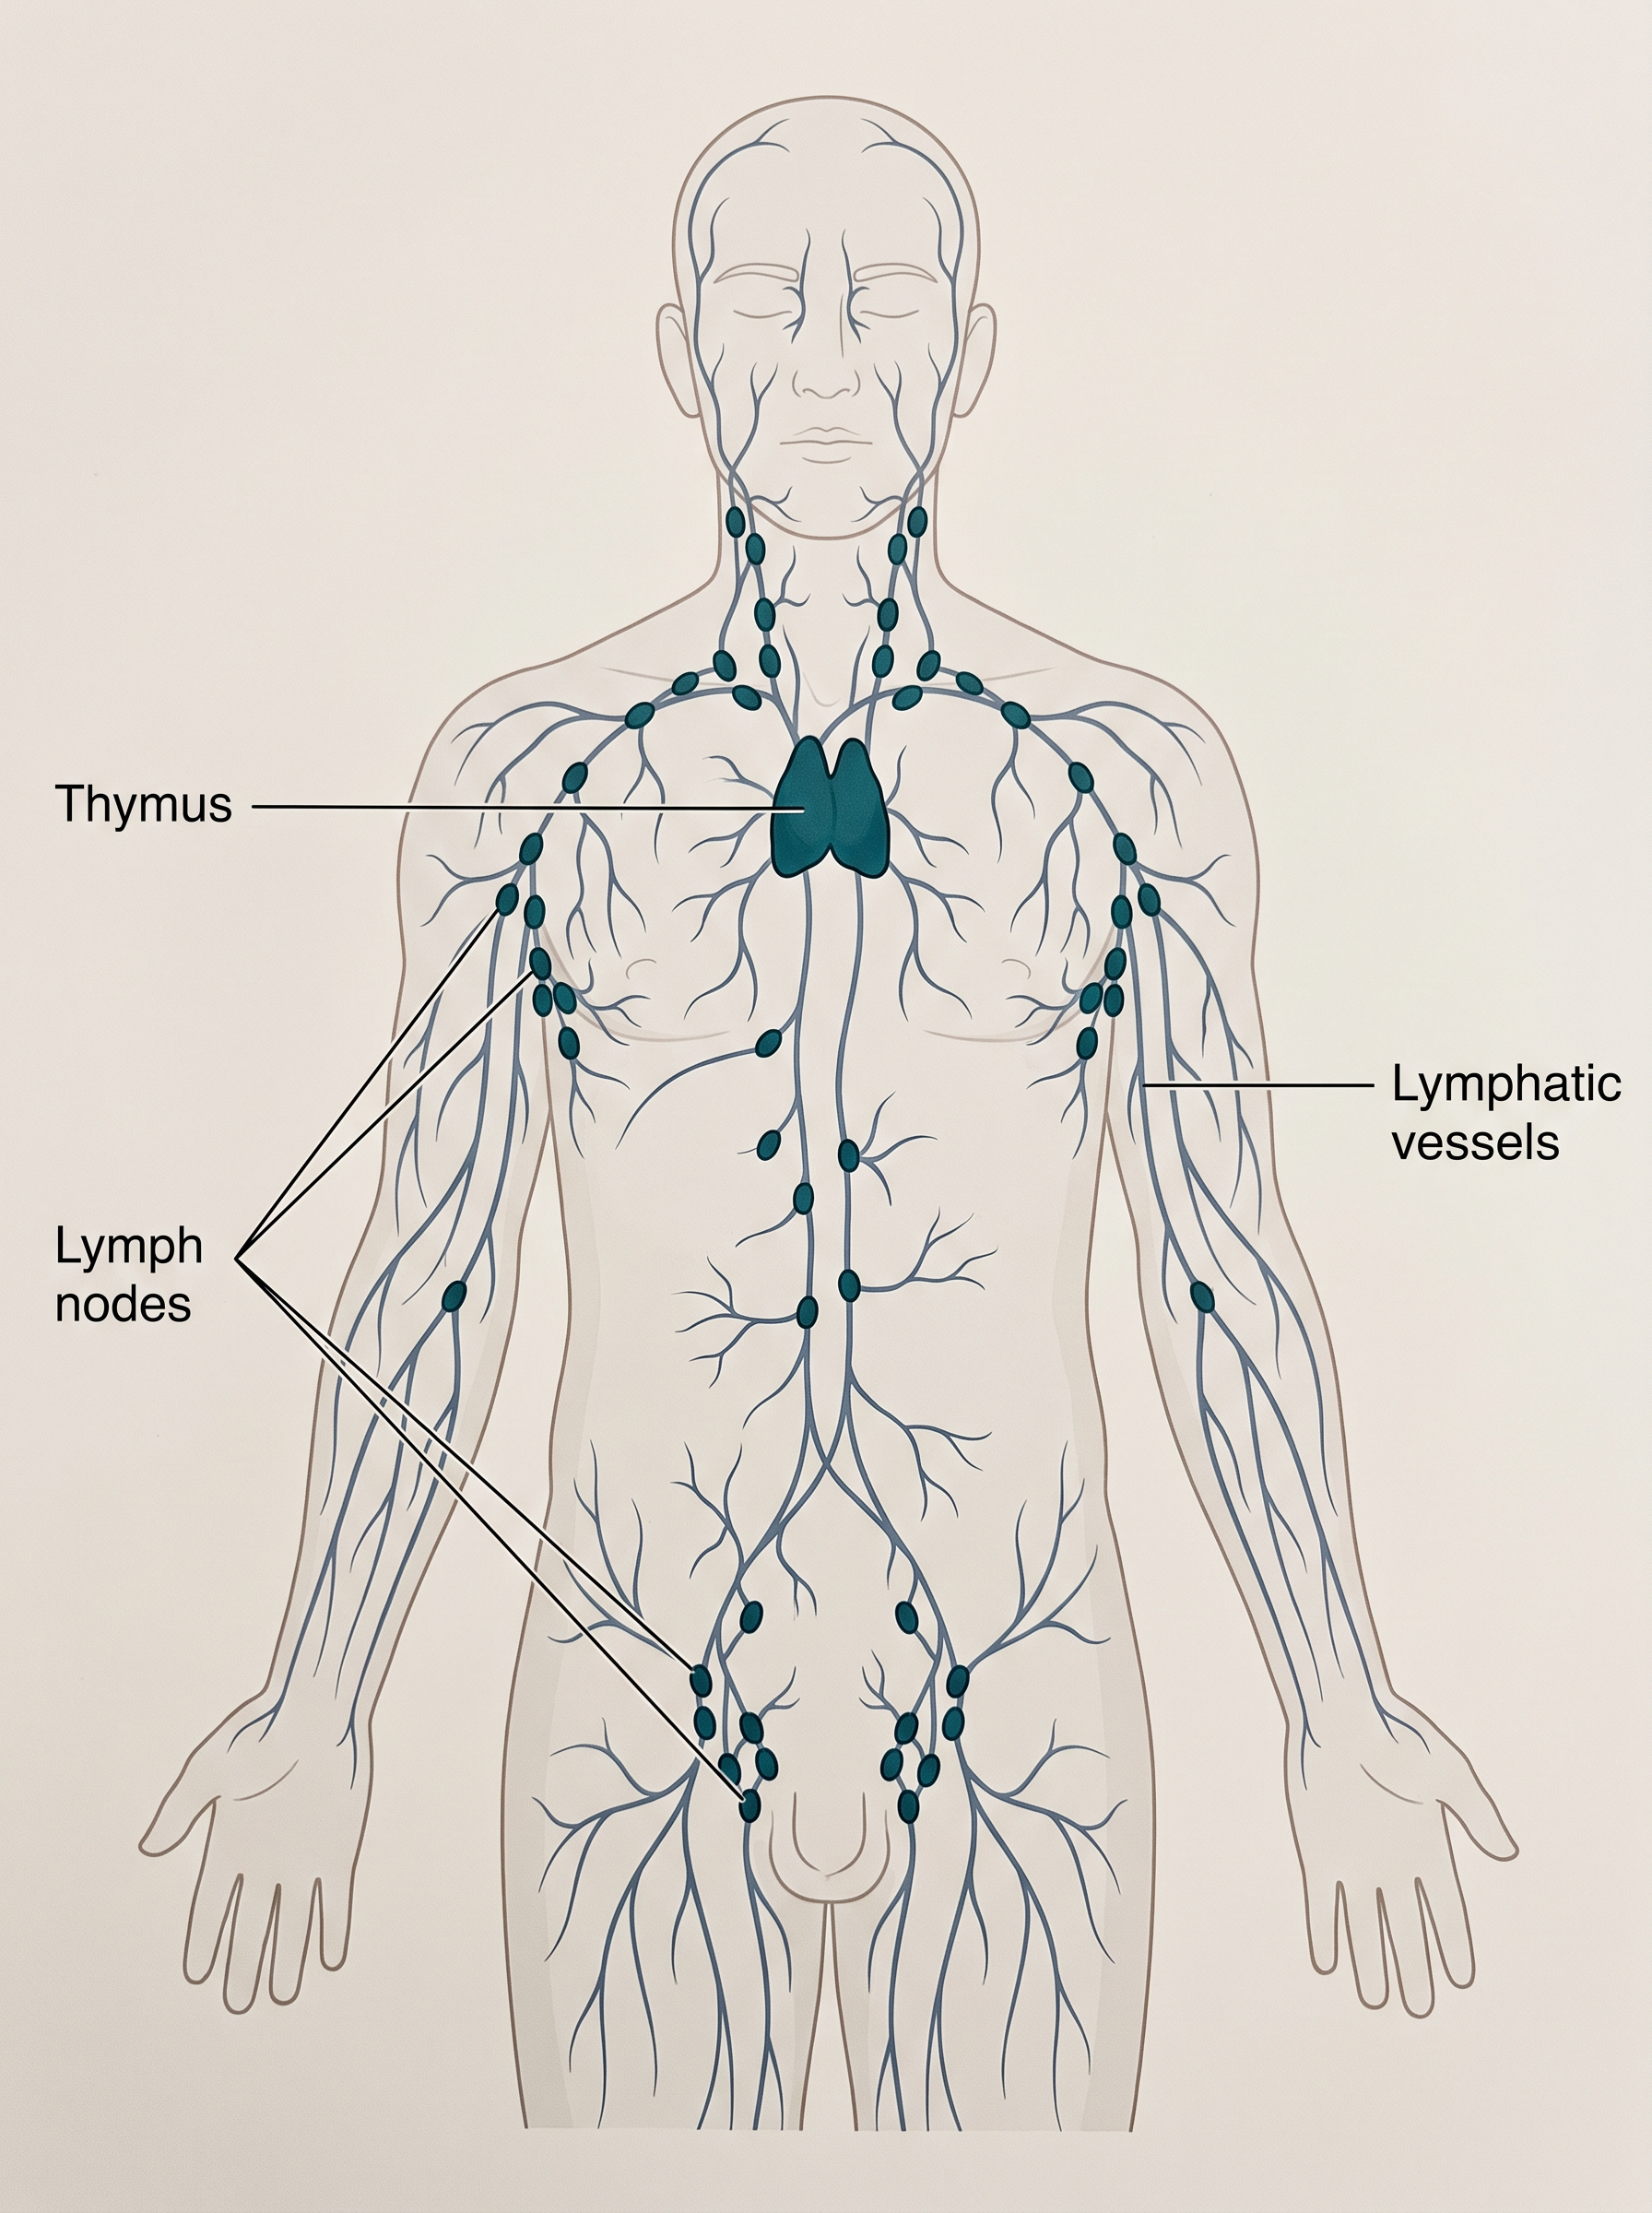
Fig. 7.5 – Lymphoid organs in the human body.
Flowchart
FC 7.3 – Journey of a lymphocyte: immature lymphocyte formed → matures in a primary lymphoid organ (bone marrow / thymus) → becomes antigen-sensitive → migrates to a secondary lymphoid organ (spleen, lymph node, tonsils, Peyer’s patches, appendix) → meets antigen → proliferates into effector cells → immune response
The Major Lymphoid Organs
The bone marrow is the main lymphoid organ, where all the blood cells — including lymphocytes — are produced.
The thymus is a lobed organ located near the heart and beneath the breastbone. It is quite large at the time of birth but keeps reducing in size with age, and by the time puberty is reached it has shrunk to a very small size. Both the bone marrow and the thymus provide the micro-environments needed for the development and maturation of T-lymphocytes.
The spleen is a large, bean-shaped organ. It mainly contains lymphocytes and phagocytes and acts as a filter of the blood, trapping blood-borne micro-organisms. The spleen also serves as a large reservoir of erythrocytes (red blood cells).
The lymph nodes are small, solid structures located at various points along the lymphatic system. They trap the micro-organisms or other antigens that happen to get into the lymph and tissue fluid. Antigens trapped in the lymph nodes activate the lymphocytes present there and bring about the immune response.
There is also lymphoid tissue located within the lining of the major tracts — the respiratory, digestive and urogenital tracts — called the mucosa-associated lymphoid tissue (MALT). Remarkably, MALT makes up about 50 per cent of the lymphoid tissue in the human body.
7.3 AIDS
The word AIDS stands for Acquired Immuno Deficiency Syndrome. Reading the name carefully tells us a great deal about the disease. “Acquired” means the immune deficiency is picked up during the lifetime of an individual — it is not something a person is born with (it is not congenital). “Immuno Deficiency” means the immune system becomes weak and deficient. “Syndrome” means a group of symptoms that appear together.
AIDS was first reported in 1981, and over the roughly twenty-five years that followed, it spread all over the world, killing more than 25 million persons.
AIDS is caused by the Human Immuno deficiency Virus (HIV). HIV is a member of a group of viruses called retroviruses, which have an outer envelope enclosing an RNA genome (Fig. 7.6).
The Virus Behind AIDS
A retrovirus is unusual because its genetic material is RNA, not DNA. To multiply inside a host cell, it must first convert its RNA into DNA — the reverse of the usual flow of genetic information — which is why it is called a “retro” (backward) virus. This conversion is carried out by a special viral enzyme called reverse transcriptase.
How HIV Is Transmitted
Transmission of HIV infection generally occurs by four routes: (a) sexual contact with an infected person; (b) transfusion of contaminated blood and blood products; (c) sharing infected needles, as in the case of intravenous drug abusers; and (d) from an infected mother to her child through the placenta.
Because of these routes, the people at high risk of getting the infection include individuals who have multiple sexual partners, drug addicts who take drugs intravenously, individuals who require repeated blood transfusions, and children born to an HIV-infected mother.
It is very important to note that HIV/AIDS is not spread by mere touch or ordinary physical contact — it spreads only through body fluids. For this reason, both for their physical and psychological well-being, HIV/AIDS-infected persons must not be isolated from their family and society.
There is always a time-lag between the infection and the appearance of AIDS symptoms. This period may vary from a few months to many years, usually about 5–10 years.
How HIV Destroys the Immune System
Once HIV gets into the body, the virus enters macrophages. Inside them, the RNA genome of the virus is copied into viral DNA with the help of the enzyme reverse transcriptase. This viral DNA becomes incorporated into the host cell’s own DNA and directs the infected cells to produce new virus particles (Fig. 7.6). The macrophages keep producing virus and in this way act like an “HIV factory.”
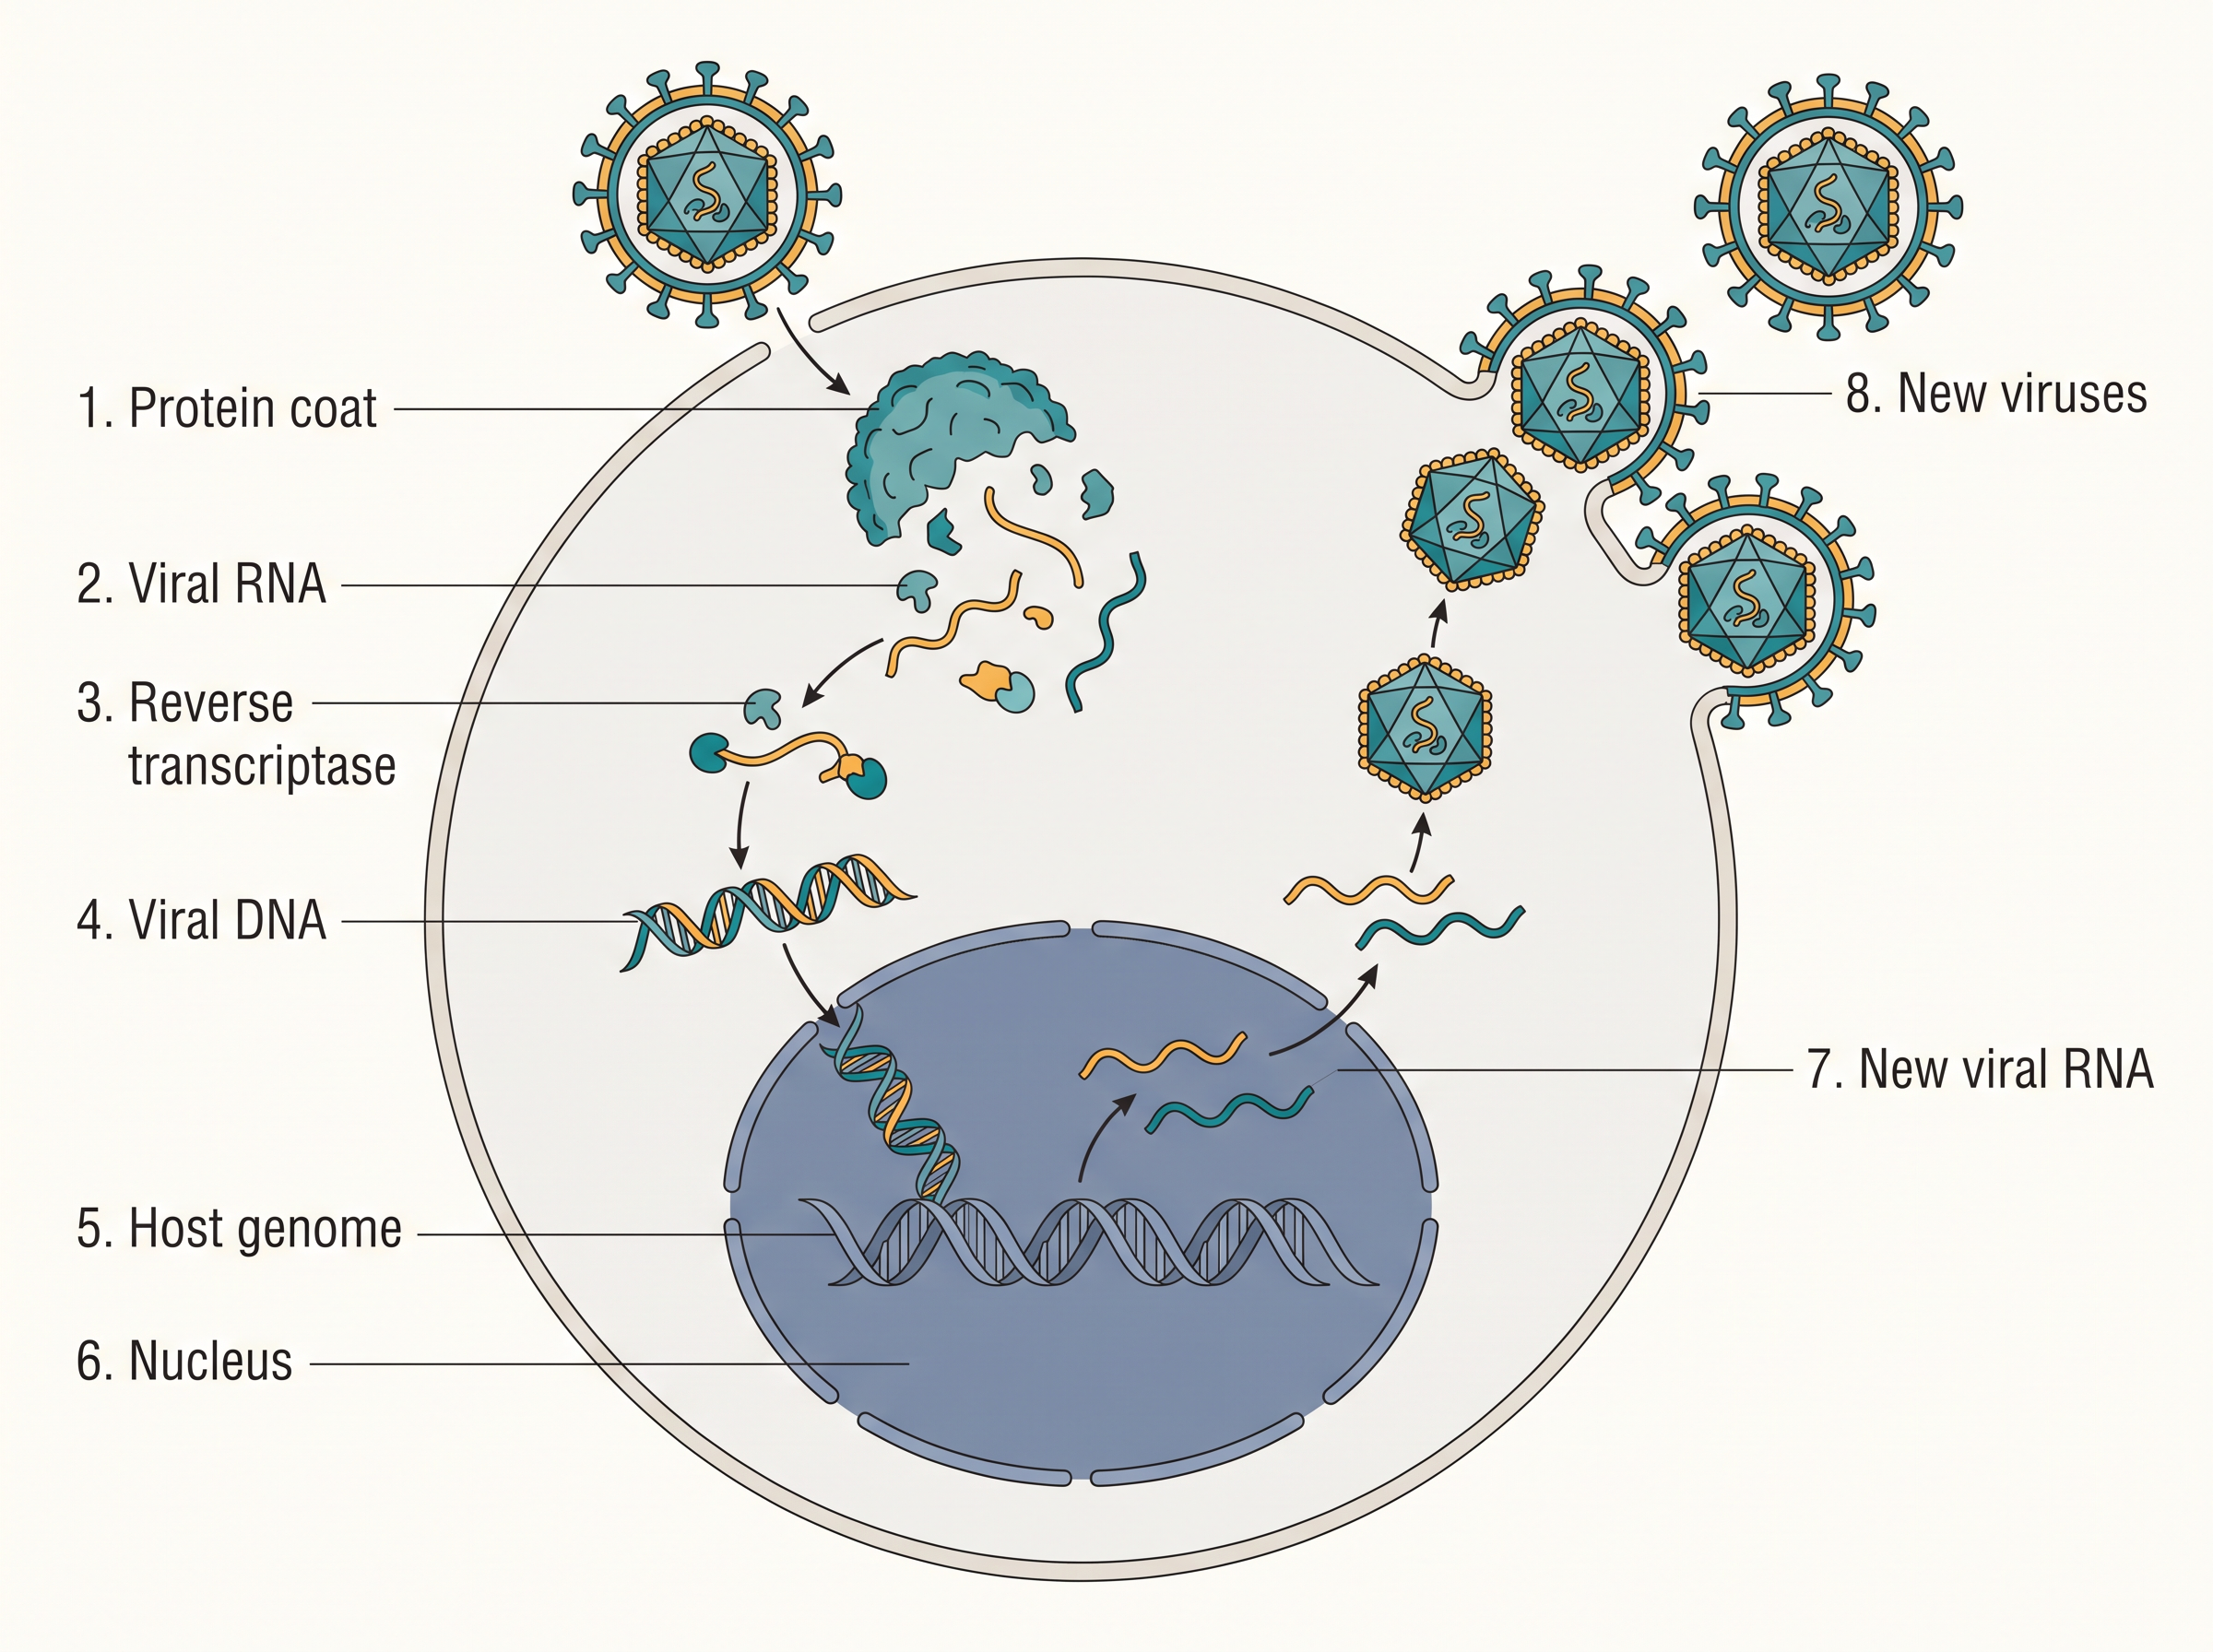
Fig. 7.6 – Replication of a retrovirus.
At the same time, HIV enters the helper T-lymphocytes (\(T_H\)), where it replicates and produces progeny (offspring) viruses. These progeny viruses are released into the blood and attack still more helper T-lymphocytes. As this repeats, there is a progressive decrease in the number of helper T-lymphocytes in the infected person’s body.
Flowchart
FC 7.4 – HIV replication and immune collapse: HIV enters body → enters macrophage → reverse transcriptase makes viral DNA → viral DNA integrates into host DNA → host cell produces new viruses (macrophage as HIV factory) → HIV also enters helper T-lymphocytes → replicates and releases progeny viruses → progeny attack more helper T-cells → progressive fall in helper T-cell numbers → immunodeficiency → opportunistic infections → AIDS
During this period, the person suffers from bouts of fever, diarrhoea and weight loss. As the number of helper T-lymphocytes falls, the person starts suffering from infections that a healthy body could normally overcome — such as those caused by bacteria (especially Mycobacterium), viruses, fungi, and even parasites like Toxoplasma. The patient becomes so immuno-deficient that he or she is unable to fight off these infections.
A widely used diagnostic test for AIDS is the enzyme linked immuno-sorbent assay (ELISA). Treatment of AIDS with anti-retroviral drugs is only partially effective: these drugs can prolong the life of the patient but cannot prevent death, which is inevitable.
Prevention of AIDS
Since AIDS has no cure, prevention is the best option. Moreover, HIV infection more often spreads due to conscious behaviour patterns rather than by accident, unlike diseases such as pneumonia or typhoid. Of course, infection in blood transfusion patients and in newborns (from the mother) can occur due to poor monitoring. The only real excuse is ignorance, and it has rightly been said — “don’t die of ignorance.”
In our country, the National AIDS Control Organisation (NACO) and various non-governmental organisations (NGOs) are doing a great deal to educate people about AIDS. The World Health Organization (WHO) has started a number of programmes to prevent the spread of HIV infection.
The main preventive steps include making blood from blood banks safe from HIV, ensuring the use of only disposable needles and syringes in public and private hospitals and clinics, free distribution of condoms, controlling drug abuse, advocating safe sex, and promoting regular check-ups for HIV in susceptible populations.
7.4 Cancer
Cancer is one of the most dreaded diseases of human beings and is a major cause of death all over the globe. More than a million Indians suffer from cancer, and a large number of them die from it every year.
Because of this, the mechanisms that underlie the development of cancer — the oncogenic transformation of cells — along with its treatment and control, have been among the most intense areas of research in biology and medicine.
How Cancer Cells Differ from Normal Cells
In our body, cell growth and differentiation (the process by which cells become specialised) are normally kept under tight control and regulation. In cancer cells, these regulatory mechanisms break down.
Normal cells show a property called contact inhibition: when a cell comes into contact with other cells, this contact stops it from dividing uncontrollably. Cancer cells appear to have lost this property. As a result, cancerous cells simply keep on dividing, giving rise to masses of cells called tumors.
Tumors are of two types: benign and malignant. Benign tumors normally remain confined to their original location, do not spread to other parts of the body, and cause little damage.
Malignant tumors, on the other hand, are masses of actively proliferating cells called neoplastic or tumor cells. These cells grow very rapidly, invading and damaging the surrounding normal tissues. As they actively divide and grow, they also starve the normal cells by competing with them for vital nutrients.
A particularly dangerous feature of malignant tumors is that cells sloughed off (shed) from them can reach distant sites through the blood. Wherever such a cell gets lodged in the body, it starts a new tumor there. This property, called metastasis, is the most feared property of malignant tumors.
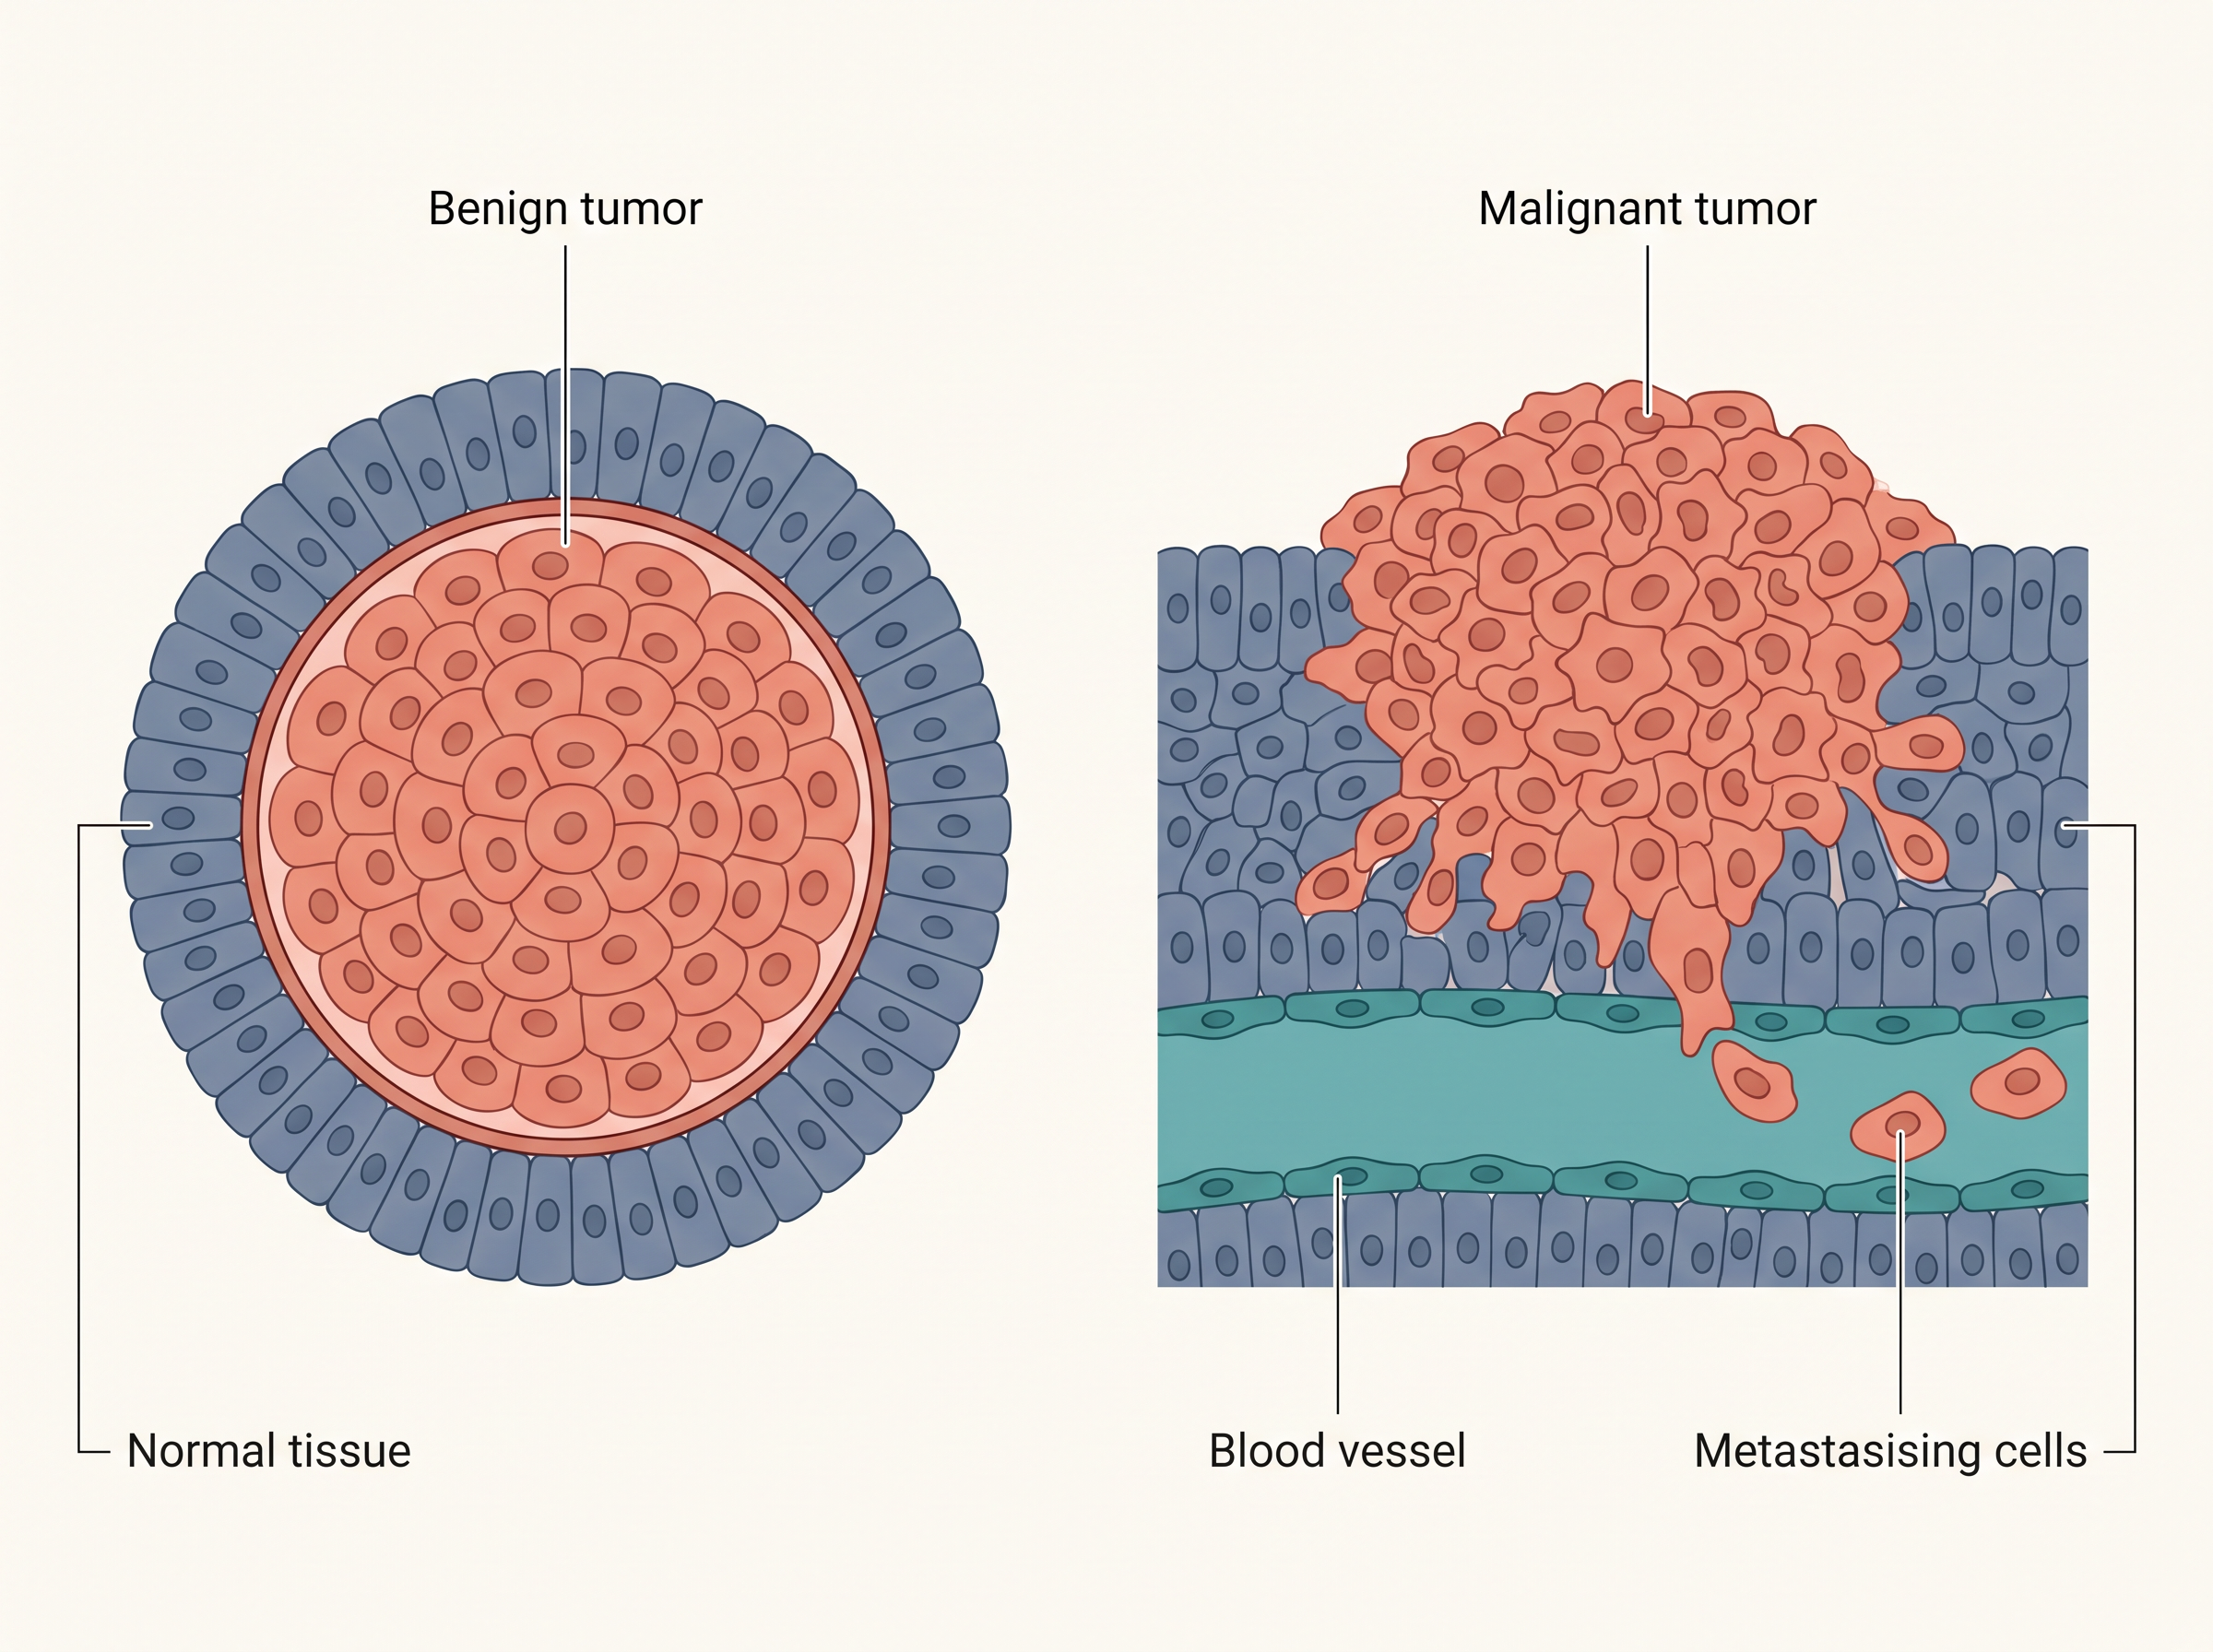
Fig. 7.7 – Benign versus malignant tumours.
Flowchart
FC 7.5 – Metastasis: normal cell loses contact inhibition → divides uncontrollably → forms malignant tumor → cells slough off → enter the blood → travel to a distant organ → get lodged and multiply → new (secondary) tumor forms
Causes of Cancer
The transformation of normal cells into cancerous, neoplastic cells can be triggered by physical, chemical or biological agents. These cancer-causing agents are called carcinogens.
Among physical carcinogens, ionising radiations like X-rays and gamma rays, and non-ionizing radiations like ultraviolet (UV) light, cause DNA damage that can lead to neoplastic transformation. Among chemical carcinogens, those present in tobacco smoke have been identified as a major cause of lung cancer.
Biological agents matter too. Cancer-causing viruses, called oncogenic viruses, carry genes called viral oncogenes. Furthermore, several genes called cellular oncogenes (c-onc) or proto oncogenes have been identified in normal cells. Under certain conditions, when these genes get activated, they can lead to the oncogenic transformation of the cells.
Flowchart
FC 7.6 – How cancer develops (carcinogenesis): carcinogen (ionising/non-ionising radiation, chemical, or oncogenic virus) → DNA damage or activation of oncogenes/proto-oncogenes → breakdown of growth regulation → loss of contact inhibition → uncontrolled division → neoplastic transformation → cancer
Cancer Detection and Diagnosis
Early detection of cancer is essential, because it allows the disease to be treated successfully in many cases.
Cancer detection is based on biopsy and histopathological studies of the tissue, and on blood and bone marrow tests for increased cell counts in the case of leukemias (cancers of the blood-forming tissue). In a biopsy, a piece of the suspected tissue is cut into thin sections, stained, and examined under a microscope by a pathologist — this examination is the histopathological study.
Imaging techniques are also very useful for detecting cancers of the internal organs. These include radiography (the use of X-rays), CT (computed tomography) and MRI (magnetic resonance imaging). Computed tomography uses X-rays to generate a three-dimensional image of the internal parts of an object. MRI uses strong magnetic fields and non-ionising radiations to accurately detect pathological and physiological changes in the living tissue.
In addition, antibodies against cancer-specific antigens are used to detect certain cancers. Techniques of molecular biology can also be applied to detect genes in individuals who have an inherited susceptibility to certain cancers. Identifying such genes — which predispose an individual to particular cancers — can be very helpful in prevention, since such individuals may be advised to avoid the specific carcinogens to which they are susceptible.
Treatment of Cancer
The common approaches for treating cancer are surgery, radiation therapy and immunotherapy.
In radiotherapy, the tumor cells are irradiated lethally (given a fatal dose of radiation), while proper care is taken to protect the normal tissues surrounding the tumor mass. Several chemotherapeutic drugs are used to kill cancerous cells, and some of these are specific to particular tumors. Many of these drugs have side effects such as hair loss and anemia. Most cancers are treated by a combination of surgery, radiotherapy and chemotherapy.
Tumor cells have been shown to avoid detection and destruction by the immune system. To counter this, patients are given substances called biological response modifiers, such as α-interferon, which activate the patient’s own immune system and help it to destroy the tumor.
7.5 Drugs and Alcohol Abuse
Surveys and statistics show that the use of drugs and alcohol has been on the rise, especially among the youth. This is a serious cause of concern, because it can lead to many harmful effects. Proper education and guidance can help young people safeguard themselves against these dangerous behaviour patterns and follow healthy lifestyles.
The drugs that are commonly abused are opioids, cannabinoids and coca alkaloids. Most of these are obtained from flowering plants, while some are obtained from fungi.
Commonly Abused Drugs
Opioids are drugs that bind to specific opioid receptors present in our central nervous system (the brain and spinal cord) and gastrointestinal tract. Heroin (Fig. 7.8), commonly called smack, is chemically diacetylmorphine — a white, odourless, bitter, crystalline compound. It is obtained by the acetylation of morphine (Fig. 7.8), which is extracted from the latex of the poppy plant Papaver somniferum (Fig. 7.9). Generally taken by snorting and injection, heroin is a depressant, meaning it slows down the body’s functions.
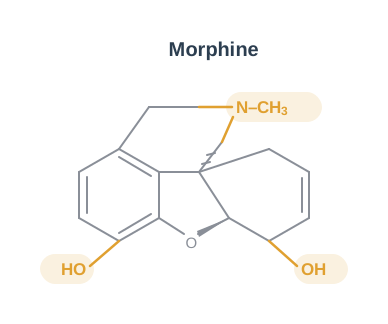
Fig. 7.8 – Chemical structure of morphine.
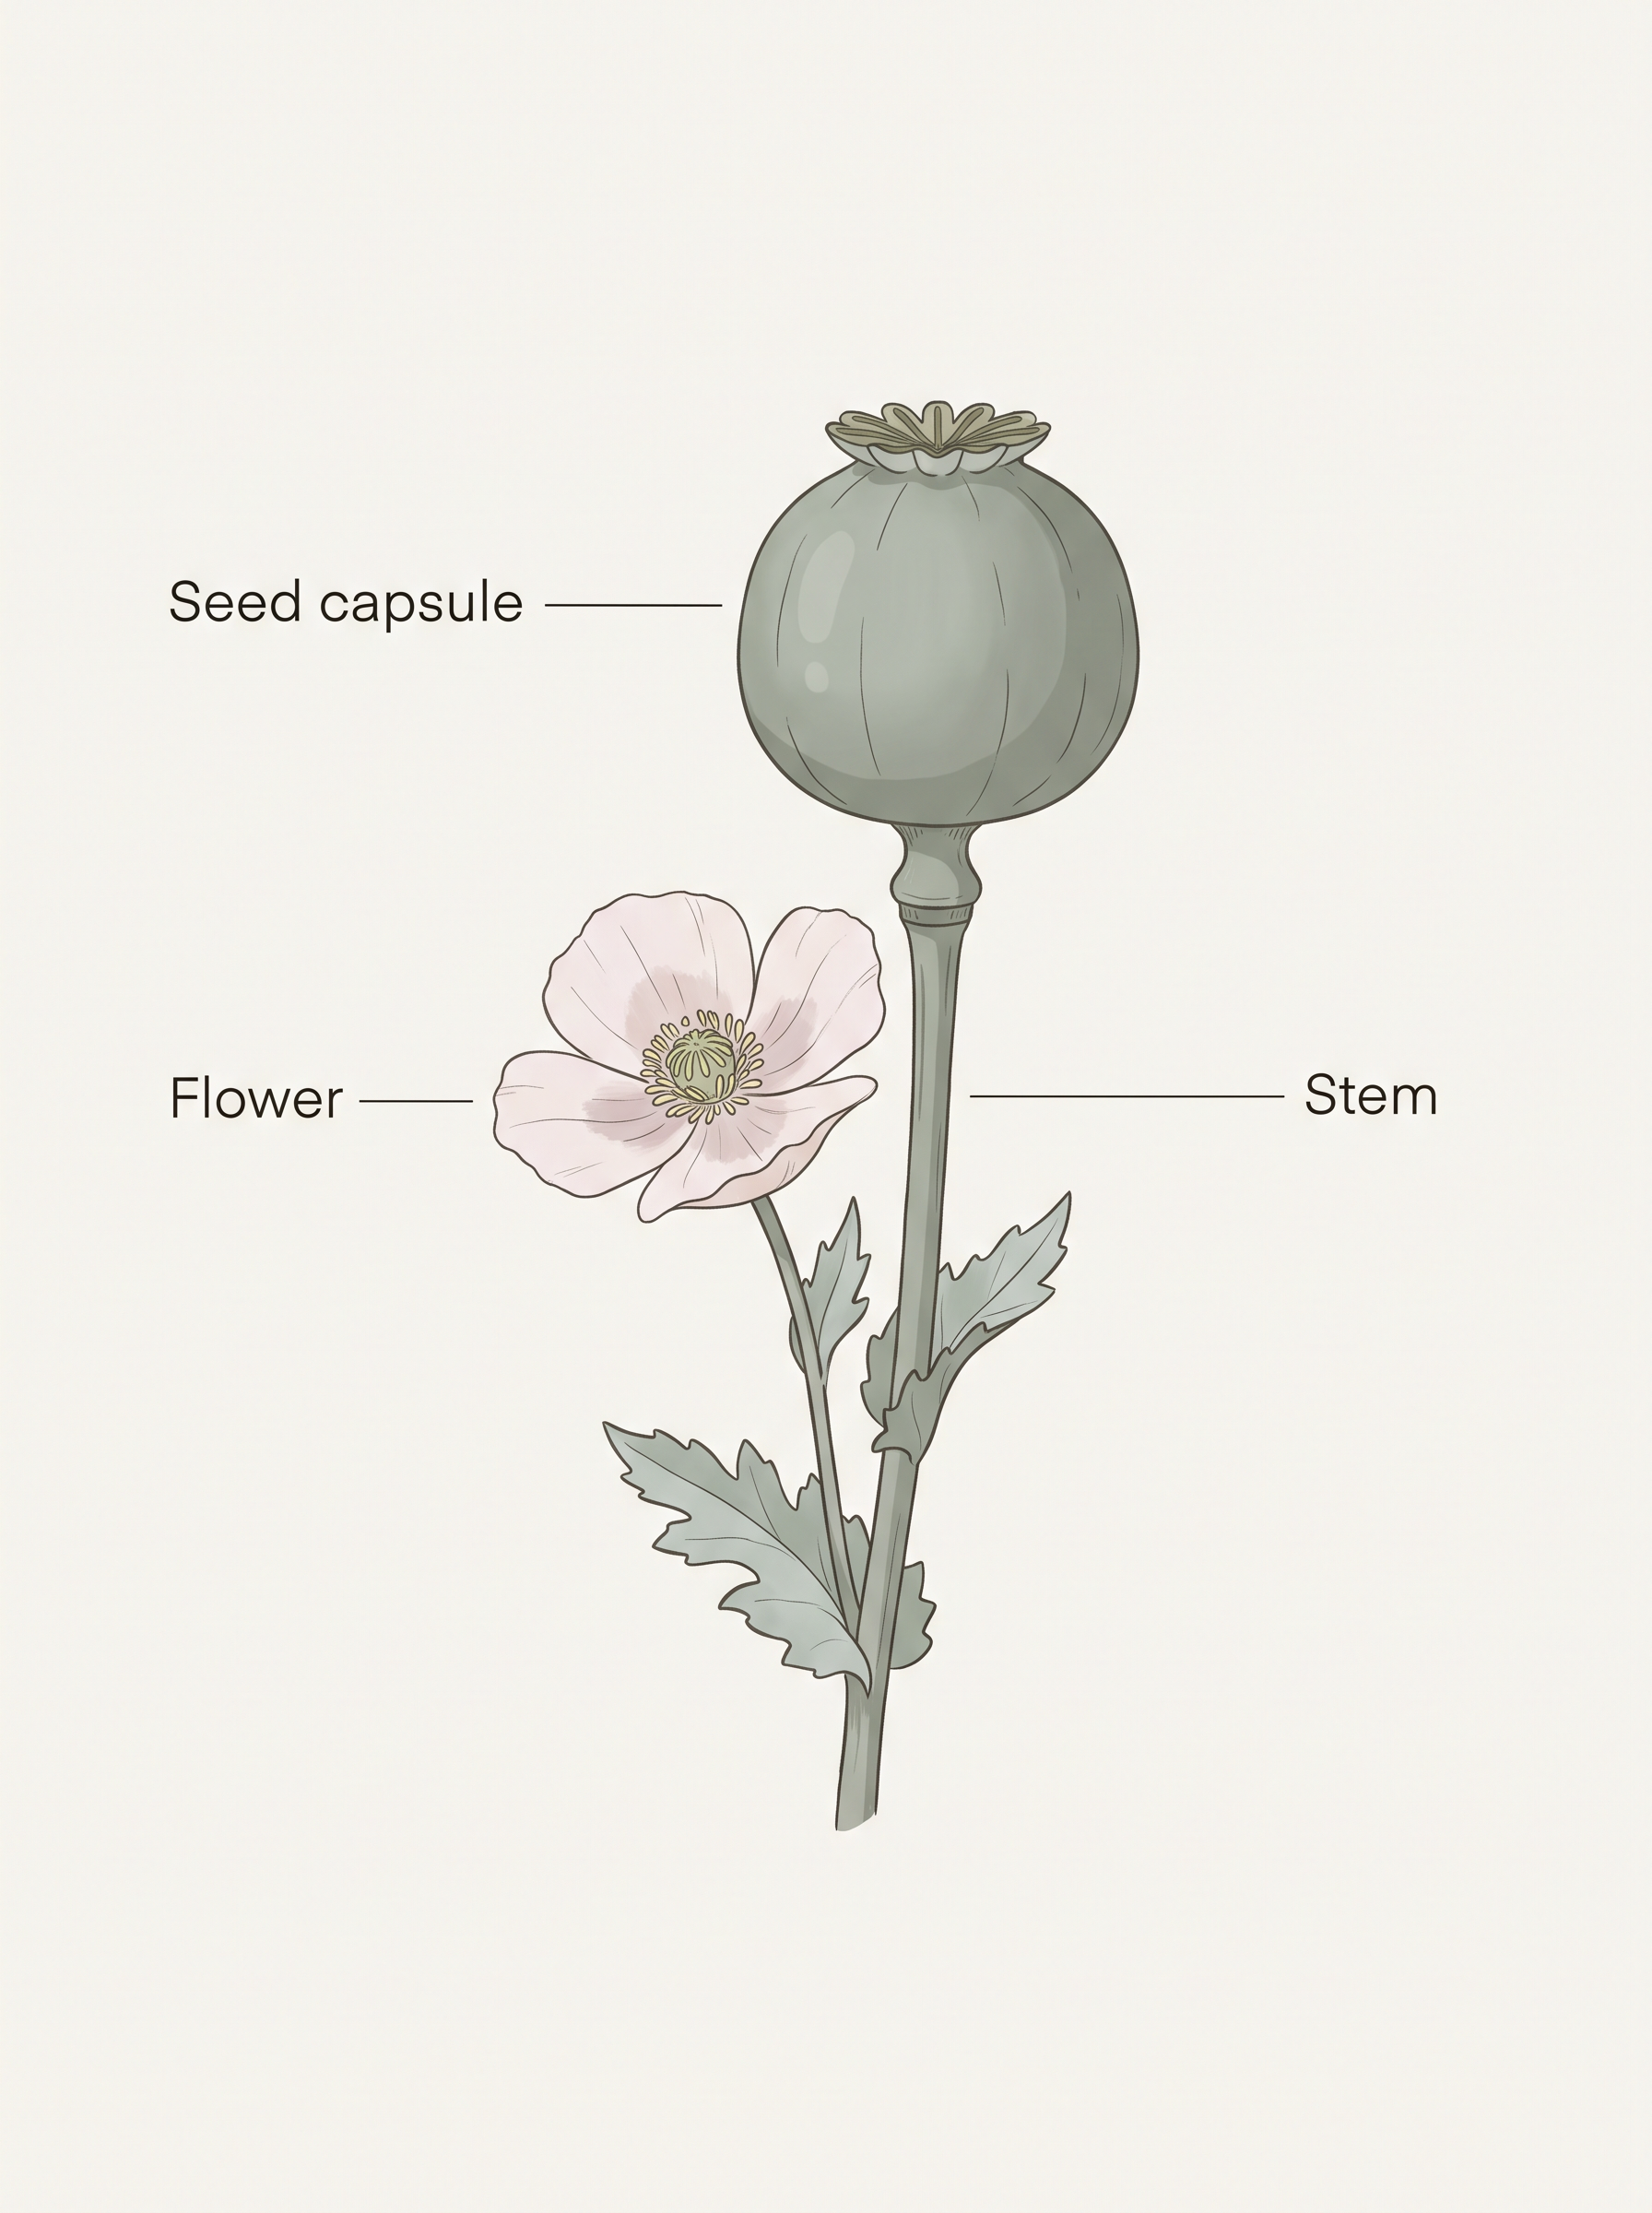
Fig. 7.9 – Opium poppy (Papaver somniferum).
Flowchart
FC 7.7 – From poppy to heroin: latex of Papaver somniferum → morphine extracted → acetylation of morphine → heroin (diacetylmorphine, “smack”)
Cannabinoids are a group of chemicals (Fig. 7.10) that interact with cannabinoid receptors present principally in the brain. Natural cannabinoids are obtained from the inflorescences (flower clusters) of the plant Cannabis sativa (Fig. 7.11). The flower tops, leaves and resin of the cannabis plant are used in various combinations to produce marijuana, hashish, charas and ganja. Generally taken by inhalation and oral ingestion, cannabinoids are known for their effects on the cardiovascular system of the body.
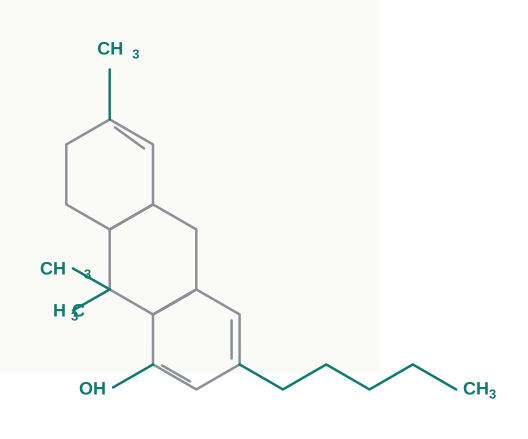
Fig. 7.10 – Skeletal structure of a cannabinoid molecule.
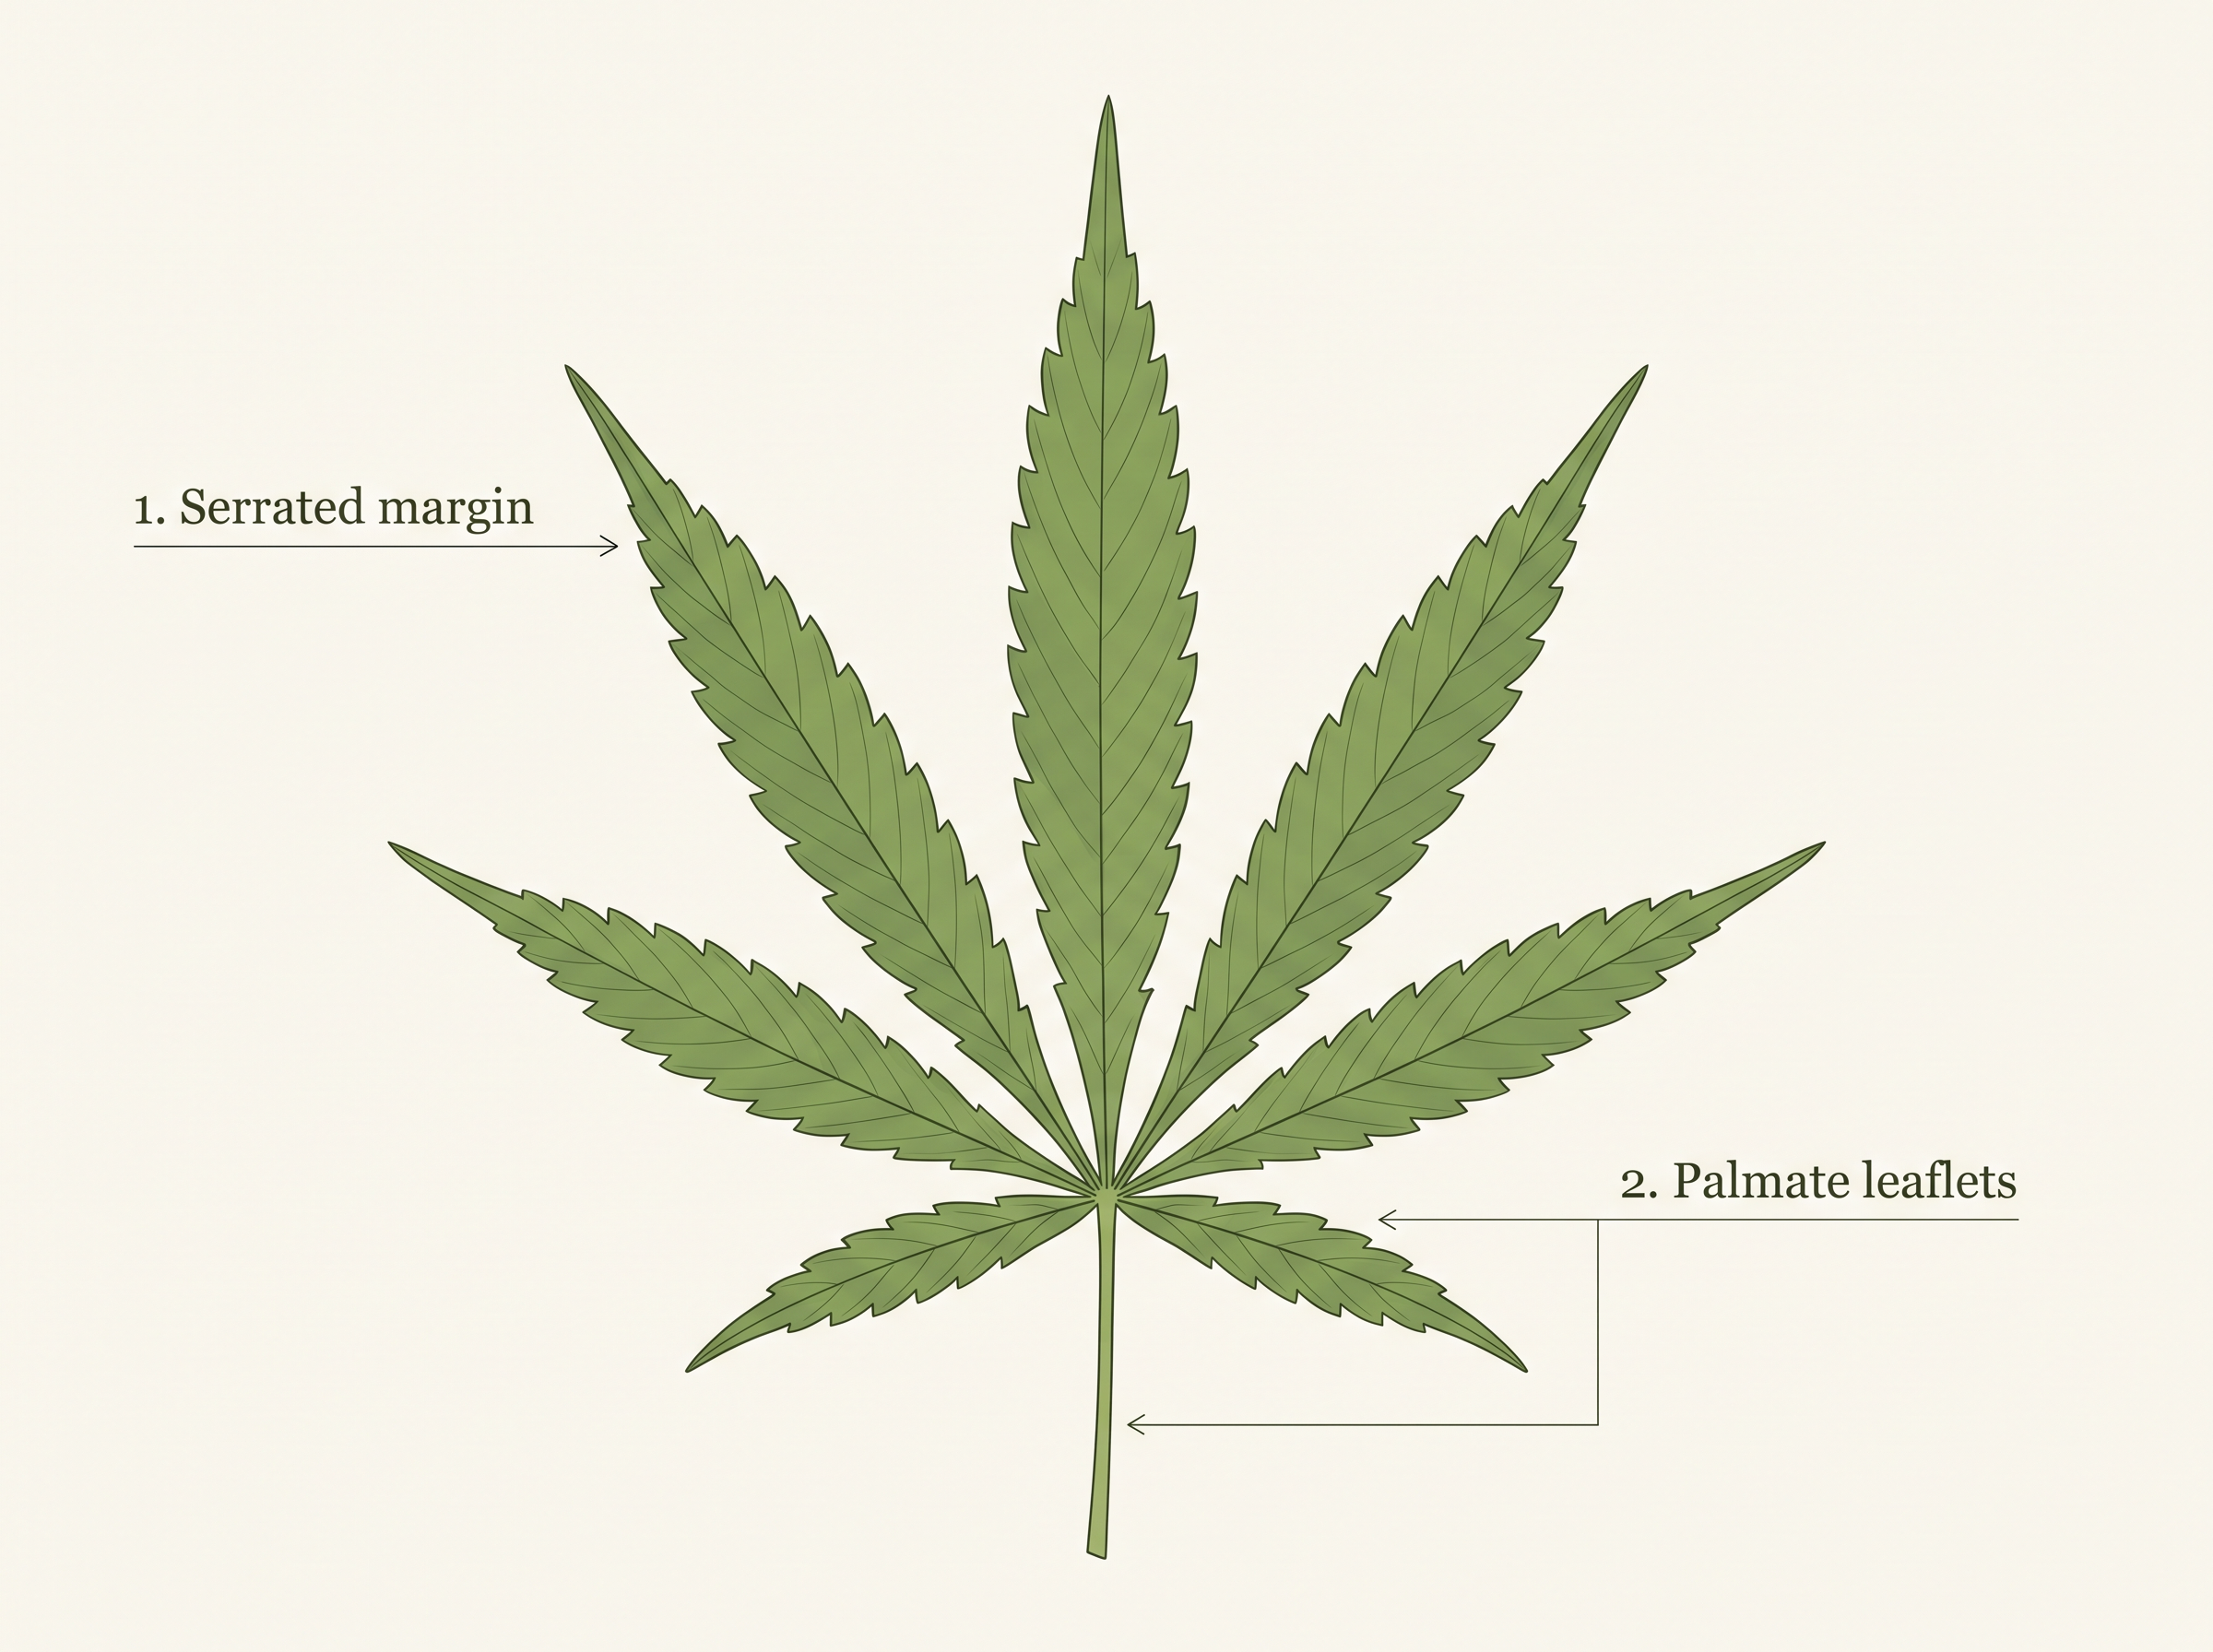
Fig. 7.11 – Leaves of Cannabis sativa.
Coca alkaloid, or cocaine, is obtained from the coca plant Erythroxylum coca, which is native to South America. Cocaine interferes with the transport of the neurotransmitter dopamine (a chemical messenger in the nervous system). Commonly called coke or crack, it is usually snorted. It has a potent stimulating action on the central nervous system, producing a sense of euphoria and increased energy. Excessive doses of cocaine cause hallucinations.
Other well-known plants with hallucinogenic properties are Atropa belladona and Datura (Fig. 7.12). These days, cannabinoids are also being abused by some sportspersons.
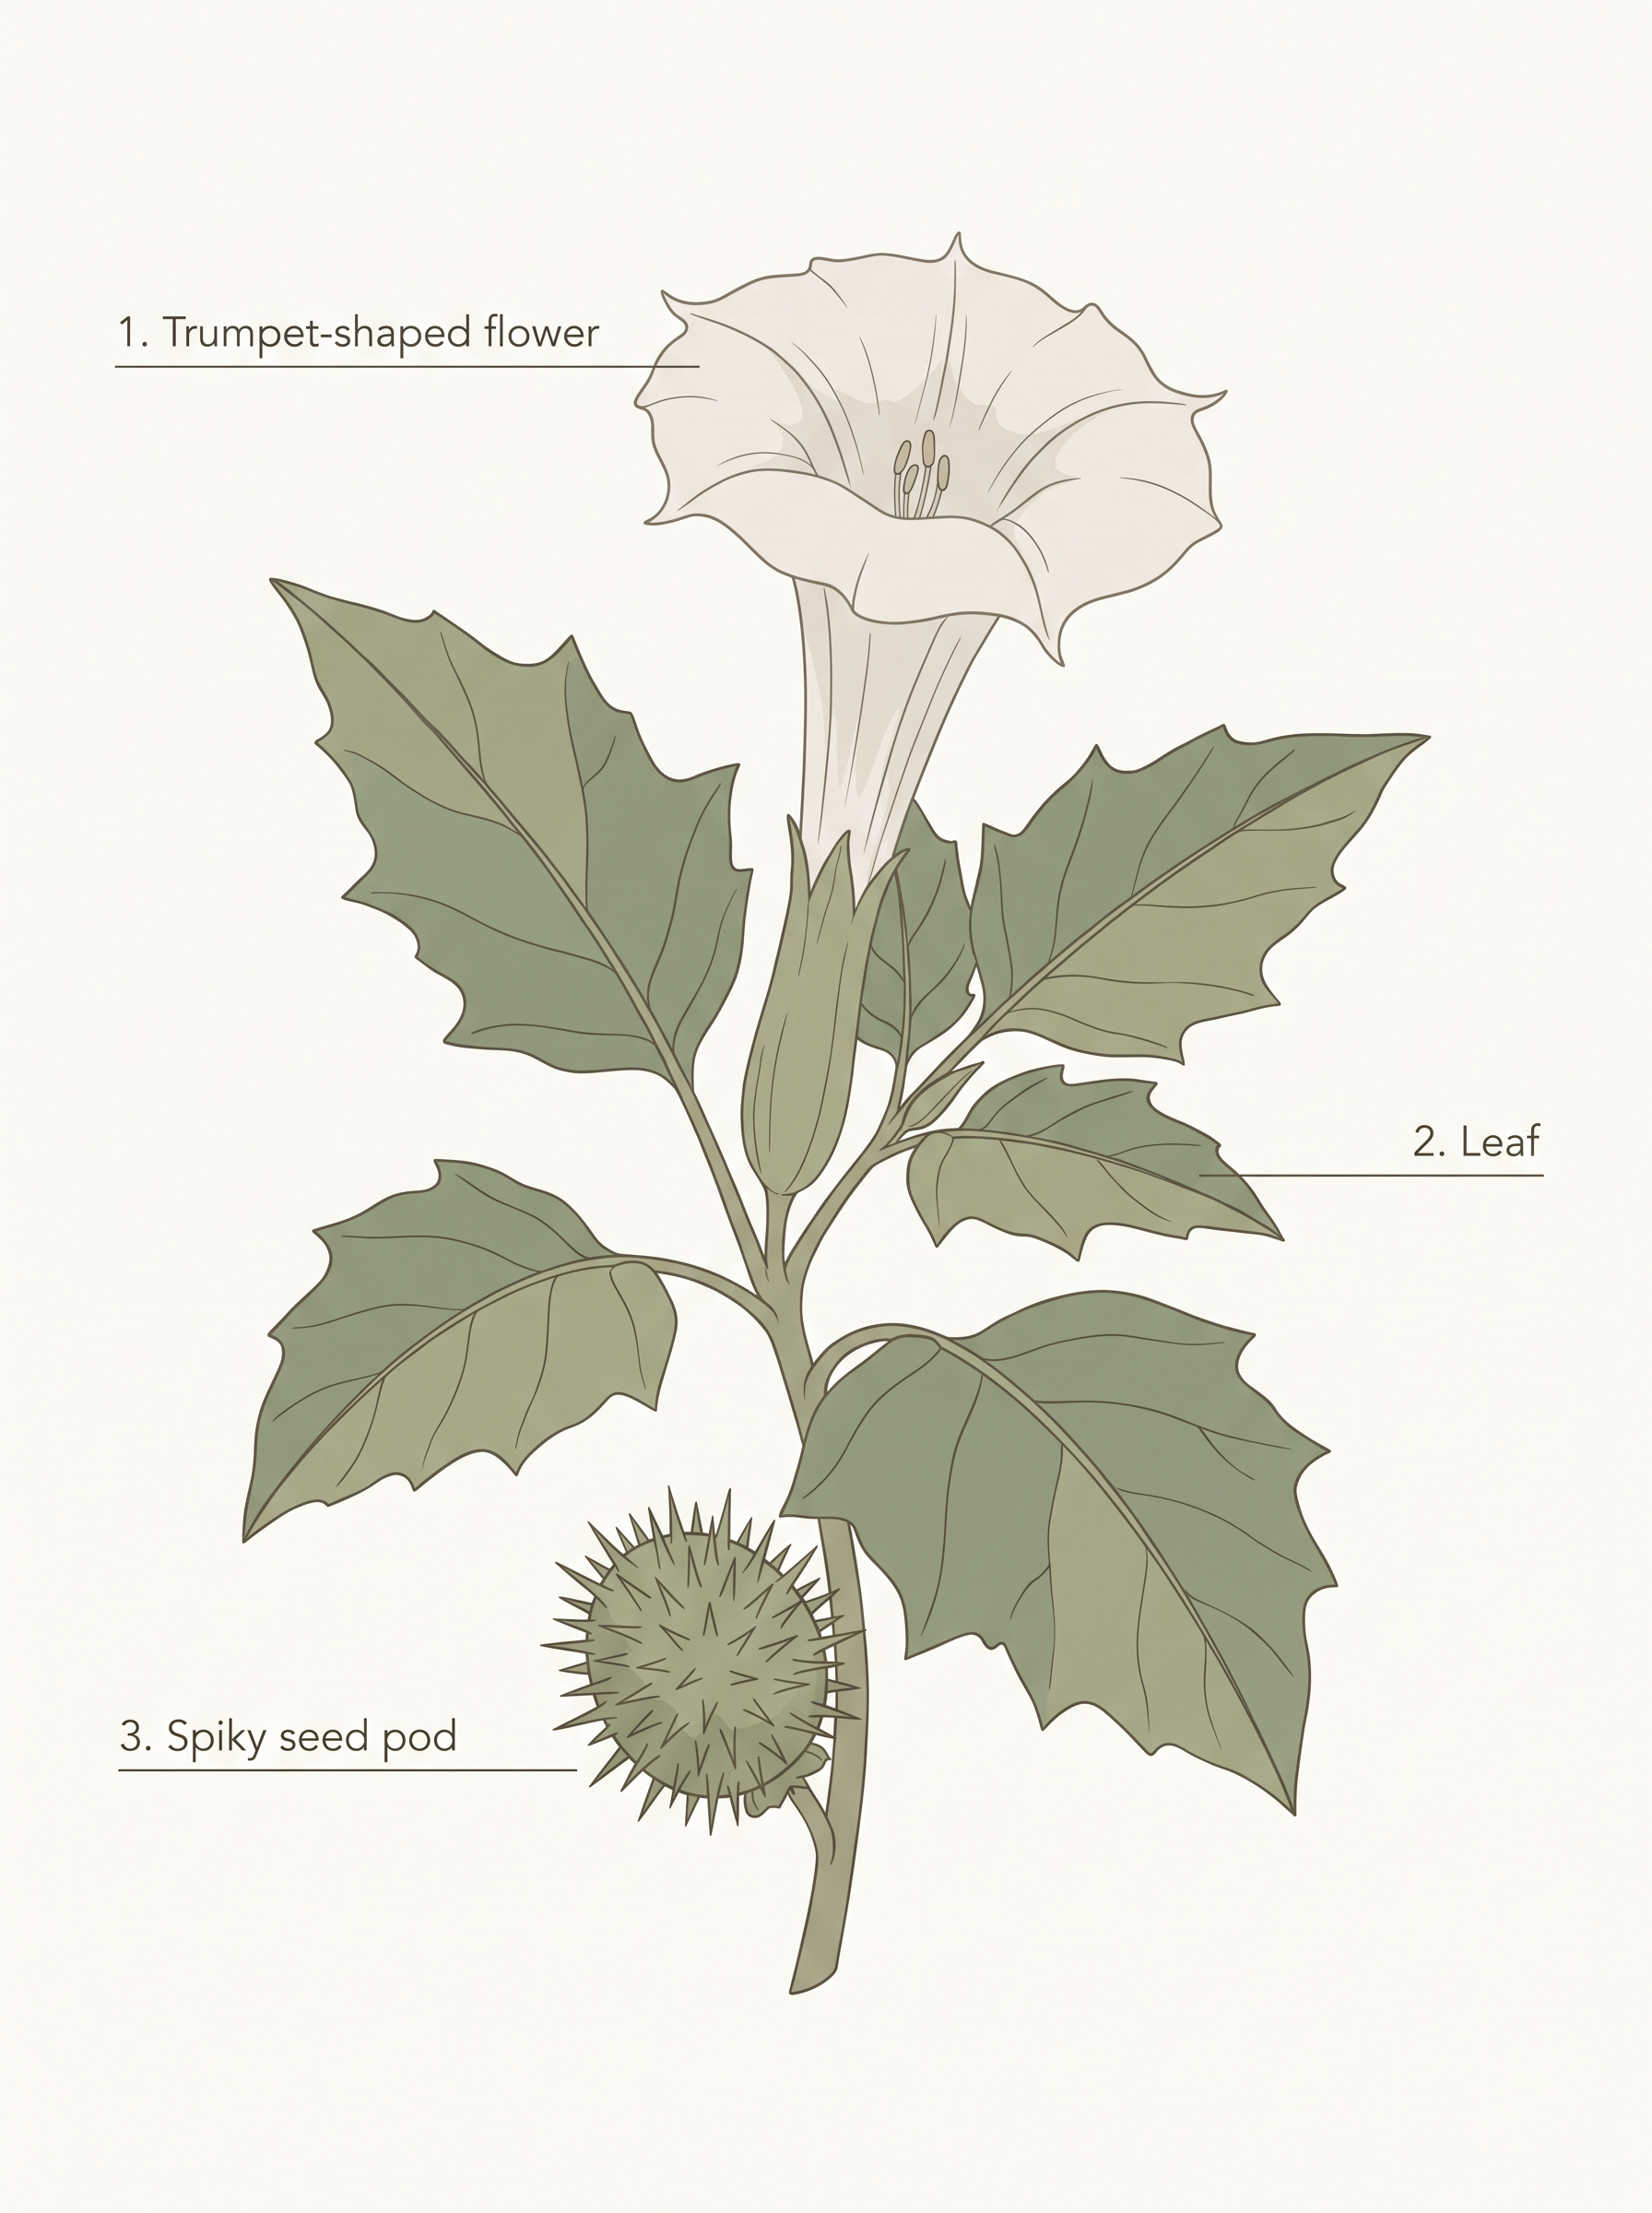
Fig. 7.12 – Flowering branch of Datura.
Several drugs that are normally used as medicines are also often abused. Drugs like barbiturates, amphetamines, benzodiazepines and other similar drugs — normally used to help patients cope with mental illnesses such as depression and insomnia — are frequently misused. Morphine, for instance, is a very effective sedative and painkiller, and is very useful in patients who have undergone surgery.
Many plants, fruits and seeds with hallucinogenic properties have been used for hundreds of years in folk-medicine, religious ceremonies and rituals all over the globe. When such substances are taken for a purpose other than medicinal use, or in amounts or frequency that impair one’s physical, physiological or psychological functions, it constitutes drug abuse.
Tobacco and Smoking
Smoking also paves the way to hard drugs. Tobacco has been used by human beings for more than 400 years. It is smoked, chewed, or used as a snuff. Tobacco contains a large number of chemical substances, including nicotine, an alkaloid.
Nicotine stimulates the adrenal gland to release adrenaline and nor-adrenaline into the blood circulation. (You may recall these hormones from your study of the endocrine system — they prepare the body for action.) Both of these raise the blood pressure and increase the heart rate.
Flowchart
FC 7.8 – How nicotine affects the body: nicotine (from tobacco) → stimulates adrenal gland → releases adrenaline and nor-adrenaline into blood → raised blood pressure + increased heart rate
Smoking is associated with an increased incidence of cancers of the lung, urinary bladder and throat, as well as bronchitis, emphysema, coronary heart disease and gastric ulcer. Tobacco chewing is associated with an increased risk of cancer of the oral cavity. Smoking also increases the carbon monoxide (CO) content in the blood and reduces the concentration of haembound oxygen, causing an oxygen deficiency in the body.
When one buys packets of cigarettes, one cannot miss the statutory warning printed on the packing, which warns against smoking and states how it is injurious to health. Yet smoking remains very common in society, among both the young and the old. Knowing the dangers of smoking and chewing tobacco, and its addictive nature, both the youth and the old need to avoid these habits. Any addict requires counselling and medical help to get rid of the habit.
7.5.1 Adolescence and Drug/Alcohol Abuse
Adolescence means both “a period” and “a process” during which a child becomes mature in terms of his or her attitudes and beliefs for effective participation in society. The period between 12 and 18 years of age may be thought of as adolescence. In other words, adolescence is a bridge linking childhood and adulthood.
Adolescence is accompanied by several biological and behavioural changes, and is therefore a very vulnerable phase in a person’s mental and psychological development.
Curiosity, the need for adventure and excitement, and the urge to experiment are common causes that push youngsters towards drug and alcohol use. A child’s natural curiosity motivates him or her to experiment, and this is made more complicated by the effects that might be perceived as “benefits” of alcohol or drug use.
Thus, the first use of drugs or alcohol may be out of curiosity or experimentation, but later the child starts using them to escape from facing problems. Of late, stress from the pressure to excel in academics or examinations has played a significant role in persuading youngsters to try alcohol and drugs.
The perception among the youth that it is “cool” or progressive to smoke, use drugs or drink alcohol is, in a way, another major cause for starting these habits. Television, movies, newspapers and the internet also help to promote this perception. Other associated factors include unstable or unsupportive family structures and peer pressure.
7.5.2 Addiction and Dependence
Because of the perceived benefits, drugs are frequently used again and again. The most important thing that a person often fails to realise is the inherent addictive nature of alcohol and drugs.
Addiction is a psychological attachment to certain effects — such as euphoria and a temporary feeling of well-being — associated with drugs and alcohol. These effects drive people to take drugs even when they are not needed, or even when their use has become self-destructive.
With repeated use of drugs, the tolerance level of the receptors present in our body increases. As a result, the receptors respond only to higher doses of the drug or alcohol, leading to greater intake and stronger addiction. However, it must be clearly kept in mind that even a single use of these drugs can be a fore-runner to addiction. In this way, the addictive potential of drugs and alcohol pulls the user into a vicious circle of regular use (abuse) that may be very hard to escape. In the absence of guidance or counselling, the person becomes addicted and dependent on their use.
Flowchart
FC 7.9 – The vicious circle of addiction: perceived benefit (euphoria, well-being) → repeated drug use → receptor tolerance increases → higher doses needed → greater intake → addiction and dependence → withdrawal symptoms on stopping → use resumed → back to repeated use
Dependence is the tendency of the body to show a characteristic and unpleasant withdrawal syndrome if the regular dose of drugs or alcohol is abruptly discontinued. This is marked by anxiety, shakiness, nausea and sweating, which may be relieved when the drug is used again. In some cases, withdrawal symptoms can be severe and even life-threatening, and the person may need medical supervision.
Dependence also leads the patient to ignore all social norms in order to get enough funds to satisfy their needs, and this results in many social adjustment problems.
7.5.3 Effects of Drug/Alcohol Abuse
The immediate adverse effects of drug and alcohol abuse show up as reckless behaviour, vandalism and violence. Excessive doses of drugs may lead to coma and death due to respiratory failure, heart failure or cerebral hemorrhage (bleeding in the brain). A combination of different drugs, or their intake along with alcohol, generally results in overdosing and even death.
The most common warning signs of drug and alcohol abuse among youth include a drop in academic performance, unexplained absence from school or college, lack of interest in personal hygiene, withdrawal, isolation, depression, fatigue, aggressive and rebellious behaviour, deteriorating relationships with family and friends, loss of interest in hobbies, changes in sleeping and eating habits, and fluctuations in weight and appetite.
There can even be far-reaching implications. If an abuser is unable to get money to buy drugs or alcohol, he or she may turn to stealing. Importantly, the adverse effects are not restricted to the user alone: at times, a drug or alcohol addict becomes the cause of mental and financial distress for their entire family and friends.
Infections and Long-term Damage
Those who take drugs intravenously (by direct injection into a vein using a needle and syringe) are far more likely to acquire serious infections like AIDS and Hepatitis B. The viruses responsible for these diseases are transferred from one person to another by sharing infected needles and syringes. Both AIDS and Hepatitis B infections are chronic and ultimately fatal, and both can also be transmitted through sexual contact or infected blood.
The use of alcohol during adolescence may also have long-term effects, and could lead to heavy drinking in adulthood. Chronic use of drugs and alcohol damages the nervous system and the liver (causing cirrhosis, a scarring of the liver). The use of drugs and alcohol during pregnancy is also known to adversely affect the foetus.
Misuse of Drugs in Sports
Another misuse of drugs is what certain sportspersons do to enhance their performance. They (mis)use narcotic analgesics, anabolic steroids, diuretics and certain hormones to increase muscle strength and bulk and to promote aggressiveness, and thereby boost athletic performance.
The side-effects of anabolic steroids differ between the sexes. In females, they include masculinisation (developing male-like features), increased aggressiveness, mood swings, depression, abnormal menstrual cycles, excessive hair growth on the face and body, enlargement of the clitoris, and deepening of the voice.
In males, they include acne, increased aggressiveness, mood swings, depression, reduction in the size of the testicles, decreased sperm production, potential for kidney and liver dysfunction, breast enlargement, premature baldness, and enlargement of the prostate gland. Many of these effects may become permanent with prolonged use. In an adolescent male or female, severe facial and body acne, along with premature closure of the growth centres of the long bones, may result in stunted growth.
7.5.4 Prevention and Control
The age-old adage “prevention is better than cure” holds true here as well. It is also true that habits such as smoking, or taking drugs or alcohol, are more likely to begin at a young age, particularly during adolescence. Hence, it is best to identify the situations that may push an adolescent towards the use of drugs or alcohol, and to take remedial measures well in time.
In this regard, parents and teachers have a special responsibility. Parenting that combines high levels of nurturance with consistent discipline has been associated with a lowered risk of substance (alcohol, drugs or tobacco) abuse. Some of the measures that are particularly useful for the prevention and control of alcohol and drug abuse among adolescents are given below.
First, avoid undue peer pressure. Every child has his or her own choice and personality, which should be respected and nurtured. A child should not be pushed unduly to perform beyond his or her threshold limits — be it in studies, sports or other activities.
Second, education and counselling. The child should be educated and counselled to face problems and stresses, and to accept disappointments and failures as a part of life. It is also worthwhile to channelise the child’s energy into healthy pursuits like sports, reading, music, yoga and other extracurricular activities.
Third, seeking help from parents and peers. Help from parents and peers should be sought immediately so that they can guide the young person appropriately. Help may also be sought from close and trusted friends. Besides getting proper advice to sort out problems, this helps young people to vent their feelings of anxiety and guilt.
Fourth, looking for danger signs. Alert parents and teachers need to look for and identify the danger signs discussed earlier. Even friends, if they find someone using drugs or alcohol, should not hesitate to bring this to the notice of parents or teachers in the best interests of the person concerned. Appropriate measures can then be taken to diagnose the problem and its underlying causes, and to begin proper remedial steps or treatment.
Fifth, seeking professional and medical help. A great deal of help is available in the form of highly qualified psychologists and psychiatrists, and de-addiction and rehabilitation programmes, to help individuals who have unfortunately fallen into the quagmire of drug or alcohol abuse. With such help, and with sufficient effort and will power, the affected individual can get rid of the problem completely and lead a perfectly normal and healthy life.
7.6 Summary
Health is not merely the absence of disease. It is a state of complete physical, mental, social and psychological well-being.
Many diseases — typhoid, cholera, pneumonia, fungal infections of the skin, malaria and others — cause great distress to human beings. Vector-borne diseases like malaria, especially the type caused by Plasmodium falciparum, can prove fatal if not treated.
Besides personal cleanliness and hygiene, public health measures are very helpful in preventing these diseases. These include proper disposal of waste, decontamination of drinking water, control of vectors like mosquitoes, and immunisation.
Our immune system plays the major role in protecting us when we are exposed to disease-causing agents.
The innate defences of the body — the skin, mucous membranes, antimicrobial substances in tears and saliva, and phagocytic cells — help block the entry of pathogens into the body.
If pathogens do manage to enter, specific antibodies (the humoral immune response) and specific cells (the cell-mediated immune response) act to kill these pathogens.
The immune system has memory. On a later exposure to the same pathogen, the immune response is rapid and more intense. This memory is the basis of the protection given by vaccination and immunisation.
Flowchart
FC 7.10 – The body’s line of defence: pathogen approaches → innate barriers (skin, mucus, tears/saliva, phagocytes) block entry → if pathogen gets in → acquired immunity responds (antibodies = humoral response; T-cells = cell-mediated response) → pathogen destroyed → memory cells formed → faster, stronger response on next exposure
Among the other major diseases, AIDS and cancer kill a large number of people worldwide. AIDS, caused by the human immuno-deficiency virus (HIV), is fatal, but it can be prevented if certain precautions are taken.
Many cancers are curable if they are detected early and appropriate therapeutic measures are taken.
Drug and alcohol abuse among youth and adolescents is becoming another cause of concern. Because of the addictive nature of alcohol and drugs, and their perceived benefits like relief from stress, a person may try them in the face of peer pressure and examination- or competition-related stress, and in doing so may become addicted.
Education about their harmful effects, counselling, and seeking immediate professional and medical help can relieve the individual from these evils.
7.7 Points to Ponder
If health means complete physical, mental and social well-being, can a person who is physically free of disease still be described as unhealthy? What might that look like?
Our immune system depends on being able to tell “self” from “nonself.” What could go wrong in the body if this ability failed, and how is this connected to auto-immune diseases like rheumatoid arthritis?
A vaccine works because the immune system “remembers” a pathogen. Why, then, do we need a fresh vaccine for some diseases (like influenza) year after year, while a single vaccine protects us for life against others?
More children in clean, protected city environments seem to suffer from allergies and asthma. What does this suggest about the relationship between early exposure to microbes and a well-balanced immune system?
AIDS spreads mostly through conscious human behaviour rather than by accident. How does this change the way we should approach its prevention compared with a disease like the common cold?
Why is society urged to support HIV/AIDS-infected people rather than isolate them, and how does isolating them actually work against controlling the disease?
Cancer cells lose the property of contact inhibition that normal cells possess. Why might a single lost control mechanism have such devastating, body-wide consequences?
The first use of a drug is often out of simple curiosity, yet it can lead to a vicious circle of addiction. What responsibility do families, schools, media and society share in either pushing a young person towards this circle or protecting them from it?
7.8 NCERT Questions
What are the various public health measures, which you would suggest as safeguard against infectious diseases?
In which way has the study of biology helped us to control infectious diseases?
How does the transmission of each of the following diseases take place?
- Amoebiasis
- Malaria
- Ascariasis
- Pneumonia
What measure would you take to prevent water-borne diseases?
Discuss with your teacher what ‘a suitable gene’ means, in the context of DNA vaccines.
Name the primary and secondary lymphoid organs.
The following are some well-known abbreviations, which have been used in this chapter. Expand each one to its full form:
- MALT
- CMI
- AIDS
- NACO
- HIV
Differentiate the following and give examples of each:
- Innate and acquired immunity
- Active and passive immunity
Draw a well-labelled diagram of an antibody molecule.
What are the various routes by which transmission of human immuno-deficiency virus takes place?
What is the mechanism by which the AIDS virus causes deficiency of the immune system of the infected person?
How is a cancerous cell different from a normal cell?
Explain what is meant by metastasis.
List the harmful effects caused by alcohol/drug abuse.
Do You think that friends can influence one to take alcohol/drugs? If yes, how may one protect himself/herself from such an influence?
Why is it that once a person starts taking alcohol or drugs, it is difficult to get rid of this habit? Discuss it with your teacher.
In your view, what motivates youngsters to take to alcohol or drugs, and how can this be avoided?
7.9 Check Your Concepts
Assertion–Reason. Assertion: The common cold does not affect the lungs. Reason: Rhino viruses infect the nose and respiratory passage but not the lungs. State whether the assertion and reason are true, and whether the reason correctly explains the assertion.
Why must a pathogen that infects the gut be able to survive a low pH and resist digestive enzymes? Explain the link between this adaptation and the pathogen’s ability to cause disease.
Arrange the following stages of the Plasmodium life cycle in the correct sequence: (a) parasites multiply in liver cells; (b) sporozoites injected by mosquito bite; (c) rupture of RBCs and release of haemozoin; (d) gametocytes taken up by mosquito during a blood meal; (e) sporozoites stored in the mosquito’s salivary glands.
Both the housefly (in amoebiasis) and the female Anopheles mosquito (in malaria) are involved in spreading disease. Why is one called a mechanical carrier and the other a biological vector? What is the key difference?
What happens to the haembound oxygen level in the blood of a chronic smoker, and why? Trace the effect of carbon monoxide from smoke to the resulting oxygen deficiency in the body.
Match the disease with its causative organism:
| Column A | Column B |
|---|---|
| a. Typhoid | i. Wuchereria bancrofti |
| b. Ringworm | ii. Salmonella typhi |
| c. Filariasis | iii. Entamoeba histolytica |
| d. Amoebiasis | iv. Microsporum |
Name the four types of barriers that make up innate immunity, and give one example of each.
Why is the secondary immune response faster and more intense than the primary response? What property of the immune system makes this possible?
An antibody is represented as \(H_2L_2\). Explain what this notation means, and relate the structure of the antibody to its ability to bind antigens.
Differentiate between humoral immunity and cell-mediated immunity, and state which type of lymphocyte is chiefly responsible for each.
A newborn infant has an immune system that is not yet fully active. Explain how colostrum protects the infant, and state whether this is an example of active or passive immunity.
In the case of a snakebite or tetanus, why is the patient given preformed antibodies rather than a vaccine? What is this type of immunisation called?
Assertion–Reason. Assertion: More children in metro cities suffer from allergies and asthma. Reason: A very protected, clean environment early in life may lower immunity and increase sensitivity to allergens. Comment on both statements and their relationship.
What happens in the body during an auto-immune disease? Name one common example of such a disease.
Why does the thymus shrink after puberty, yet it is described as a primary lymphoid organ? What role does it play, and in the maturation of which cells?
HIV is called a retrovirus. Explain the role of the enzyme reverse transcriptase in its replication, and describe how the virus ultimately causes immunodeficiency.
Distinguish between HIV and AIDS. Why can a person be HIV-positive for years before developing AIDS?
Normal cells show contact inhibition, but cancer cells do not. Explain how the loss of this single property leads to tumour formation, and why metastasis makes malignant tumours especially dangerous.
Differentiate between a viral oncogene and a proto-oncogene (cellular oncogene). How can a normal gene present in our own cells contribute to cancer?
Heroin and cocaine are both abused drugs, yet they act in opposite ways on the body. Compare their sources, the systems they act on, and their broad effects.
Explain the difference between addiction and dependence. Using the idea of receptor tolerance and the withdrawal syndrome, describe why breaking a drug habit is so difficult.
Certain sportspersons misuse anabolic steroids. List three side-effects each that may occur in females and in males, and explain why the effects on an adolescent may include stunted growth.