Chapter 2: Human Reproduction
For thousands of years, one of the deepest questions humans asked was also one of the simplest: where does a new life actually begin? People could see that babies came from mothers and fathers, but no one had ever seen the very first cells from which a human being grows.
The first clue arrived in the 1670s, when the Dutch lens-maker Antonie van Leeuwenhoek pointed his handmade microscope at a drop of semen and saw thousands of tiny, tail-lashing “animalcules” swimming across his slide. He had discovered sperm — the male gamete — without knowing what it was for.
The other half of the answer took another century and a half. In 1827, the Estonian-born biologist Karl Ernst von Baer carefully opened the ovary of a dog and, for the first time, identified the mammalian egg — a single ovum, smaller than a full stop, sitting inside a fluid-filled follicle. Two cells, discovered 150 years apart, turned out to be the starting point of every mammal, including us.
In this chapter you will meet both of these cells, the organs that build them, and the remarkable chain of events — from the meeting of a sperm and an ovum to the birth of a baby nine months later — that carries a single cell all the way to a fully formed human being.
Fig. 2.0 – Fertilisation and the beginning of human life.
By the end of this chapter, you will be able to answer each of these questions.
2.1 The Male Reproductive System
The male reproductive system lies in the lower part of the trunk, in the region called the pelvis. It is built from a pair of testes (singular: testis), a set of accessory ducts that carry sperm, a group of accessory glands that add fluids, and the external genitalia. Together these parts make, mature, store and finally deliver the male gamete — the sperm. The overall arrangement is shown in Fig. 2.1(a).
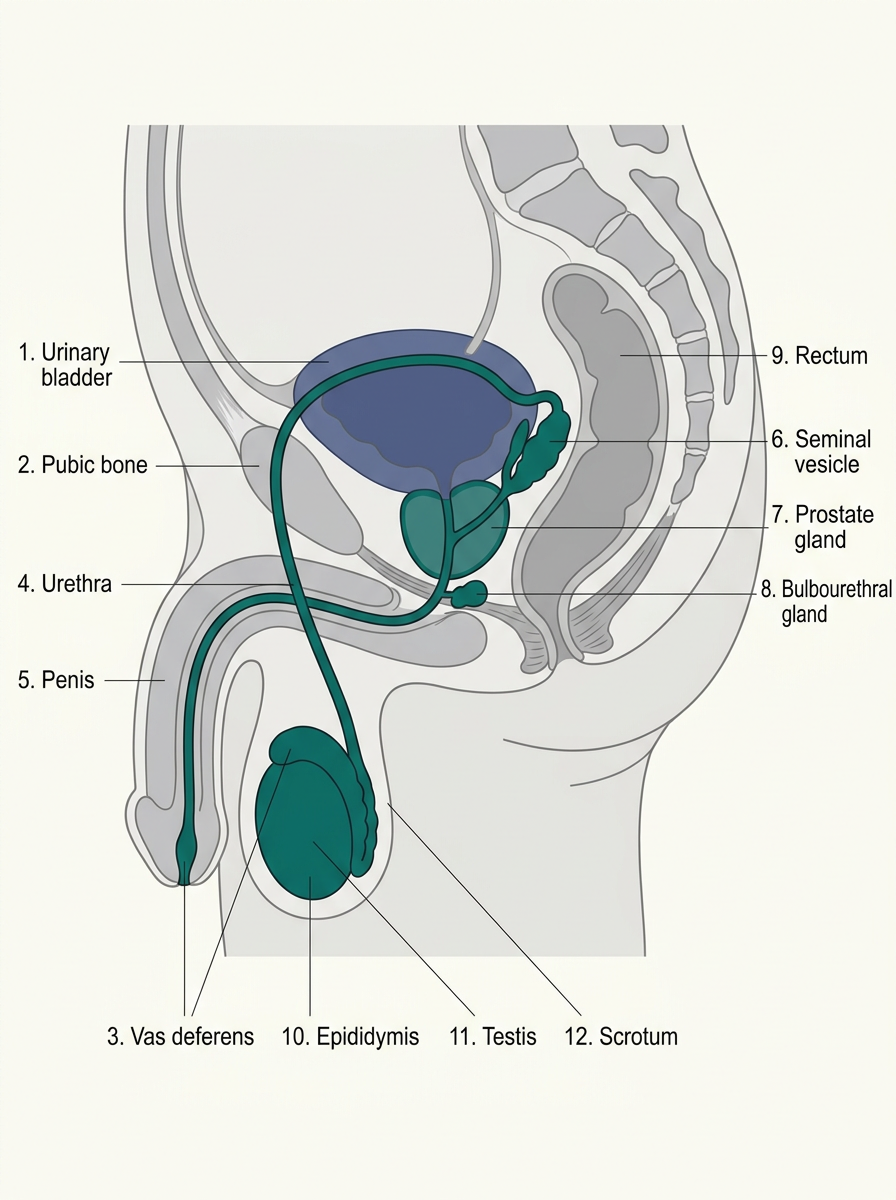
Fig. 2.1a – Male reproductive system in the pelvis.
The Testes and the Scrotum
The testes are the primary sex organs of the male, because they produce the sperm. Instead of sitting inside the abdominal cavity like most organs, they hang outside the body in a small skin pouch called the scrotum.
This unusual position has a clear purpose. The scrotum keeps the testes about 2–2.5°C cooler than the normal internal body temperature. This slightly lower temperature is essential for spermatogenesis — the formation of sperm — which cannot proceed normally at full body heat.
In an adult, each testis is oval and firm, about 4 to 5 cm long and 2 to 3 cm wide, and is wrapped in a dense protective covering. Inside, each testis is divided into about 250 compartments called testicular lobules, as seen in Fig. 2.2(b).
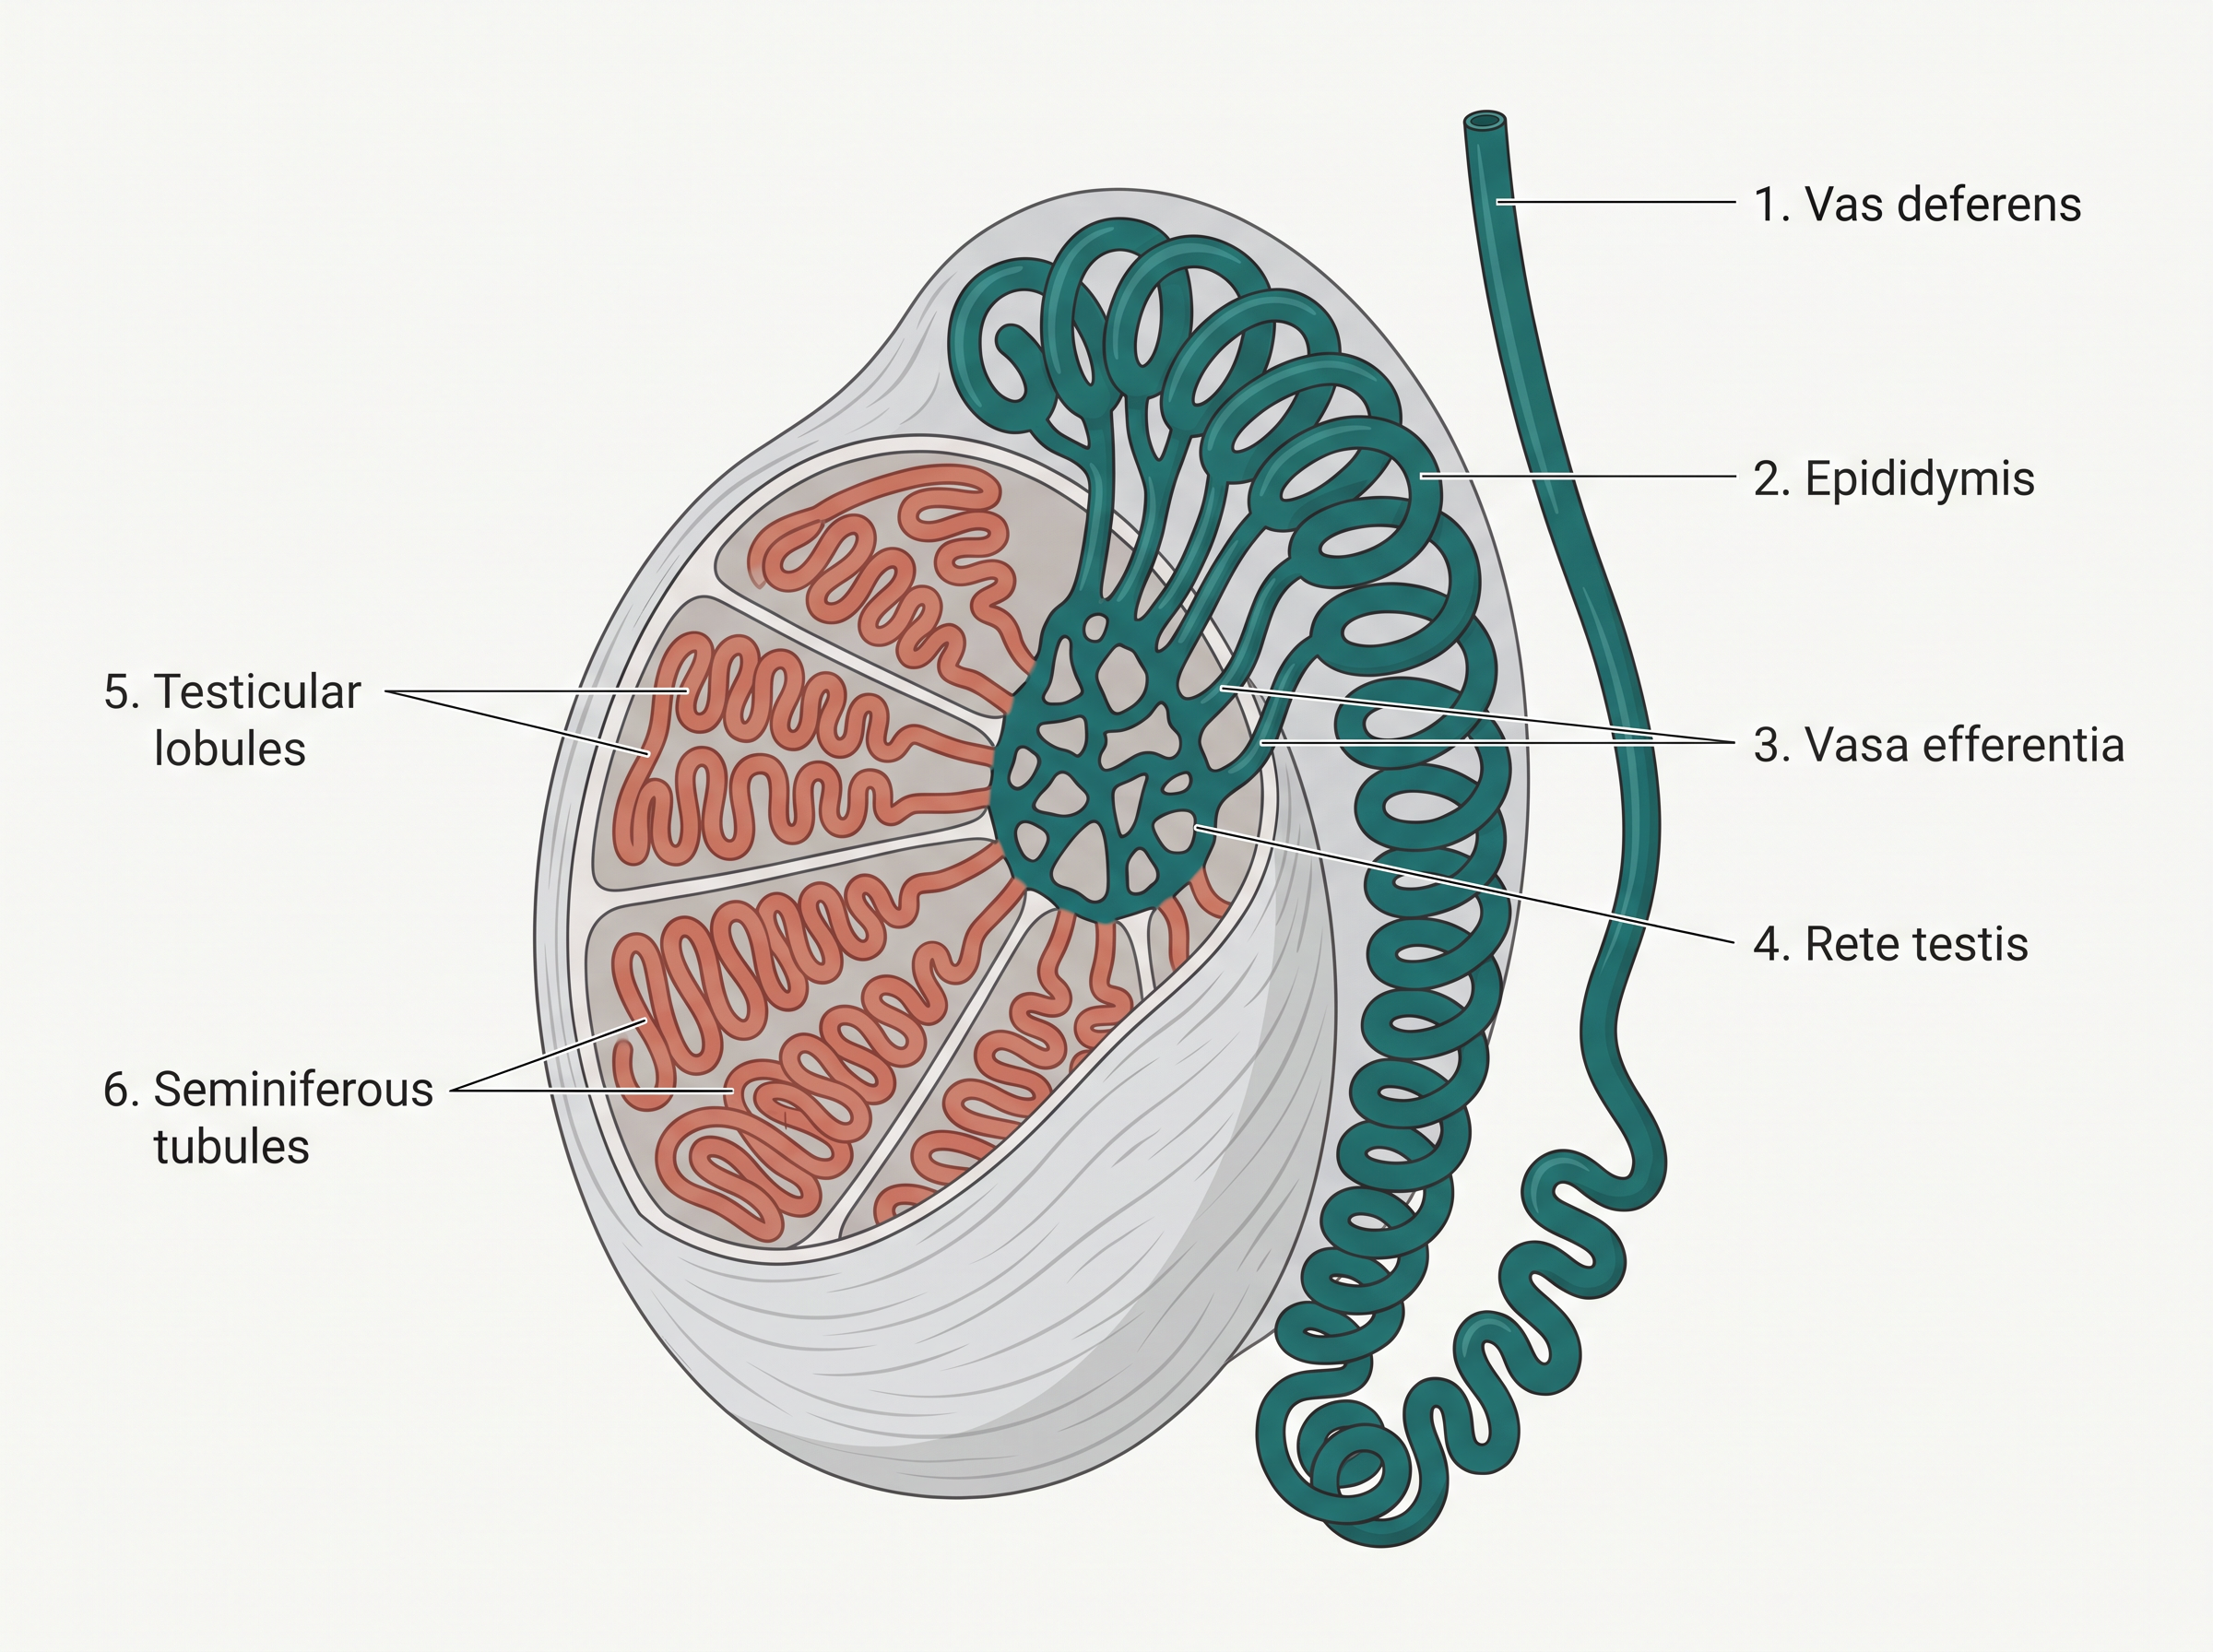
Fig. 2.2b – Internal ducts of the testis.
Inside the Seminiferous Tubules
Each lobule contains one to three tightly coiled seminiferous tubules, and it is here — inside these coiled tubes — that sperms are actually made. The inner lining of every seminiferous tubule is formed by two kinds of cells, shown in Fig. 2.3: the male germ cells (spermatogonia), and the Sertoli cells.
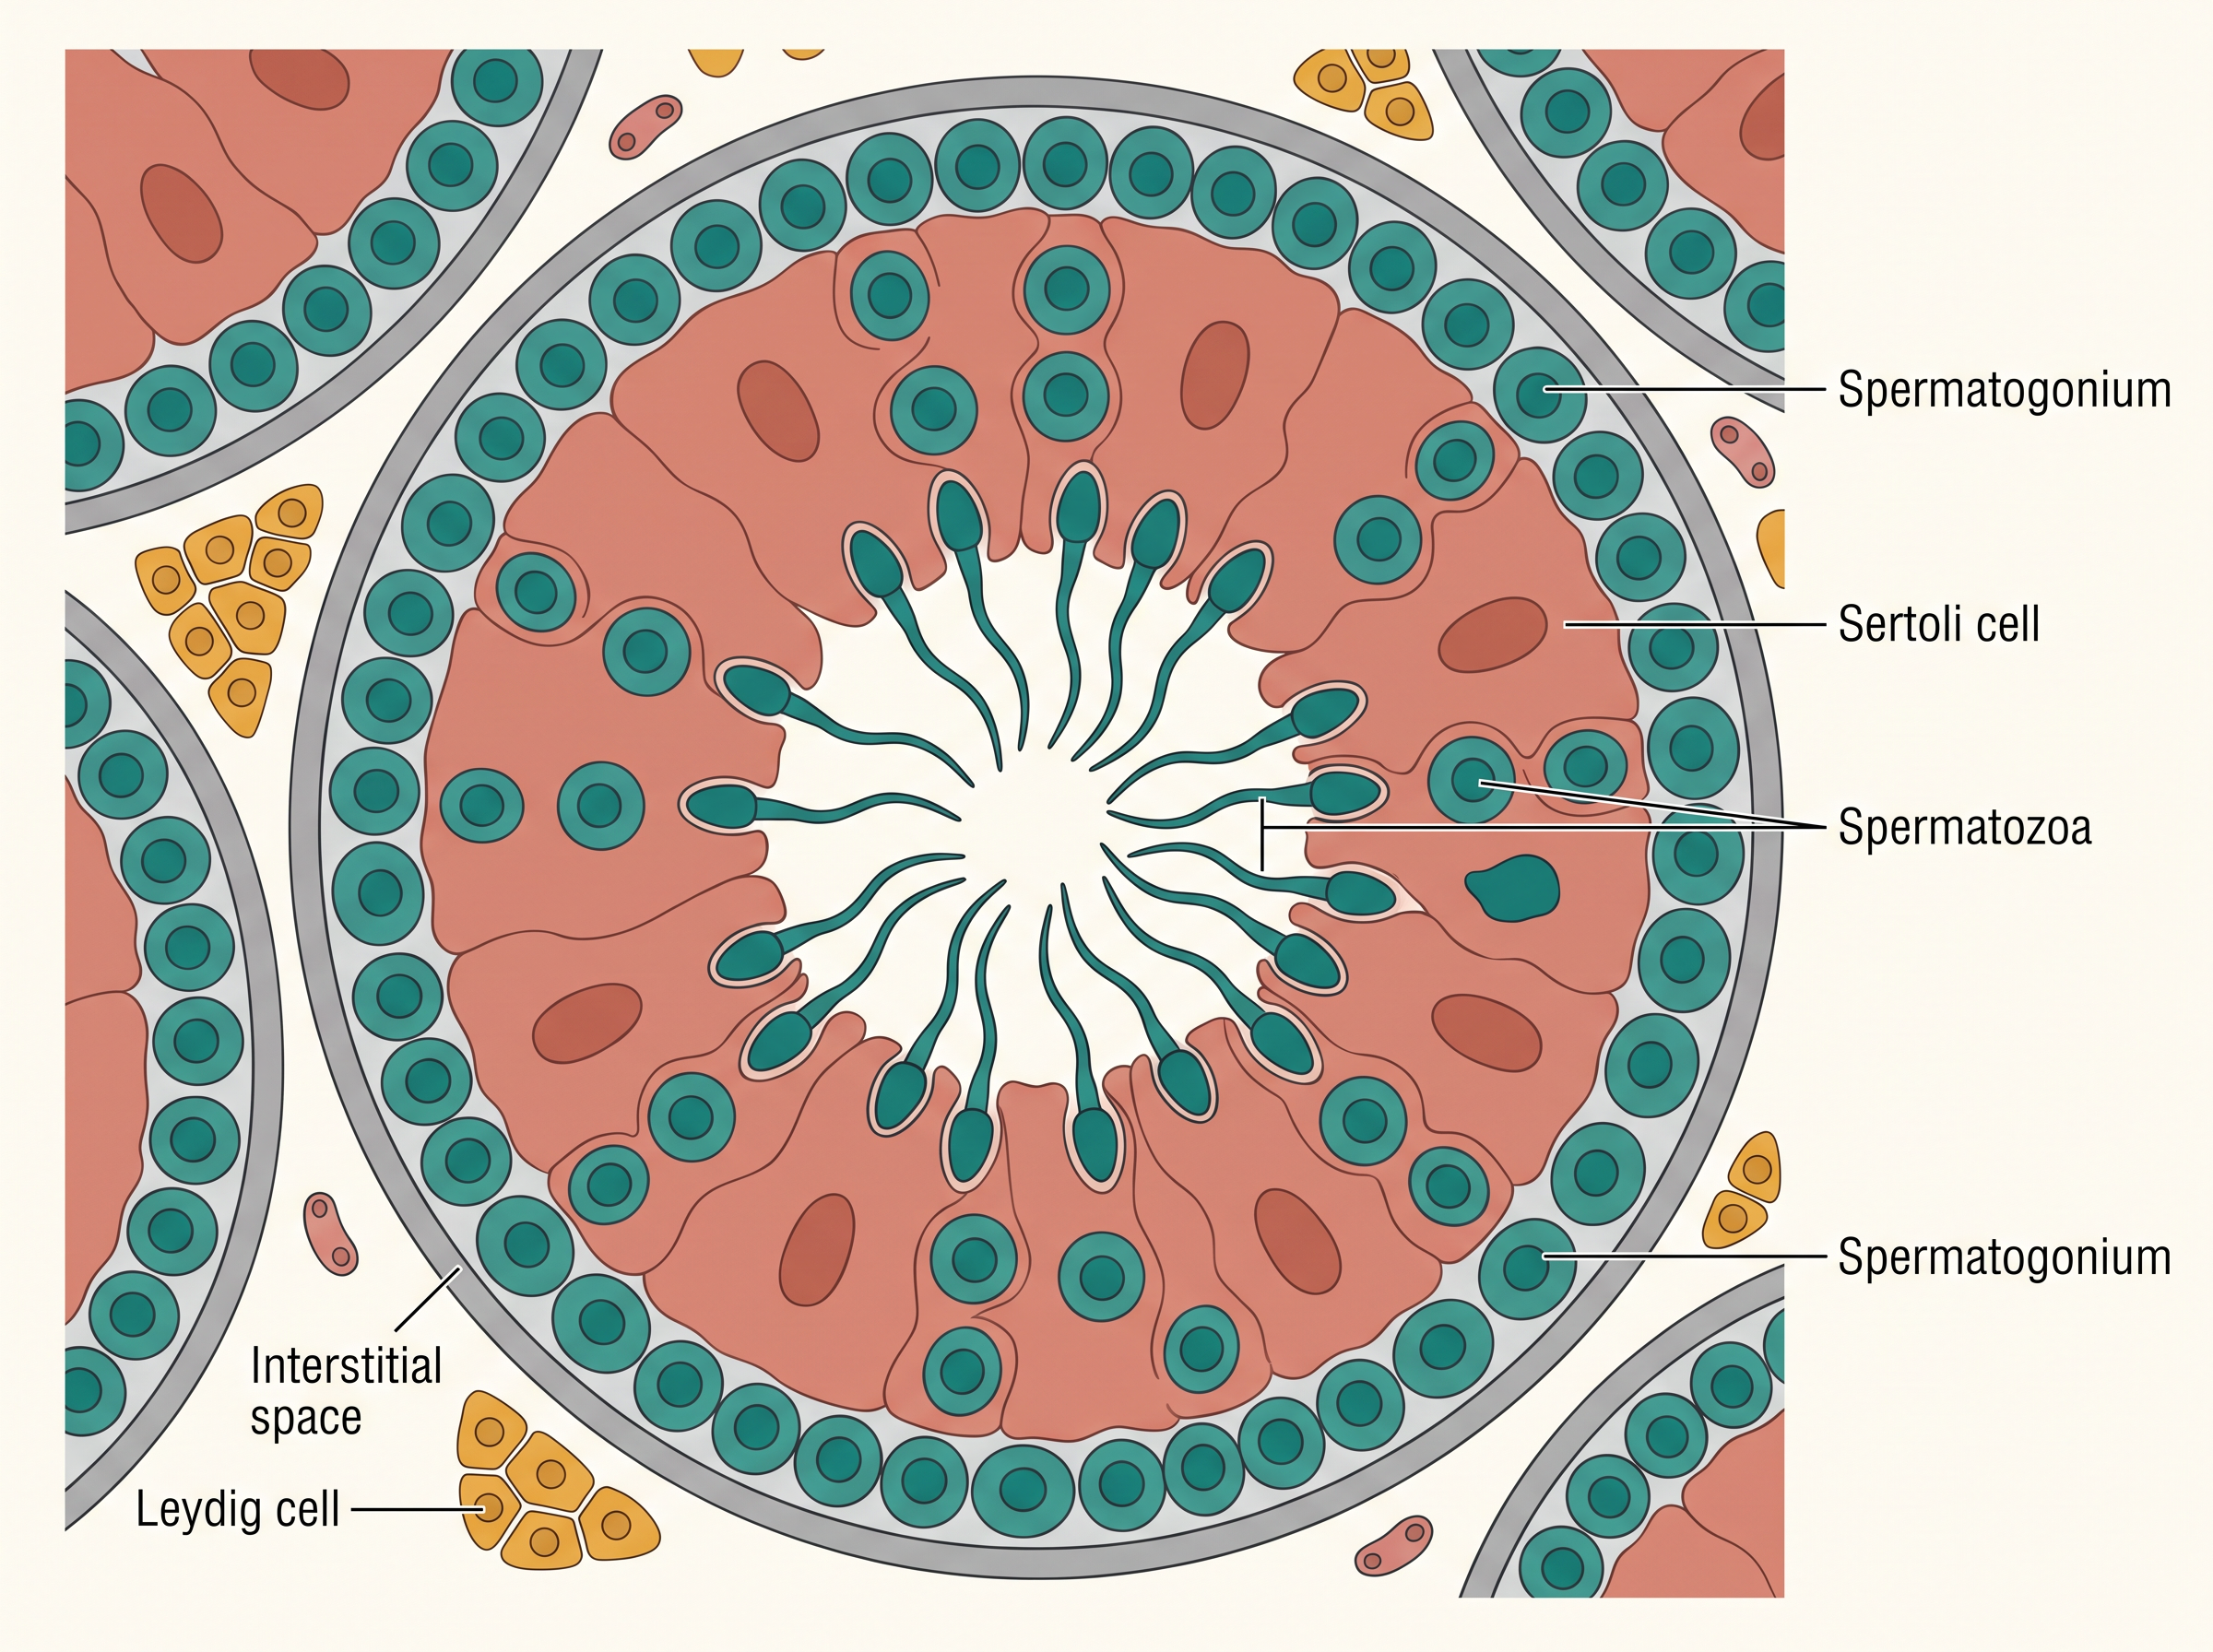
Fig. 2.3 – Sectional view of a seminiferous tubule.
The two cell types have very different jobs. The male germ cells (spermatogonia) divide and, through meiotic divisions, eventually give rise to sperms. The Sertoli cells do not become sperm; instead they nourish the developing germ cells, acting like nurse cells that feed the future sperm.
Between the seminiferous tubules lie the interstitial spaces. These spaces contain small blood vessels and a special group of cells called interstitial cells or Leydig cells (Fig. 2.3). The Leydig cells make and release the male sex hormones — the chemical messengers called androgens — which drive many male reproductive functions. A few immune-defence cells are also present in these spaces.
The Sperm-Carrying Ducts
Once formed, sperms must be moved out of the testis. This is the task of the male sex accessory ducts — the rete testis, vasa efferentia, epididymis and vas deferens (Fig. 2.2b).
The seminiferous tubules first empty into the rete testis. From the rete testis, the sperms pass into the vasa efferentia, which leave the testis and open into the epididymis running along the back surface of each testis. The epididymis then leads into the vas deferens, a long tube that climbs up into the abdomen and loops over the urinary bladder. Near the bladder, the vas deferens is joined by a duct from the seminal vesicle, and together they open into the urethra as the ejaculatory duct (Fig. 2.1a).
Along this whole route the ducts store the sperms and transport them toward the exterior. The urethra begins at the urinary bladder and runs through the penis to its outer opening, the urethral meatus. Because this pathway must be followed in the correct order — and is a favourite for sequence-ordering questions — it is summarised in FC 2.1.
Flowchart
FC 2.1 – Path of sperm from formation to exit: seminiferous tubules → rete testis → vasa efferentia → epididymis → vas deferens → ejaculatory duct → urethra → urethral meatus
The Penis and the Accessory Glands
The penis is the male external genitalia (Fig. 2.1a, 2.2b). It is built of a special erectile tissue that lets the penis stiffen (erection), which helps in insemination — the delivery of sperm into the female reproductive tract. The swollen tip of the penis, the glans penis, is covered by a loose fold of skin called the foreskin.
The male accessory glands add fluids to the sperm. They include a pair of seminal vesicles, a single prostate, and a pair of bulbourethral glands (Fig. 2.1a, 2.2b). The combined secretions of these glands form the seminal plasma, a fluid rich in fructose (a sugar that feeds the sperm), calcium, and certain enzymes. The bulbourethral gland’s secretion additionally lubricates the penis.
2.2 The Female Reproductive System
The female reproductive system is made up of a pair of ovaries, together with a pair of oviducts, a uterus, a cervix, a vagina and the external genitalia — all lying in the pelvic region (Fig. 2.4a). Along with a pair of mammary glands, these parts work together, in both structure and function, to carry out ovulation (release of the egg), fertilisation, pregnancy, birth and the feeding and care of the child.
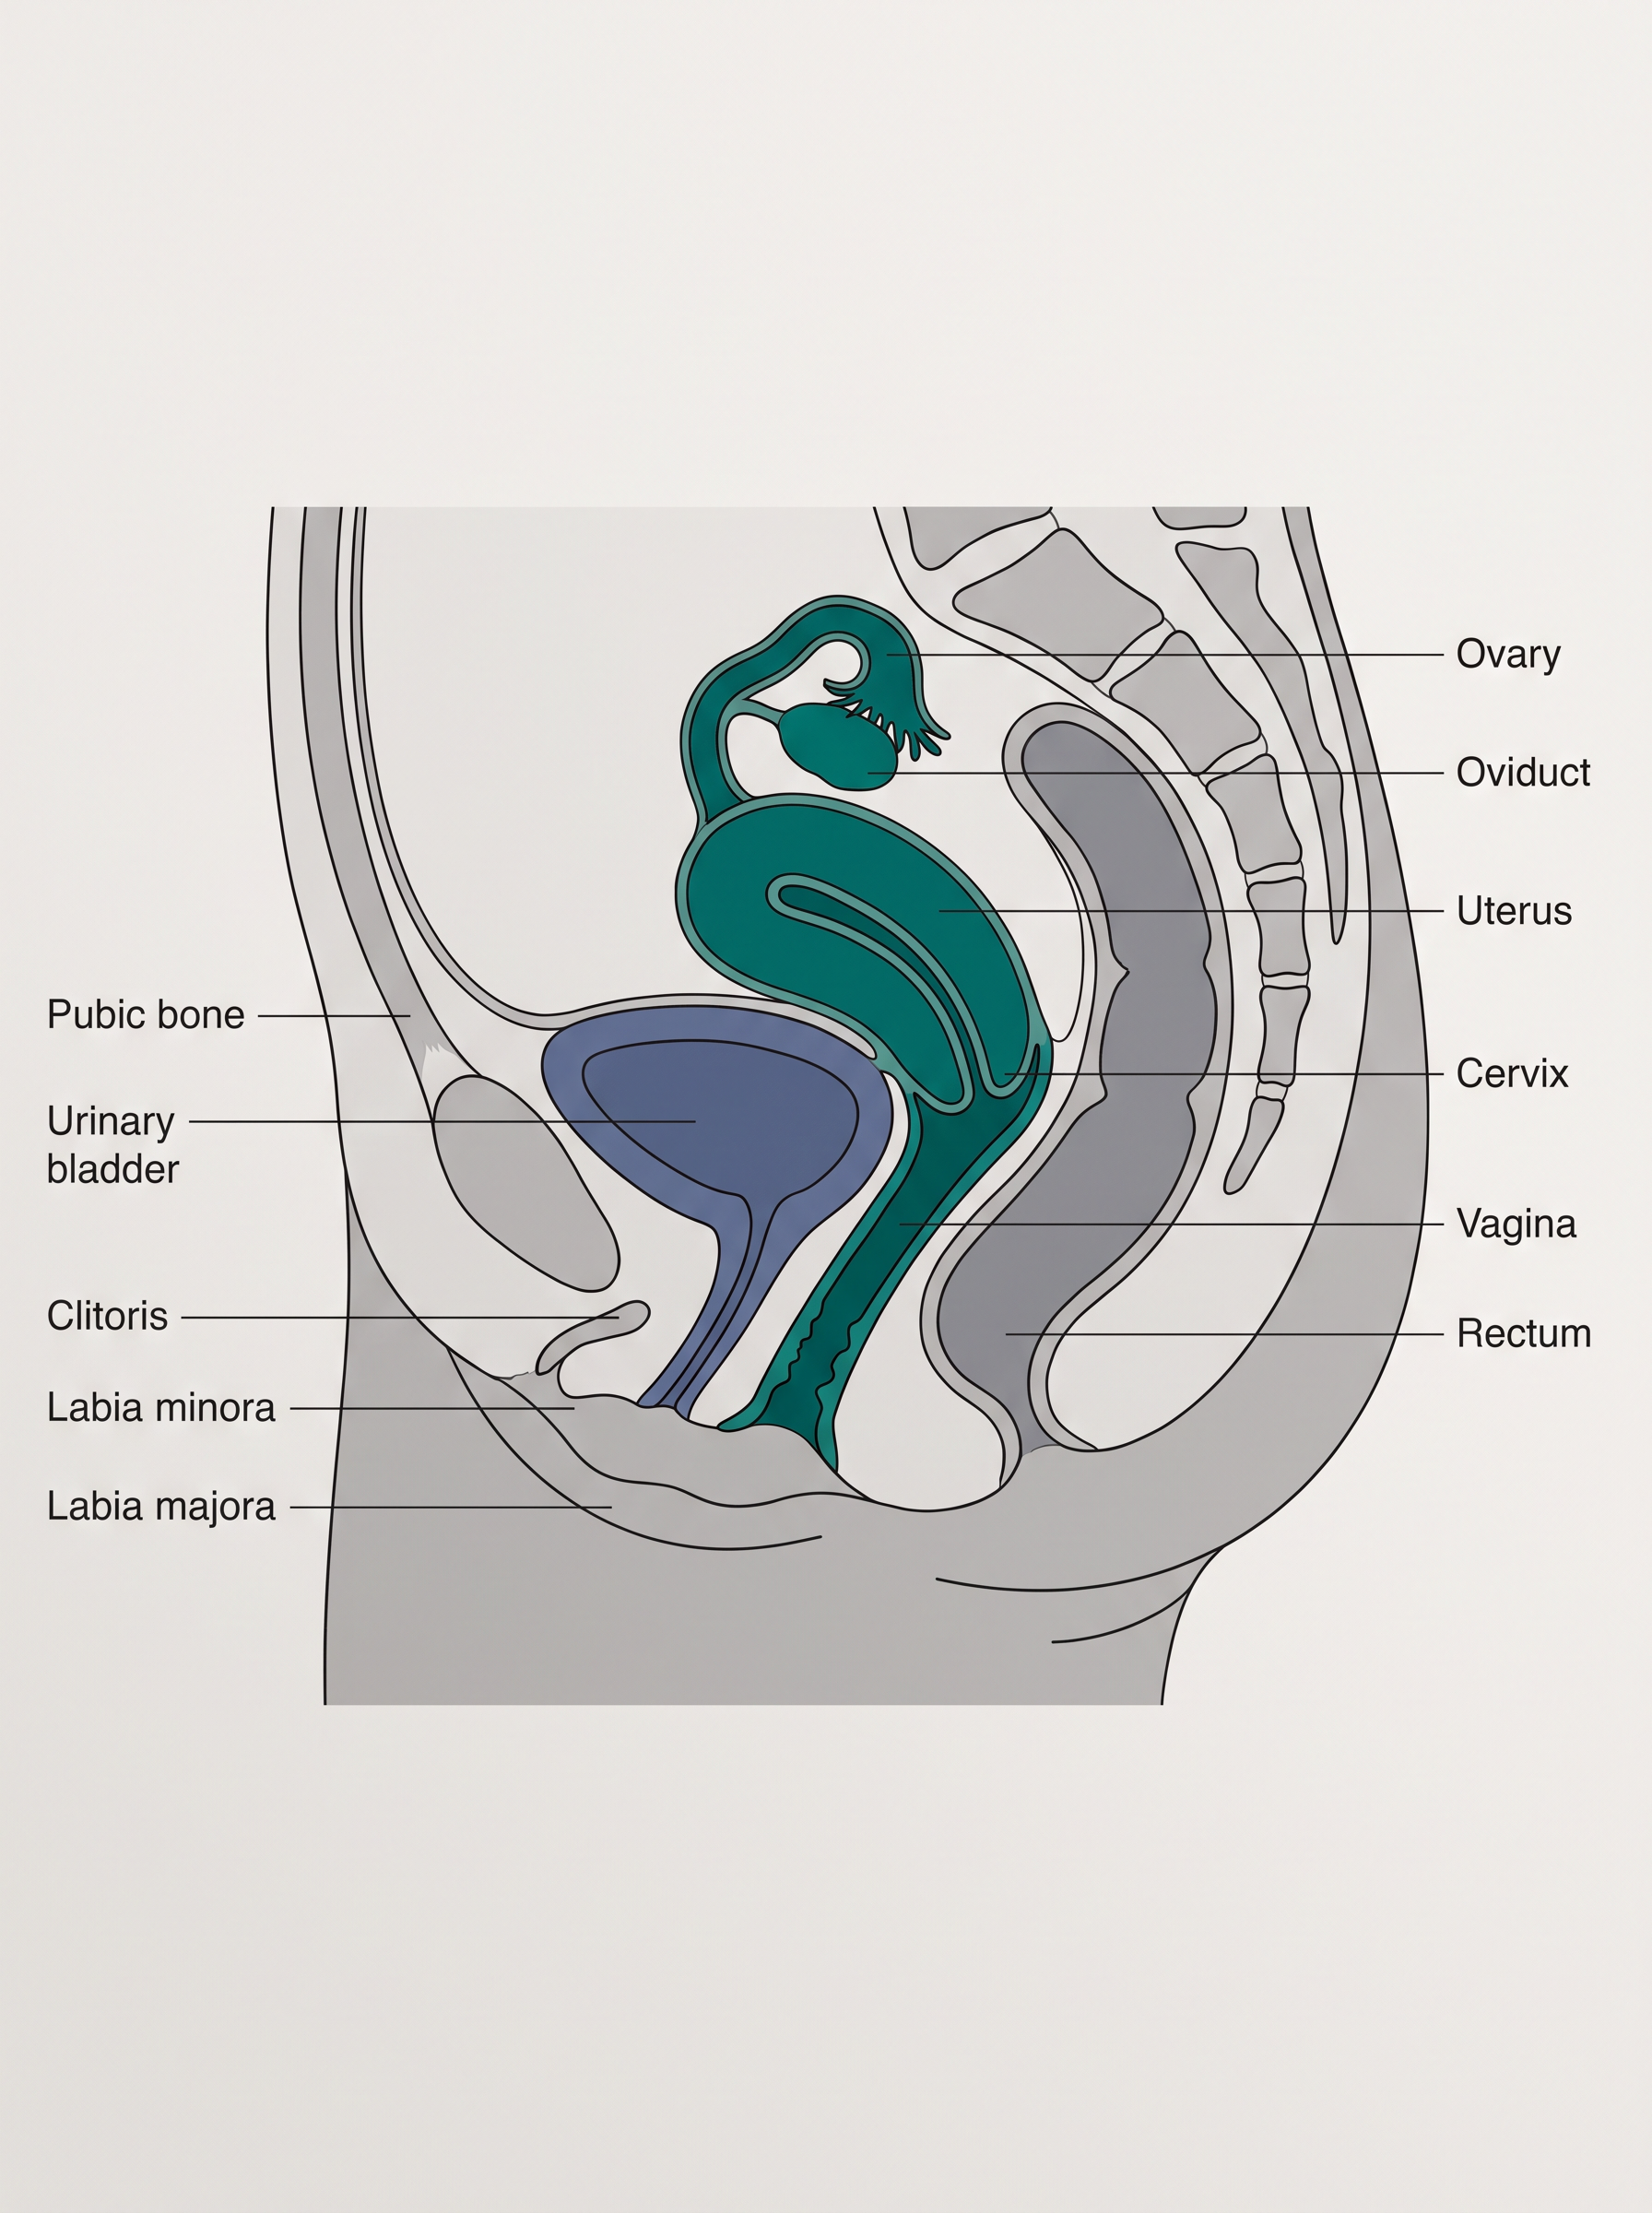
Fig. 2.4a – Female reproductive system in the pelvis.
The Ovaries
The ovaries are the primary female sex organs. They perform two jobs: they produce the female gamete — the ovum (egg) — and they secrete several steroid hormones known as the ovarian hormones. (Steroid hormones are a class of fat-derived chemical messengers.)
One ovary lies on each side of the lower abdomen (Fig. 2.5b). Each is about 2 to 4 cm long and is held in place by ligaments that anchor it to the pelvic wall and to the uterus.
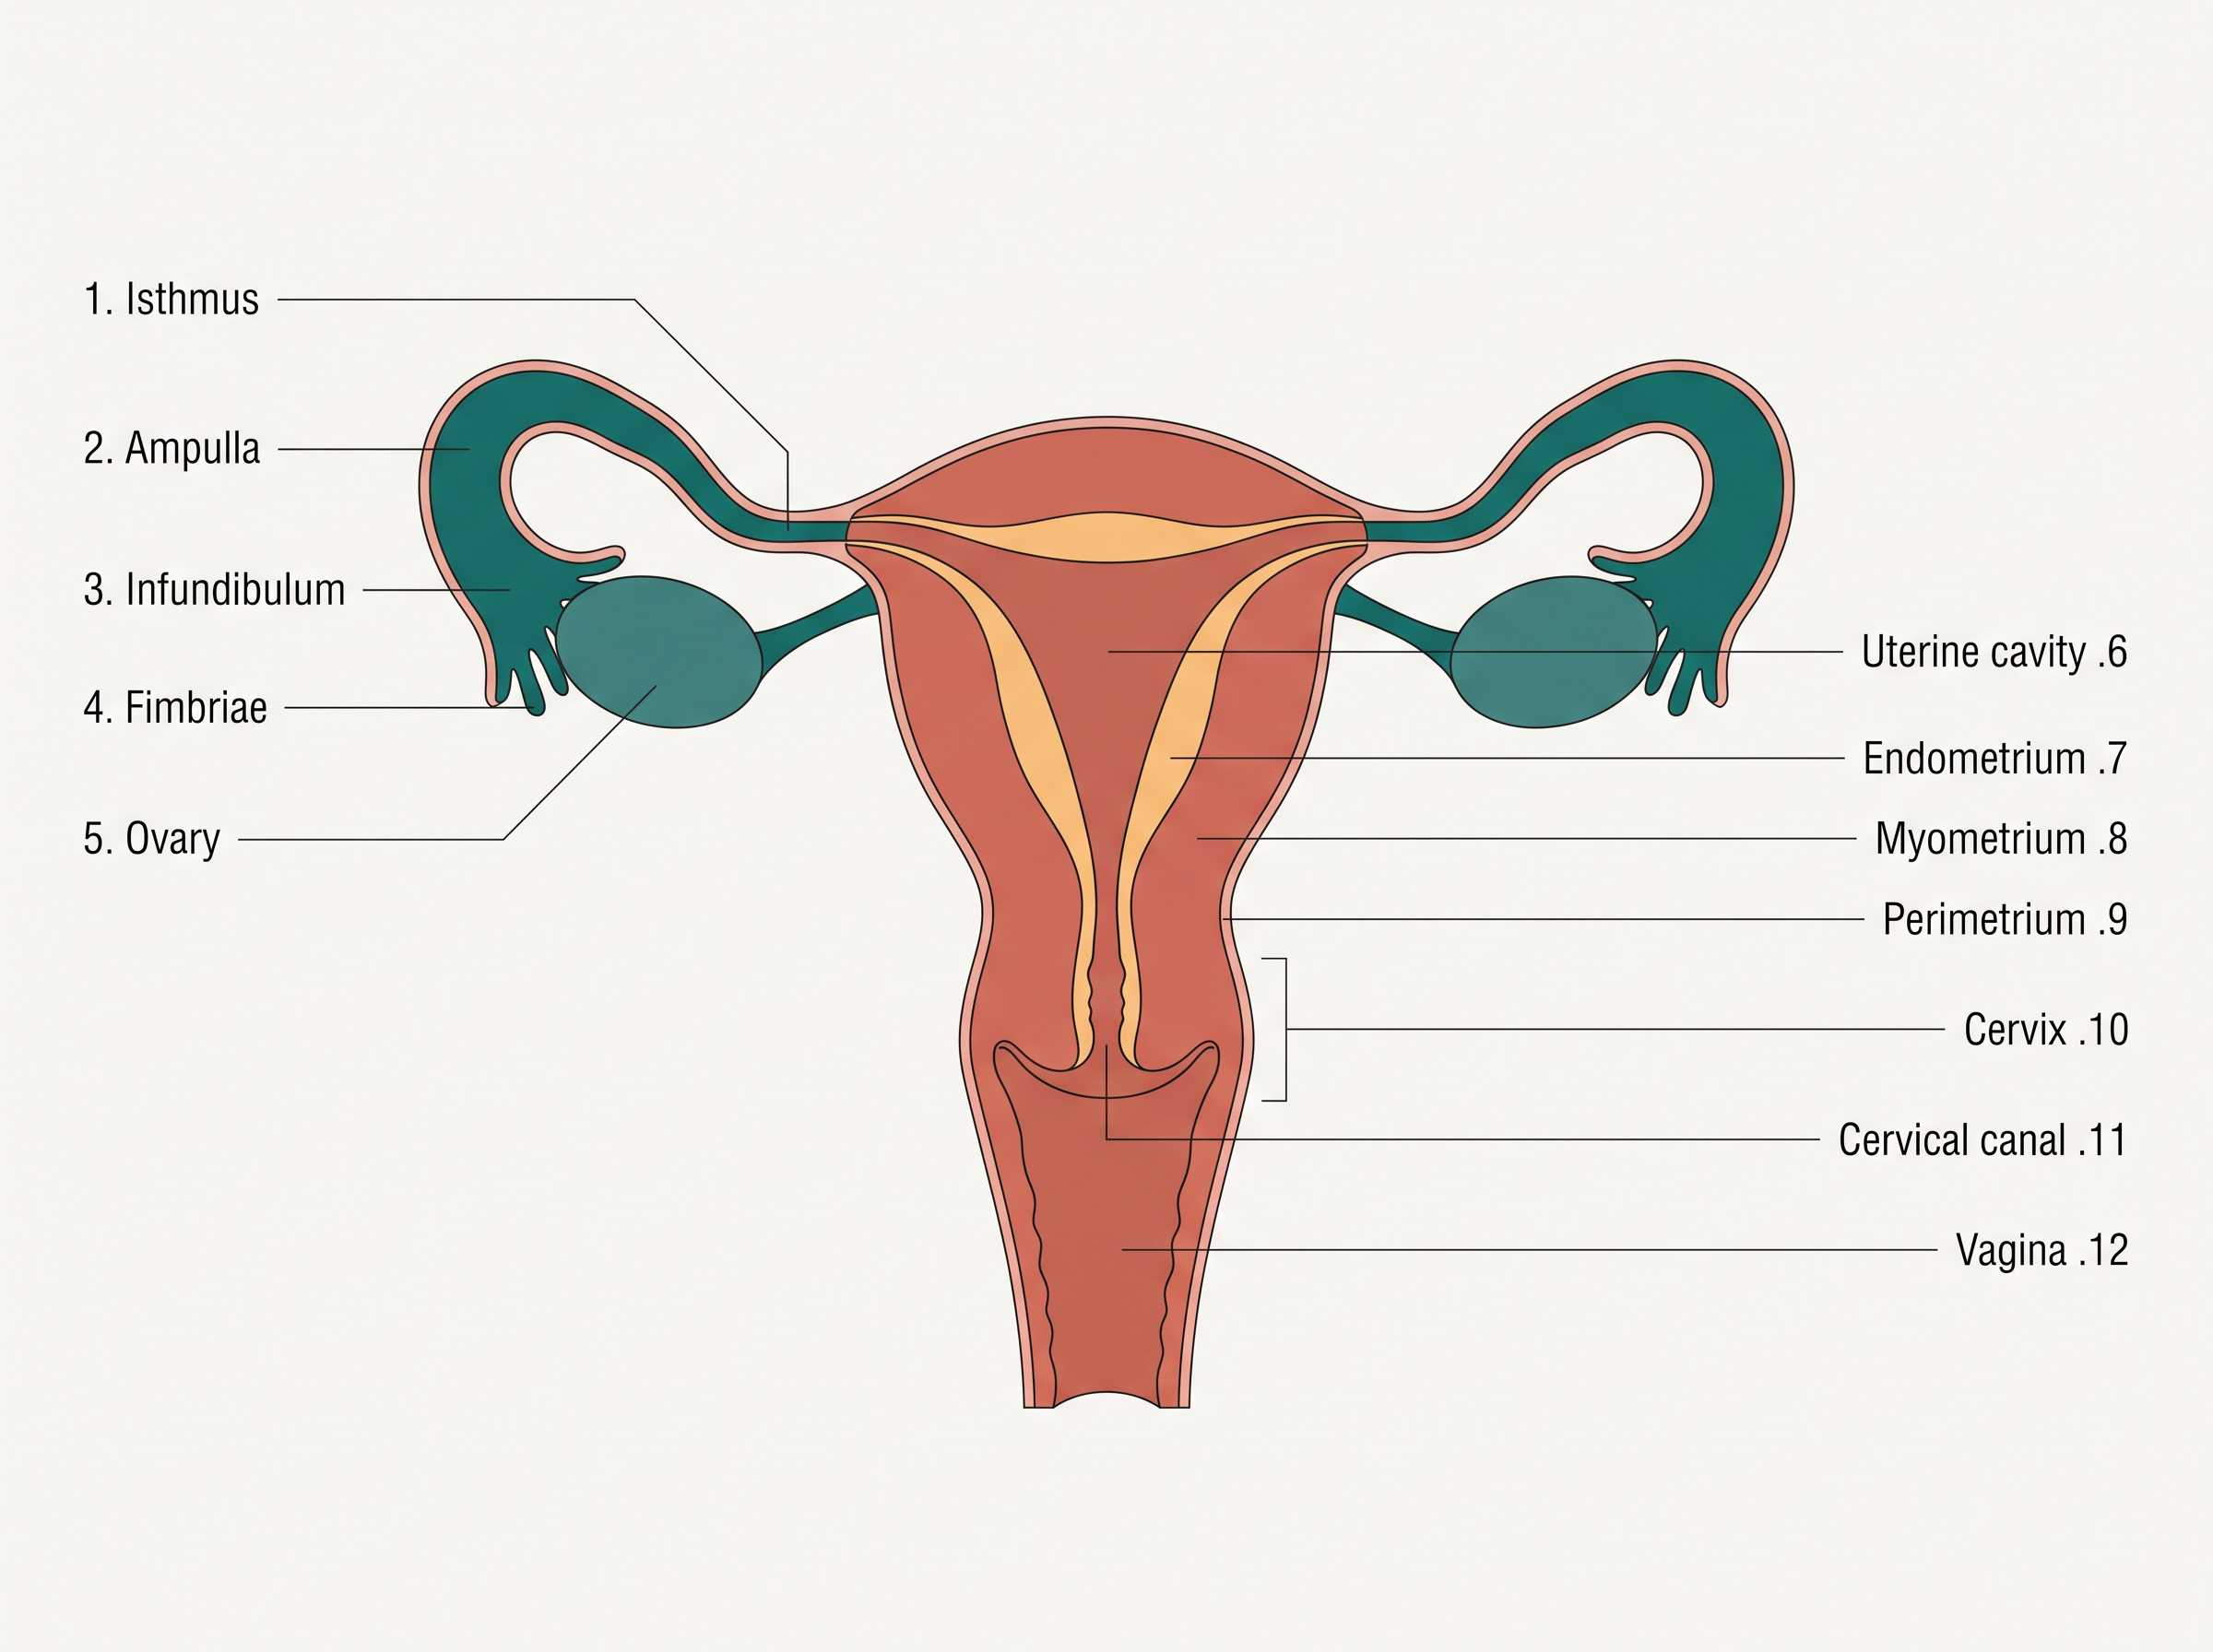
Fig. 2.5b – Anterior sectional view of the female reproductive system.
Each ovary is covered by a thin epithelium (a surface lining tissue) that encloses the inner mass called the ovarian stroma. The stroma is divided into two zones — an outer cortex and an inner medulla.
The Fallopian Tubes
The oviducts (also called fallopian tubes), the uterus and the vagina together form the female accessory ducts. Each fallopian tube is about 10–12 cm long and runs from near the ovary to the uterus (Fig. 2.5b).
The end closest to the ovary is a funnel-shaped part called the infundibulum. Its edges bear finger-like projections called fimbriae, which sweep up and collect the ovum soon after it is released at ovulation.
The infundibulum opens into a wider region called the ampulla. The final part of the oviduct, the isthmus, has a narrow channel (lumen) and joins the uterus.
The Uterus
The uterus, also called the womb, is a single organ shaped like an inverted pear and held by ligaments attached to the pelvic wall. It opens into the vagina through a narrow neck called the cervix. The cavity within the cervix is the cervical canal (Fig. 2.5b), which together with the vagina forms the birth canal through which the baby is later delivered.
The wall of the uterus is built of three tissue layers. Two of them do very different jobs during a woman’s reproductive life, so they are a frequent point of confusion in exams; the three layers are set out in the table below.
The External Genitalia
The female external genitalia include the mons pubis, labia majora, labia minora, hymen and clitoris (Fig. 2.4a).
The mons pubis is a cushion of fatty tissue covered by skin and pubic hair. Extending downward from it, the labia majora are fleshy folds that surround the vaginal opening, and beneath them lie the paired folds called the labia minora. The opening of the vagina is often partly covered by a membrane called the hymen. The clitoris is a tiny, finger-like structure at the upper meeting point of the two labia minora, just above the urethral opening.
The Mammary Glands
A working mammary gland is a feature of all female mammals. The mammary glands are the paired breasts, containing glandular tissue and a variable amount of fat.
The glandular tissue of each breast is divided into 15–20 mammary lobes, and each lobe holds clusters of milk-secreting cells called alveoli (Fig. 2.6). The alveoli make milk and store it in their cavities (lumens).
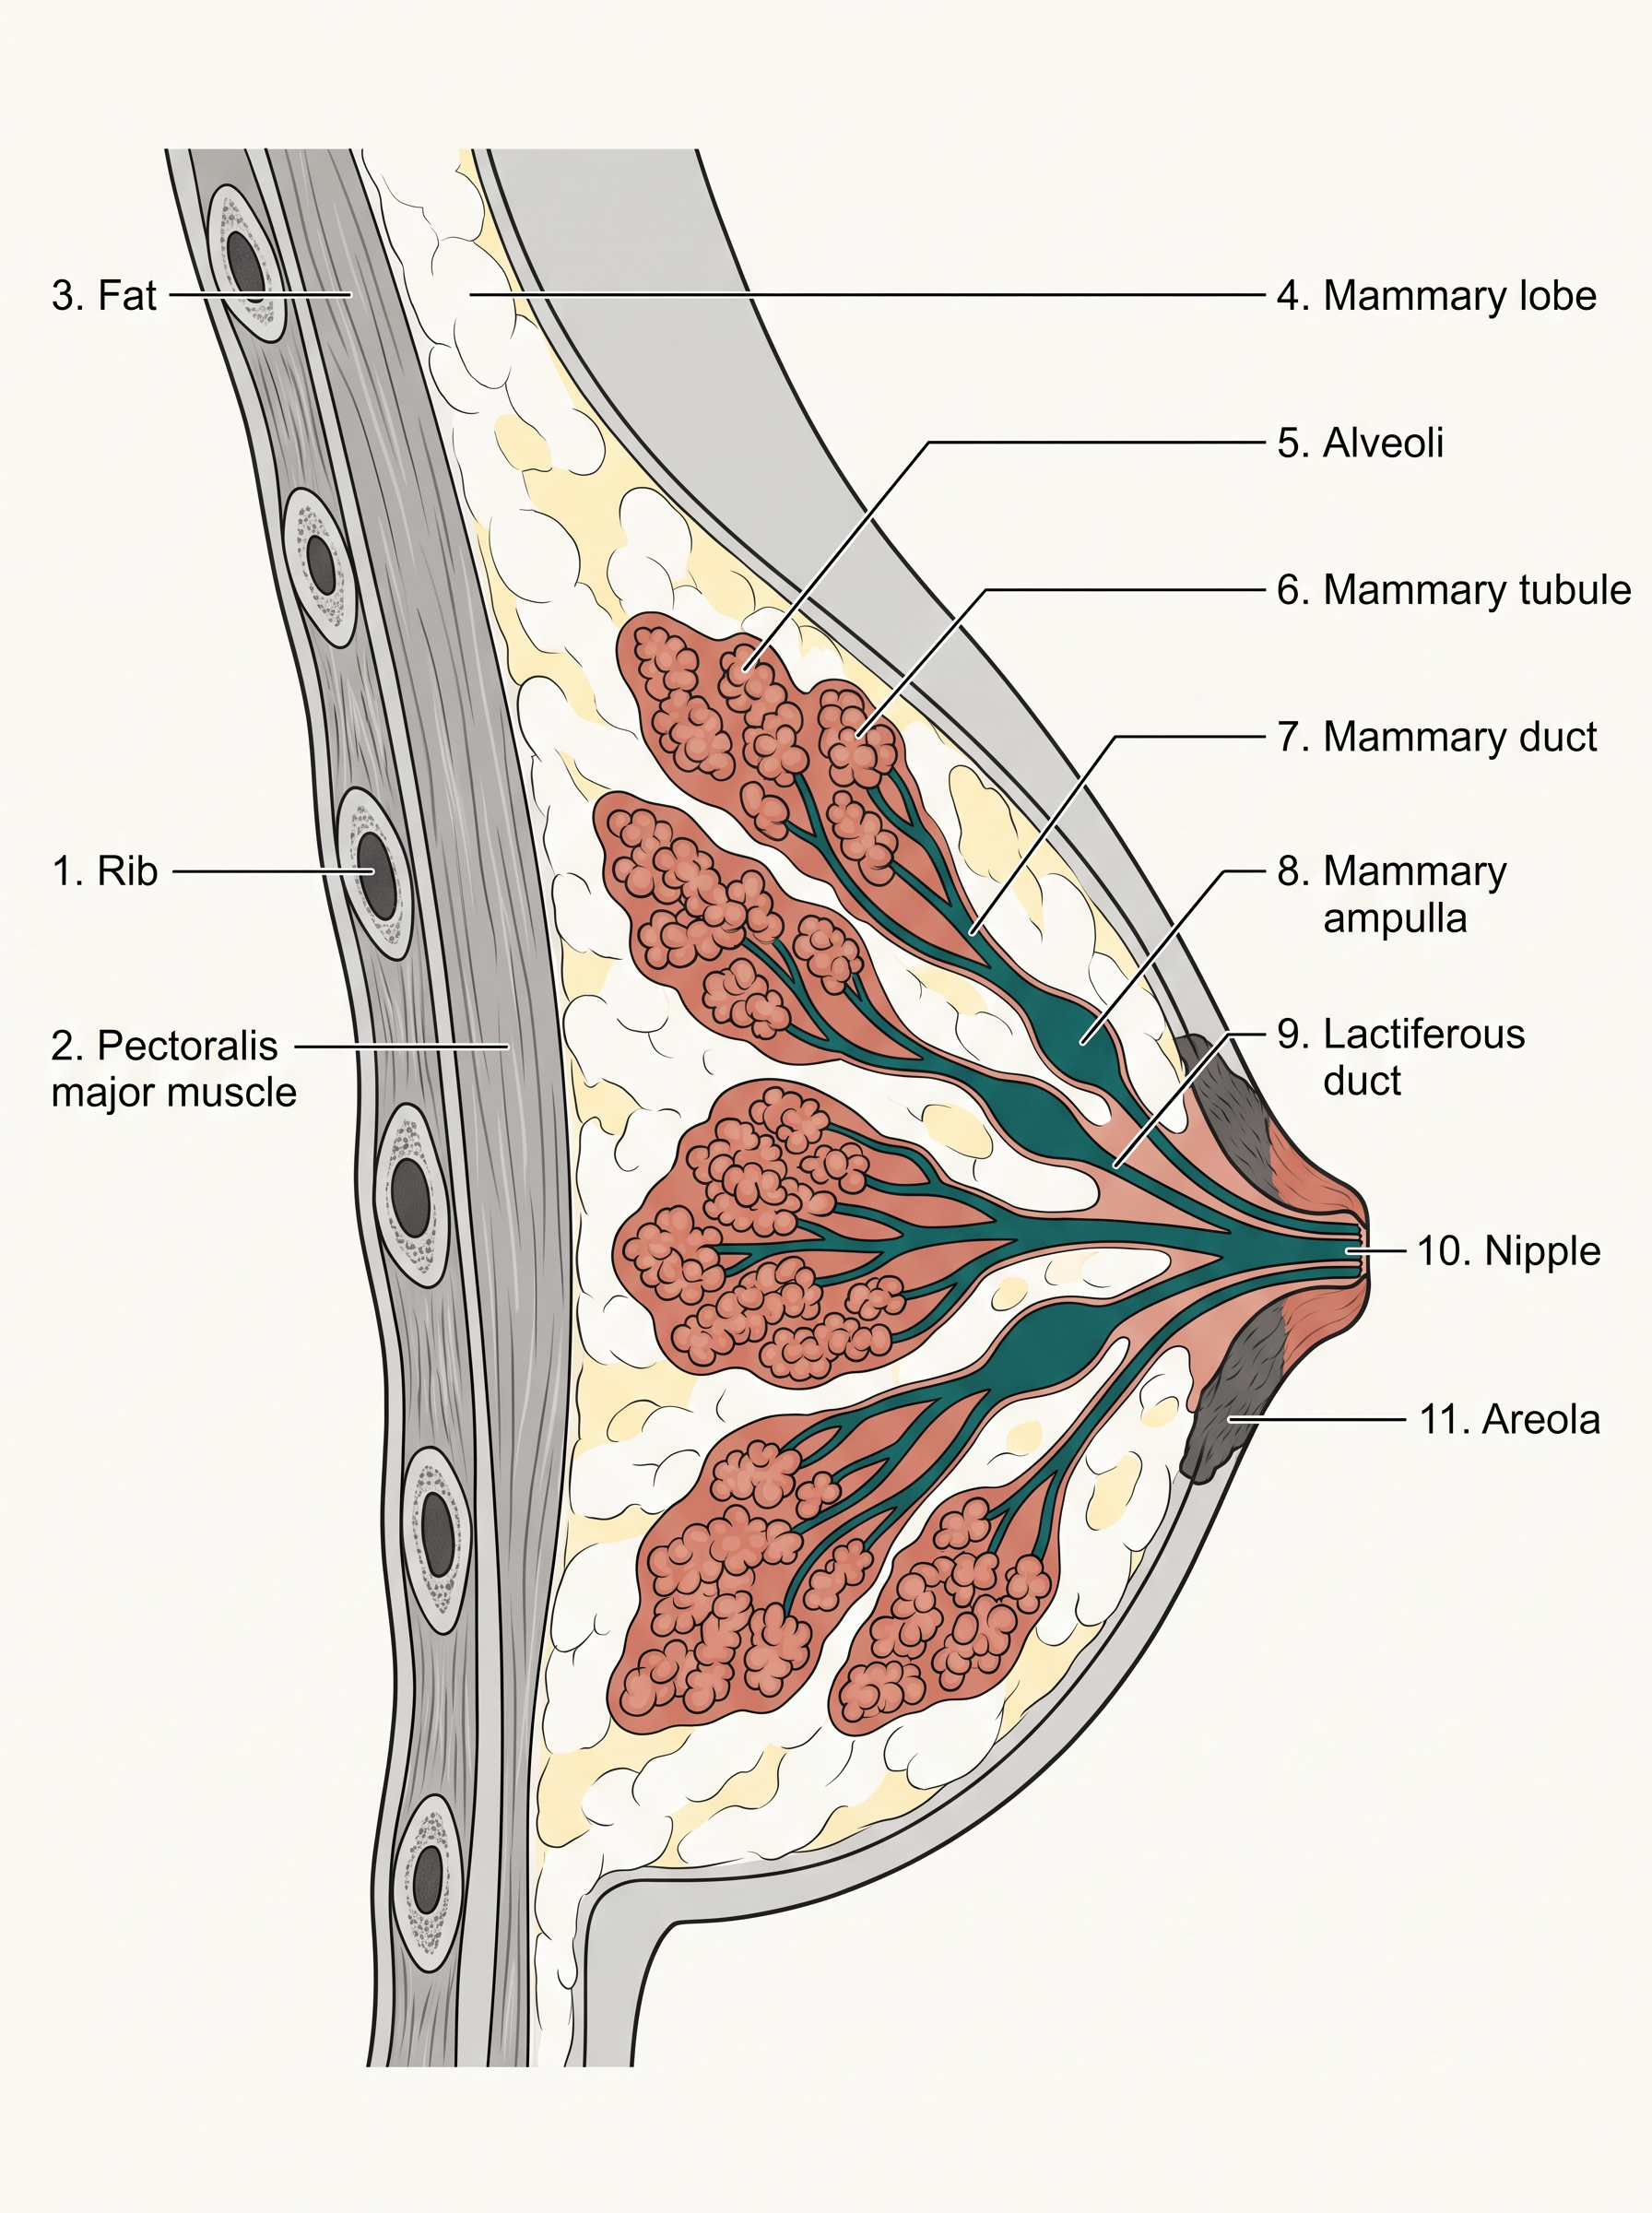
Fig. 2.6 – Sectional view of a mammary gland.
From the alveoli, milk travels along a fixed route to the outside, summarised in FC 2.3. The alveoli open into mammary tubules; the tubules of a lobe join into a mammary duct; several mammary ducts unite into a wider mammary ampulla; this connects to a lactiferous duct that opens at the nipple, from where milk is drawn during breastfeeding.
Flowchart
FC 2.3 – Path of milk through the mammary gland: alveoli → mammary tubules → mammary duct → mammary ampulla → lactiferous duct → nipple
2.3 Gametogenesis
The primary sex organs — the testis in the male and the ovaries in the female — produce the gametes: sperms and ovum, respectively. The overall process of forming these gametes is called gametogenesis. In the testis, the immature male germ cells (spermatogonia) form sperms by a process called spermatogenesis, which begins at puberty.
Spermatogenesis
The spermatogonia line the inner wall of the seminiferous tubules. They first multiply by mitotic division — the ordinary cell division that produces identical copies — so their numbers keep increasing. Each spermatogonium is diploid, meaning it carries two sets of chromosomes; in humans that is 46 chromosomes.
Some of these spermatogonia, now called primary spermatocytes, periodically undergo meiosis — the special reduction division that halves the chromosome number. A primary spermatocyte completes the first meiotic division (the reduction division) to form two equal, haploid cells called secondary spermatocytes, each carrying only 23 chromosomes. (“Haploid” means one set of chromosomes.)
The two secondary spermatocytes then complete the second meiotic division, producing four equal, haploid spermatids (Fig. 2.7).
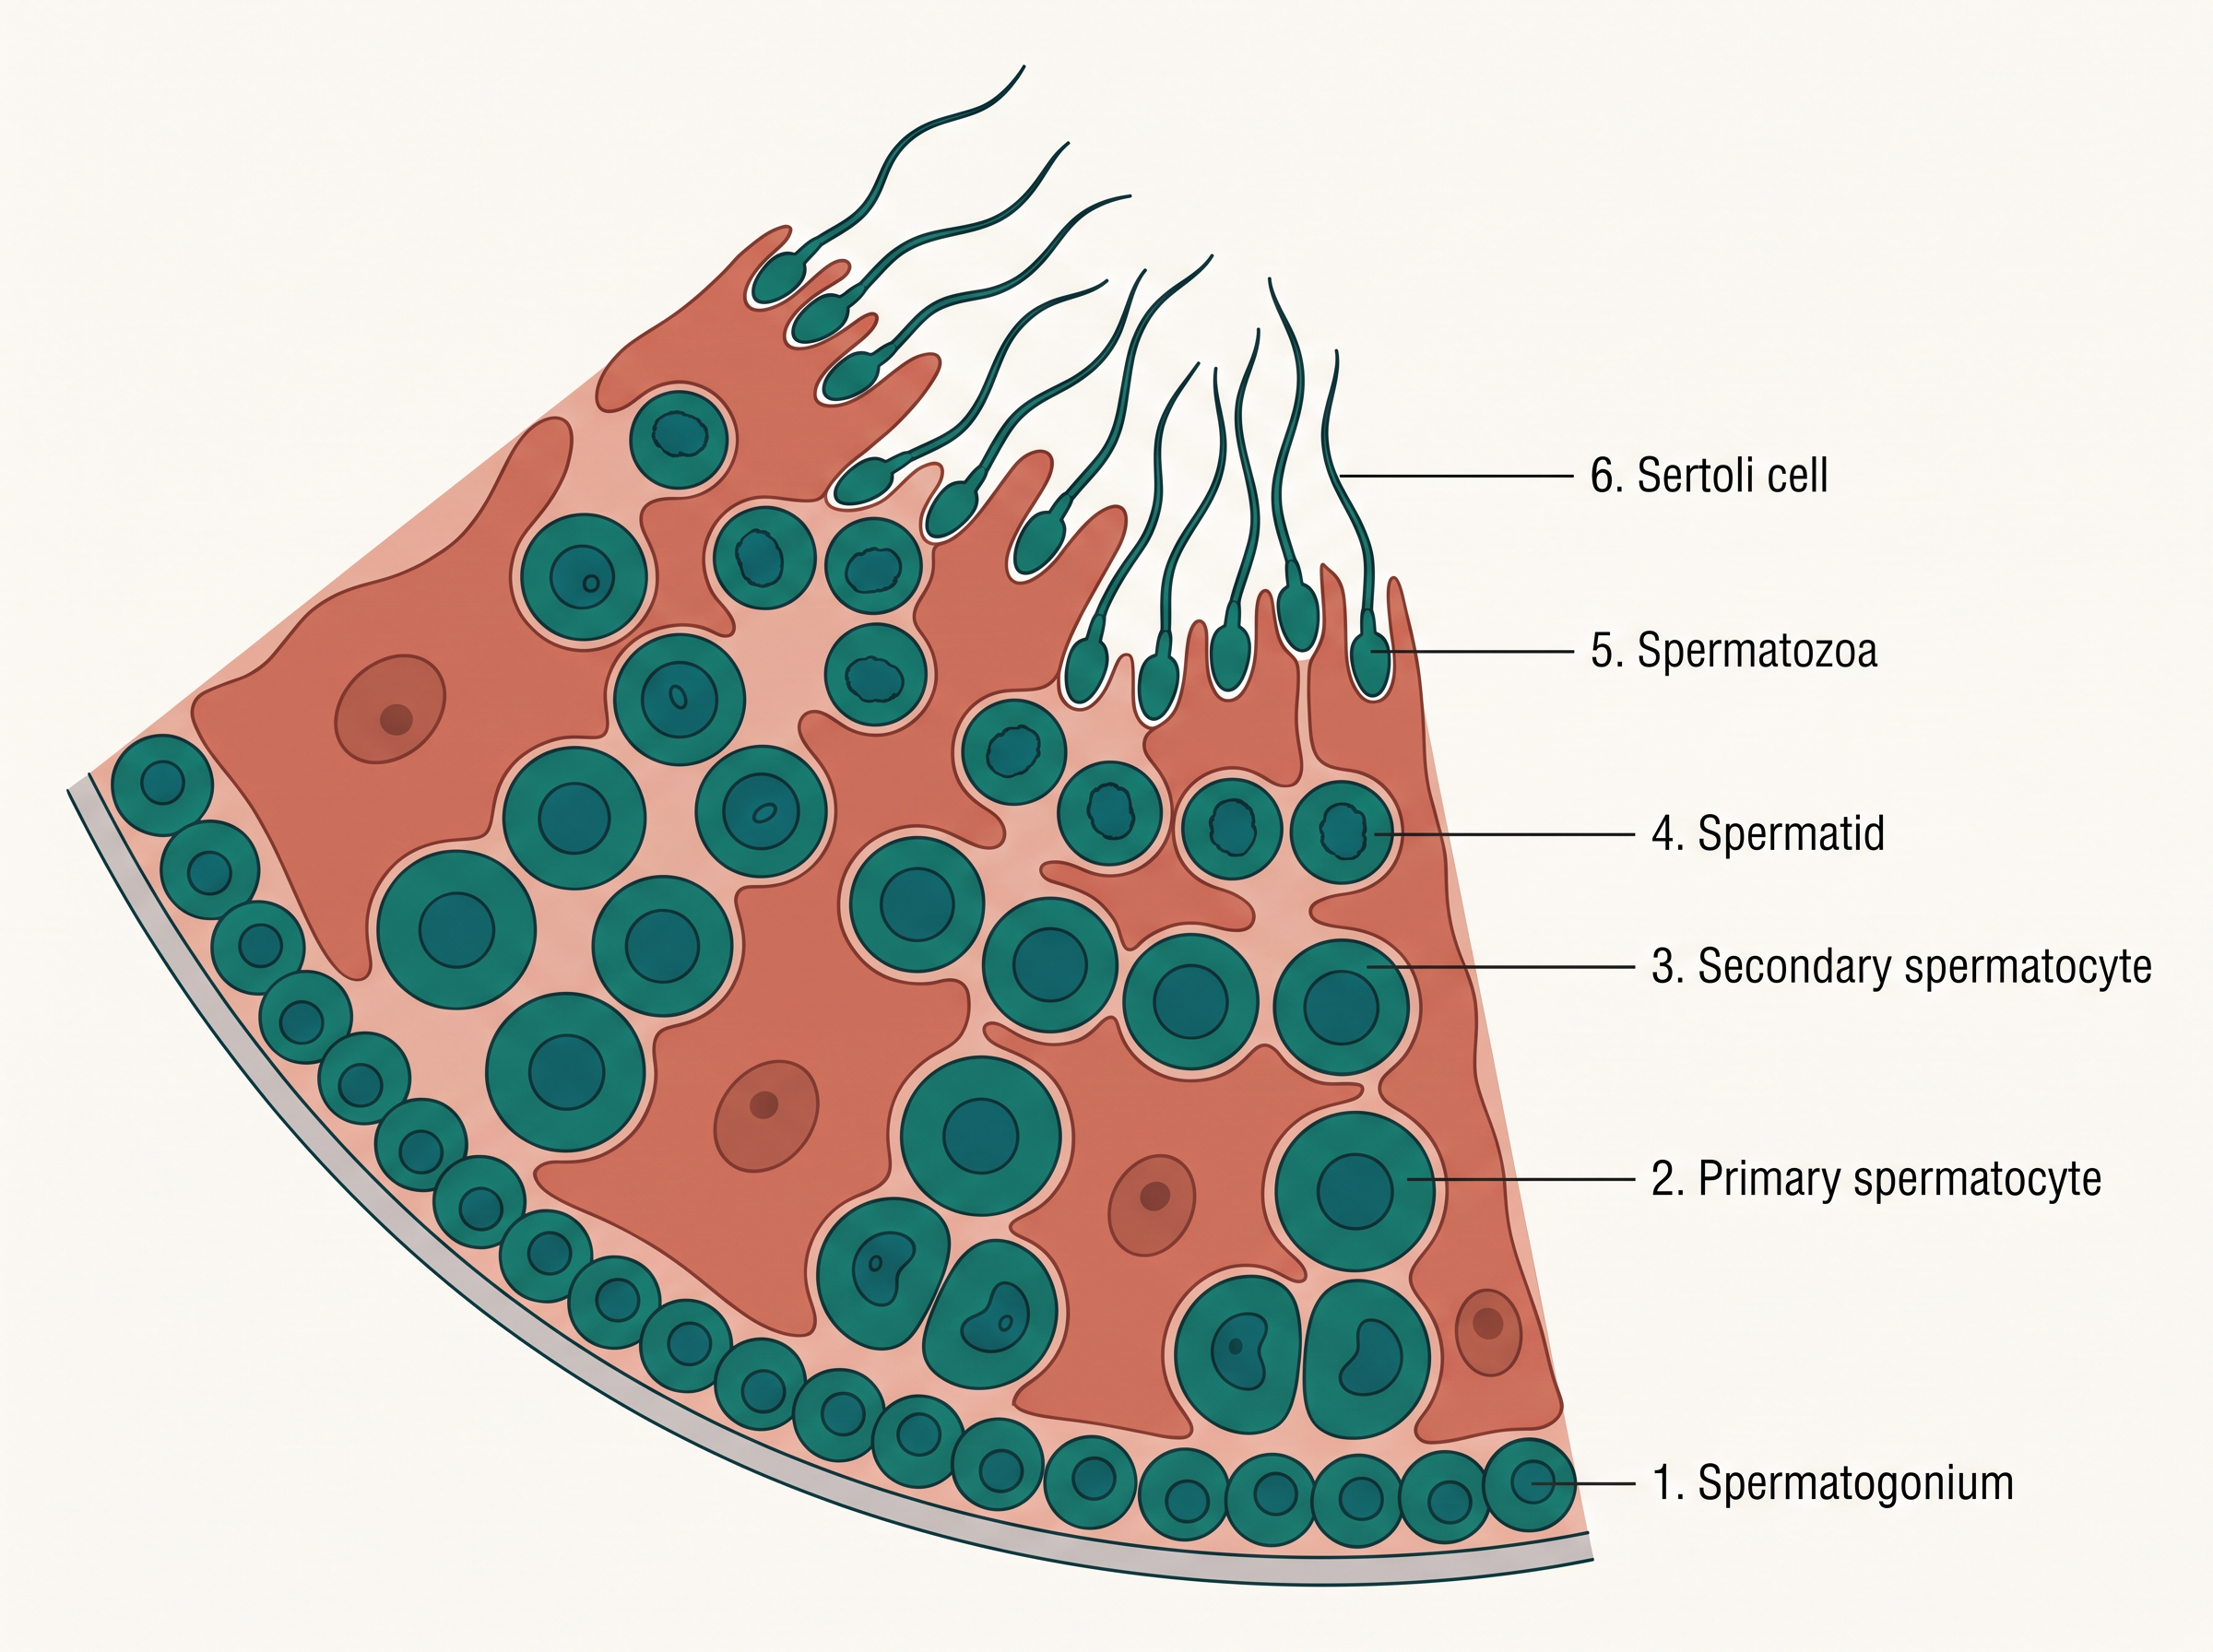
Fig. 2.7 – Enlarged view of a seminiferous tubule.
The spermatids are not yet swimming sperms. They are reshaped into spermatozoa (sperms) by a process called spermiogenesis. After spermiogenesis, the sperm heads stay tucked into the Sertoli cells for a while and are finally set free from the seminiferous tubules by a process called spermiation. The whole sequence is summarised in FC 2.4.
Flowchart
FC 2.4 – Spermatogenesis: spermatogonium (diploid, 46) → [mitosis, multiply] → primary spermatocyte (diploid, 46) → [meiosis I] → 2 secondary spermatocytes (haploid, 23) → [meiosis II] → 4 spermatids (haploid, 23) → [spermiogenesis] → spermatozoa → [spermiation] → released into tubule
Hormonal Control of Spermatogenesis
Spermatogenesis begins at puberty because of a marked rise in the secretion of gonadotropin releasing hormone (GnRH), a hormone released by the hypothalamus of the brain.
The raised GnRH acts on the anterior part of the pituitary gland and stimulates it to release two gonadotropins — luteinising hormone (LH) and follicle stimulating hormone (FSH). These two hormones then act on different targets in the testis, as shown in FC 2.5.
LH acts on the Leydig cells and drives them to make and release androgens; the androgens, in turn, stimulate spermatogenesis. FSH acts on the Sertoli cells and stimulates them to secrete certain factors that help spermiogenesis.
Flowchart
FC 2.5 – Hormonal control of spermatogenesis: hypothalamus → GnRH → anterior pituitary → releases LH and FSH; LH → Leydig cells → androgens → stimulate spermatogenesis; FSH → Sertoli cells → factors → help spermiogenesis
Structure of the Sperm
A sperm is a microscopic cell built of four parts — a head, a neck, a middle piece and a tail (Fig. 2.8). A plasma membrane wraps the entire body of the sperm.
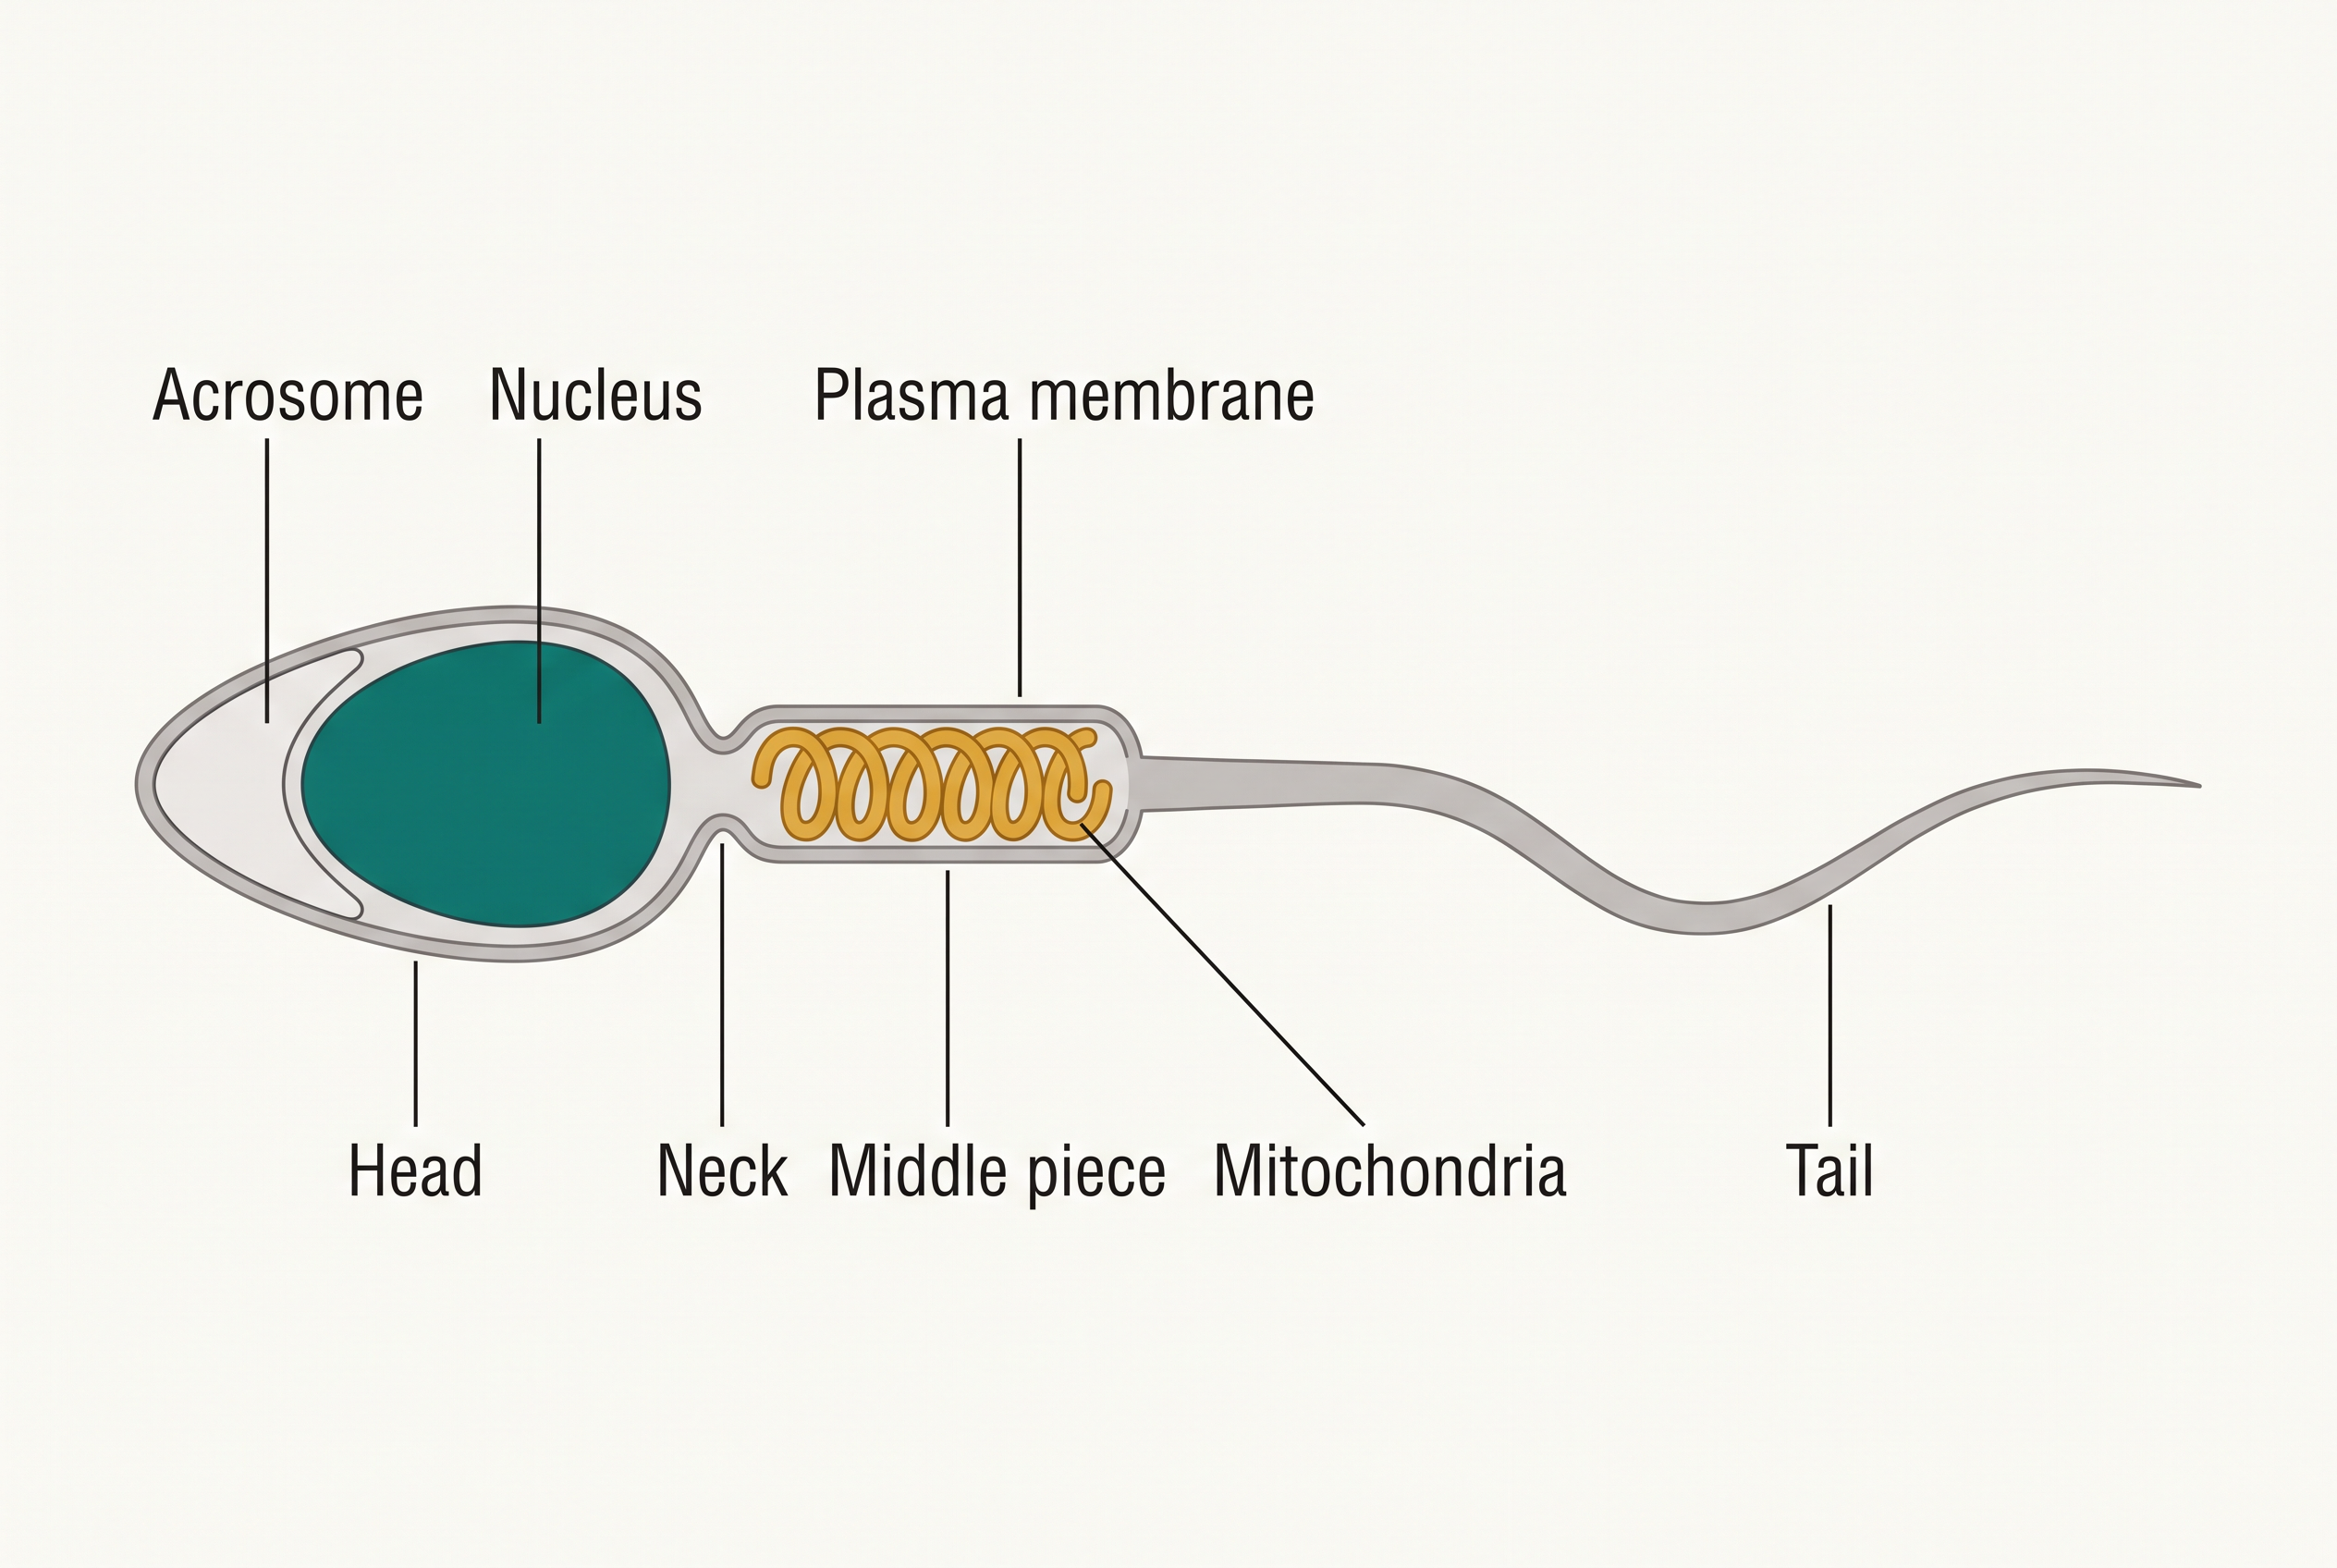
Fig. 2.8 – Structure of a human sperm.
The head holds an elongated haploid nucleus. Its front tip is covered by a cap-like structure, the acrosome, which is filled with enzymes.
The middle piece is packed with numerous mitochondria, the cell’s energy factories.
A human male ejaculates about 200 to 300 million sperms during a single coitus. For normal fertility, at least 60 per cent of these sperms must have a normal shape and size, and at least 40 per cent must show vigorous motility.
Once released from the seminiferous tubules, the sperms are carried along by the accessory ducts. The secretions of the epididymis, vas deferens, seminal vesicle and prostate are all needed for the maturation and motility of the sperms. The seminal plasma together with the sperms makes up the semen.
The functions of the male accessory ducts and glands are themselves maintained by the testicular hormones, the androgens.
Oogenesis
The formation of the mature female gamete is called oogenesis, and it is strikingly different from spermatogenesis. Oogenesis begins very early — during embryonic development, while the female is still in her mother’s womb. At that stage, a few million gamete mother cells called oogonia are formed inside each fetal ovary. No new oogonia are ever formed or added after birth.
These oogonia begin division and enter prophase-I of meiosis, but then pause — they become temporarily arrested at that stage and are now called primary oocytes. Each primary oocyte becomes surrounded by a layer of granulosa cells, forming a primary follicle (Fig. 2.9).
Between birth and puberty, a large number of these follicles simply degenerate. As a result, only about 60,000–80,000 primary follicles are left in each ovary at puberty. The surviving primary follicles gather more layers of granulosa cells and a new covering called the theca, and are then known as secondary follicles.
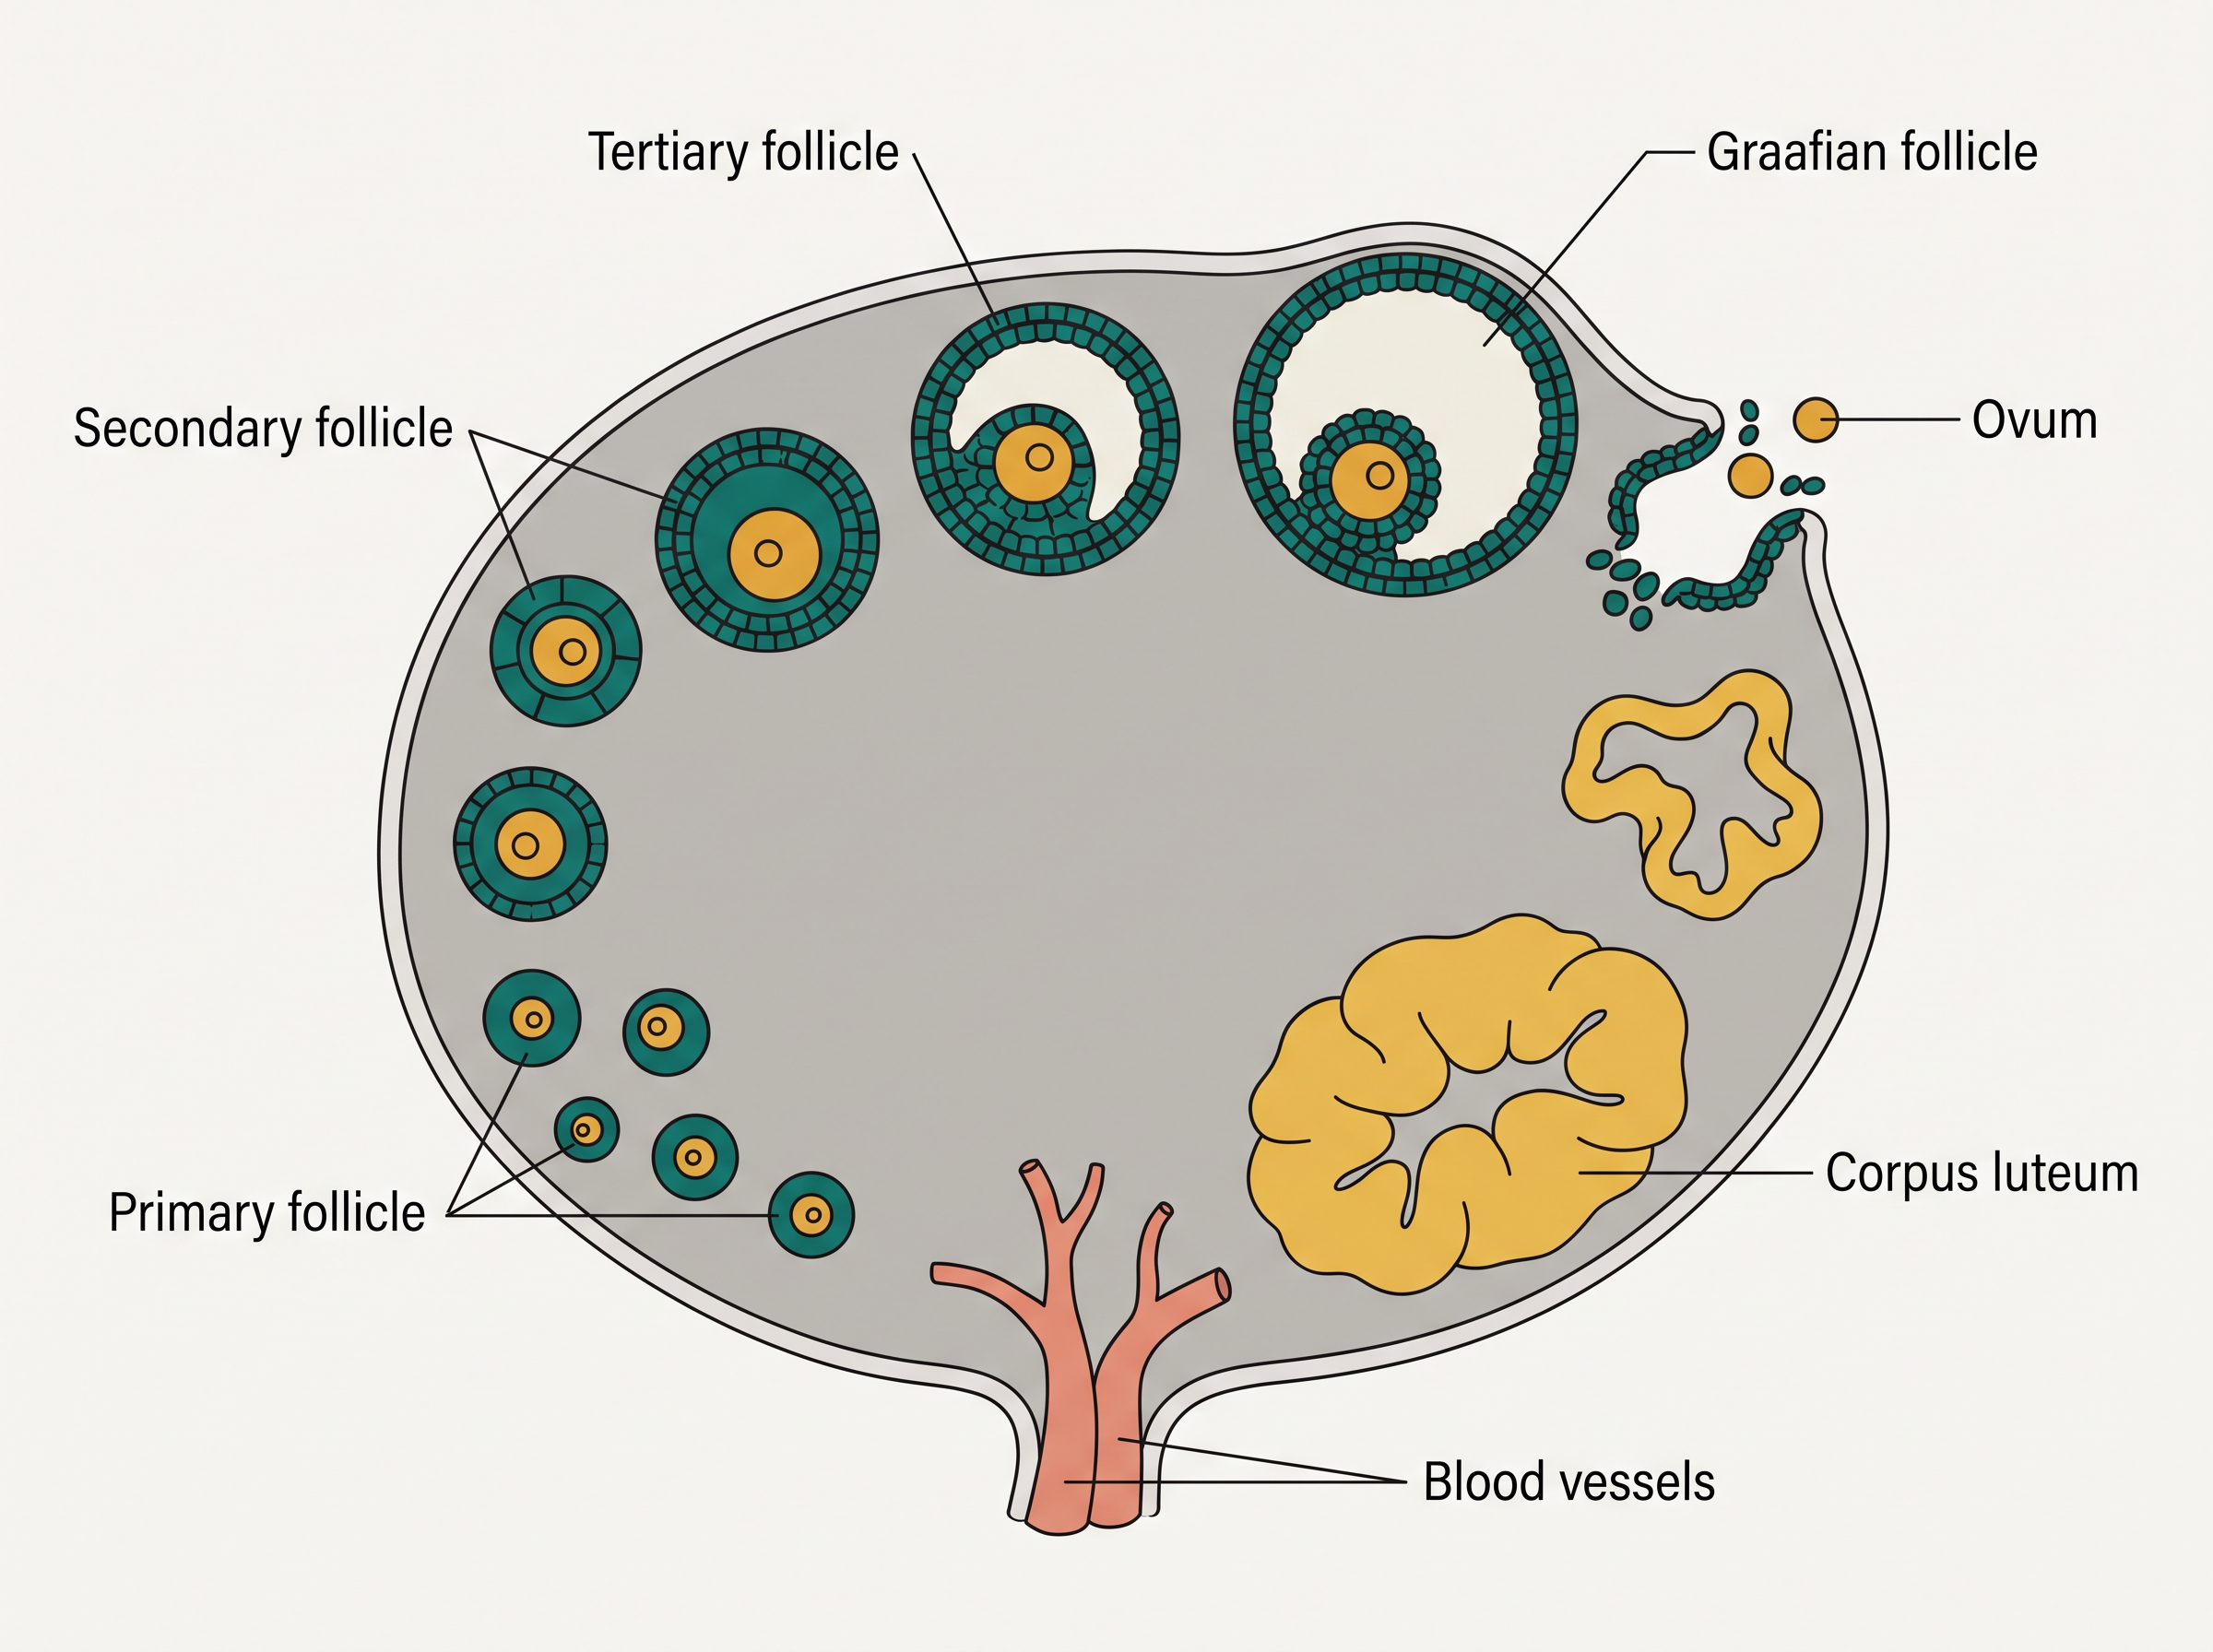
Fig. 2.9 – Sectional view of an ovary.
The secondary follicle soon becomes a tertiary follicle, marked by a fluid-filled cavity called the antrum. Its theca now organises into an inner theca interna and an outer theca externa. It is at this stage that the primary oocyte inside the tertiary follicle grows in size and finally completes its first meiotic division.
This division is unequal: it produces one large, haploid secondary oocyte and one tiny first polar body (Fig. 2.10b). The secondary oocyte keeps almost all of the nutrient-rich cytoplasm of the primary oocyte.
Whether the first polar body then divides again or simply degenerates is not certain at present. The tertiary follicle next matures into the Graafian follicle (the mature follicle, Fig. 2.9). The secondary oocyte develops a new membrane around itself called the zona pellucida. The Graafian follicle then ruptures and releases the secondary oocyte (the ovum) from the ovary — a process called ovulation. The full sequence is shown in FC 2.6.
Flowchart
FC 2.6 – Oogenesis and follicle development: oogonia (formed before birth) → primary oocytes (arrested at prophase-I) → primary follicle → secondary follicle → tertiary follicle (antrum forms; primary oocyte completes meiosis I → secondary oocyte + first polar body) → Graafian (mature) follicle → ovulation (secondary oocyte released)
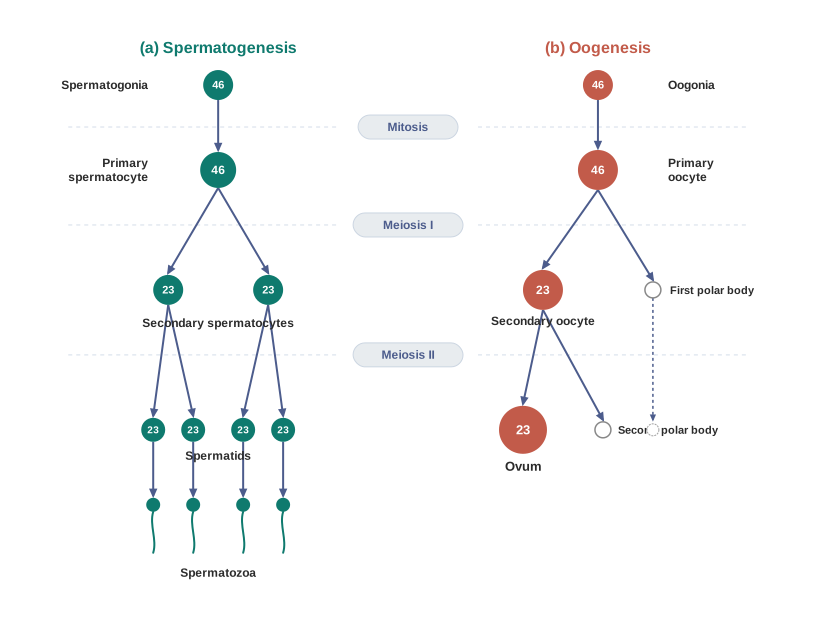
Fig. 2.10 – (a) Spermatogenesis and (b) oogenesis.
Comparing the two processes side by side makes their differences clear — a comparison that examiners frequently ask about.
2.4 Menstrual Cycle
The reproductive cycle of female primates — monkeys, apes and human beings — is called the menstrual cycle. The very first menstruation, which begins at puberty, is called menarche.
In human females, menstruation is repeated on average about every 28/29 days, and the whole set of events from one menstruation until the next makes up one menstrual cycle. During the middle of each cycle, one ovum is released — that is, ovulation occurs.
The major events of the cycle are shown in Fig. 2.11. Overall, the cycle passes through four phases in a fixed order, summarised in FC 2.7.
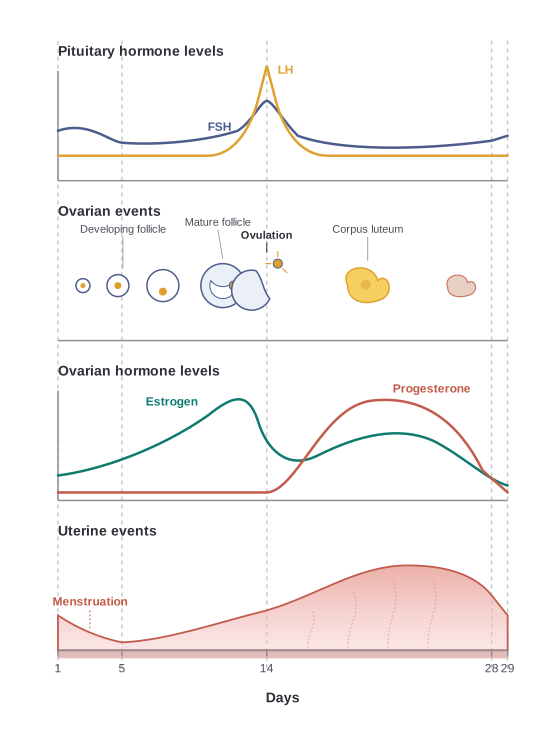
Fig. 2.11 – Events of the menstrual cycle.
Flowchart
FC 2.7 – Phases of the menstrual cycle: menstrual phase (3–5 days) → follicular phase (follicle matures, endometrium regenerates) → ovulatory phase (LH surge → ovulation, ~14th day) → luteal phase (corpus luteum, progesterone) → if no fertilisation, back to menstrual phase (new cycle)
The Menstrual Phase
The cycle opens with the menstrual phase, when menstrual flow occurs; it lasts about 3–5 days. The flow is produced by the breakdown of the endometrial lining of the uterus and its blood vessels, which forms the liquid that passes out through the vagina.
Importantly, menstruation happens only if the released ovum is not fertilised. A missed menstruation can therefore be a sign of pregnancy — though it may also be caused by other factors such as stress or poor health.
The Follicular Phase
The menstrual phase is followed by the follicular phase. During this phase, primary follicles in the ovary grow until one becomes a fully mature Graafian follicle, and at the same time the endometrium of the uterus rebuilds itself through proliferation (regrowth of its cells).
These parallel changes in the ovary and the uterus are driven by shifting levels of pituitary and ovarian hormones (Fig. 2.11). The secretion of the gonadotropins LH and FSH rises gradually through the follicular phase, stimulating both follicle growth and the secretion of estrogens by the growing follicles. Both LH and FSH reach a peak in the middle of the cycle, at about the 14th day.
Ovulation and the LH Surge
The rapid rise of LH to its maximum level at mid-cycle is called the LH surge. This surge triggers the rupture of the Graafian follicle and the release of the ovum — this is ovulation, and it defines the ovulatory phase.
The Luteal Phase
After ovulation comes the luteal phase. The parts of the Graafian follicle that are left behind in the ovary transform into a yellowish structure called the corpus luteum (Fig. 2.11).
The corpus luteum secretes large amounts of progesterone, the hormone essential for maintaining the endometrium. A well-maintained endometrium is exactly what is needed for the implantation of a fertilised ovum and for the later events of pregnancy. During pregnancy, all the events of the menstrual cycle stop, and there is no menstruation.
If fertilisation does not occur, the corpus luteum degenerates. This withdrawal of progesterone causes the endometrium to disintegrate, which brings on menstruation and marks the start of a fresh cycle.
Menopause
In human beings, menstrual cycles come to an end at around 50 years of age; this stopping is called menopause. Regular, cyclic menstruation is a sign of a normal reproductive phase, and it extends across a woman’s life between menarche and menopause.
2.5 Fertilisation and Implantation
During copulation (coitus), semen is released by the penis into the vagina — the event called insemination. From here, the sperms must travel a long way to meet the ovum.
The Sperm’s Journey and the Meeting Point
The motile sperms swim rapidly, pass through the cervix, enter the uterus, and finally reach the ampullary region of the fallopian tube (Fig. 2.12b). The ovum released from the ovary is also carried to this same ampullary region, and it is here that fertilisation takes place.
There is a crucial condition: fertilisation can happen only if the ovum and the sperms arrive at the ampulla at the same time. This timing requirement is exactly why not every copulation leads to fertilisation and pregnancy.
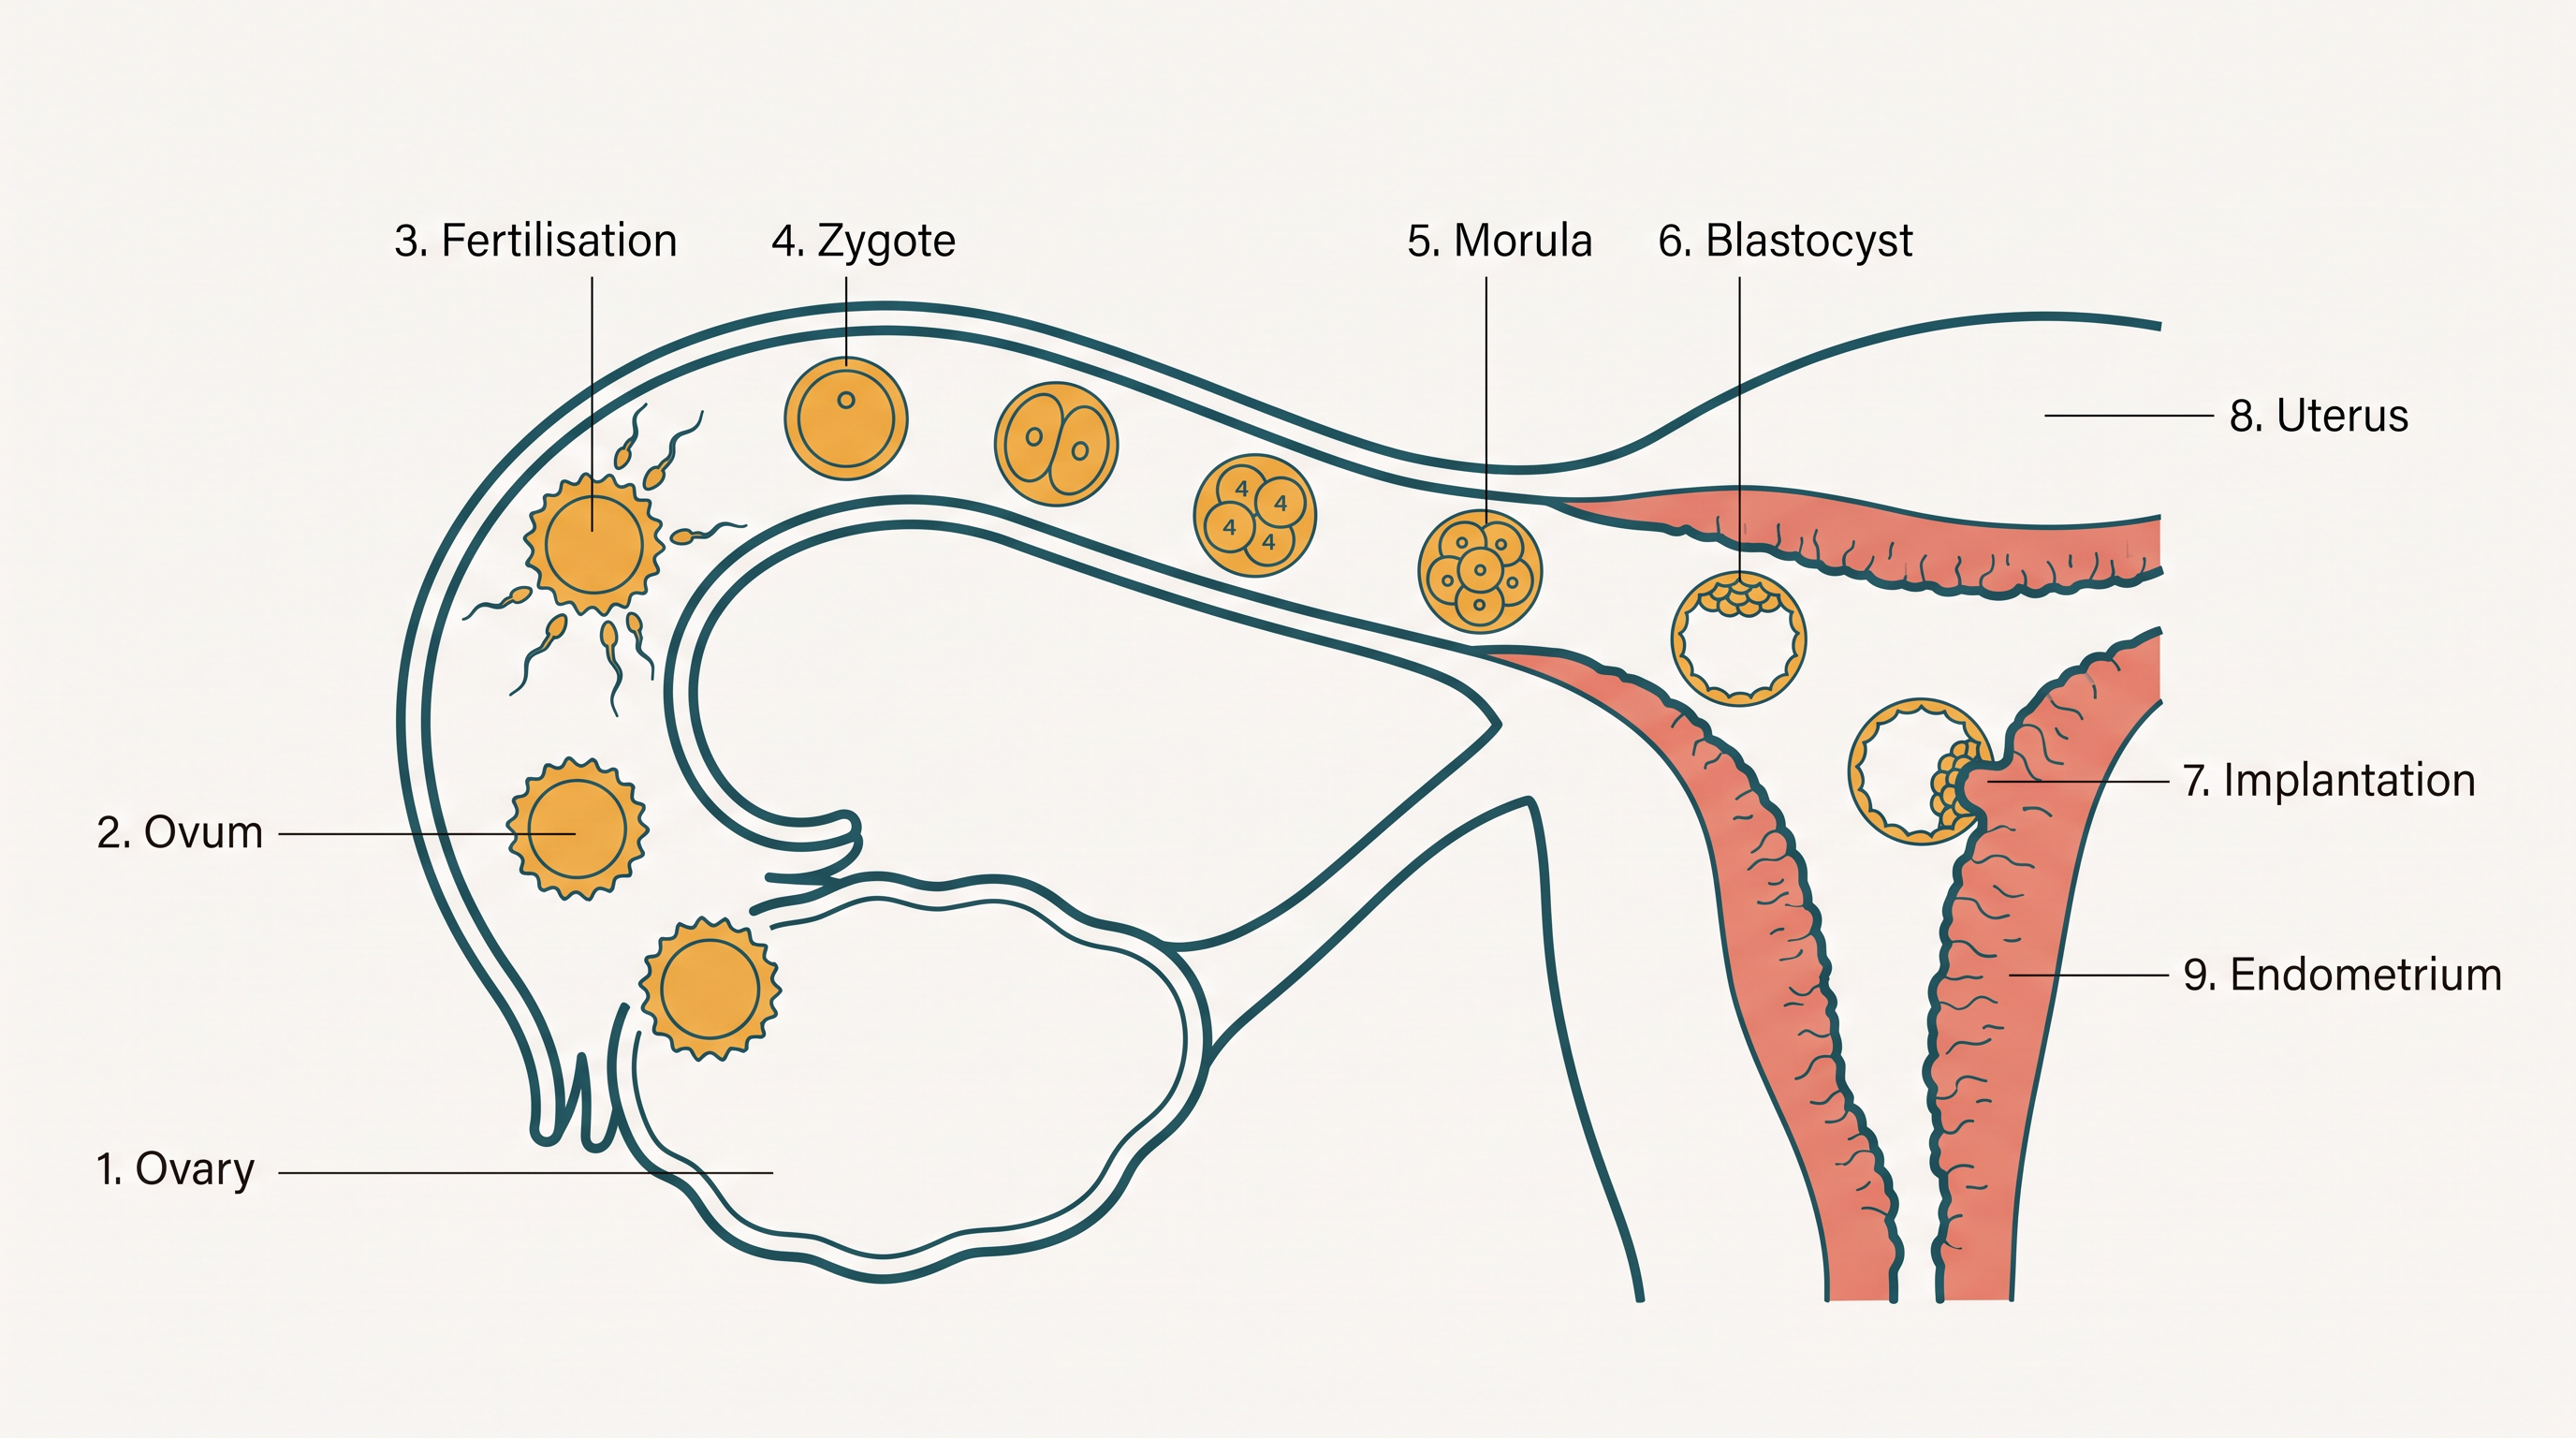
Fig. 2.12 – Transport of the ovum, fertilisation and implantation.
The Moment of Fertilisation
The fusion of a sperm with an ovum is called fertilisation.
During fertilisation, a sperm first makes contact with the zona pellucida — the membrane surrounding the ovum (Fig. 2.13). This contact triggers changes in the membrane that block any further sperms from entering, ensuring that only a single sperm fertilises the ovum.
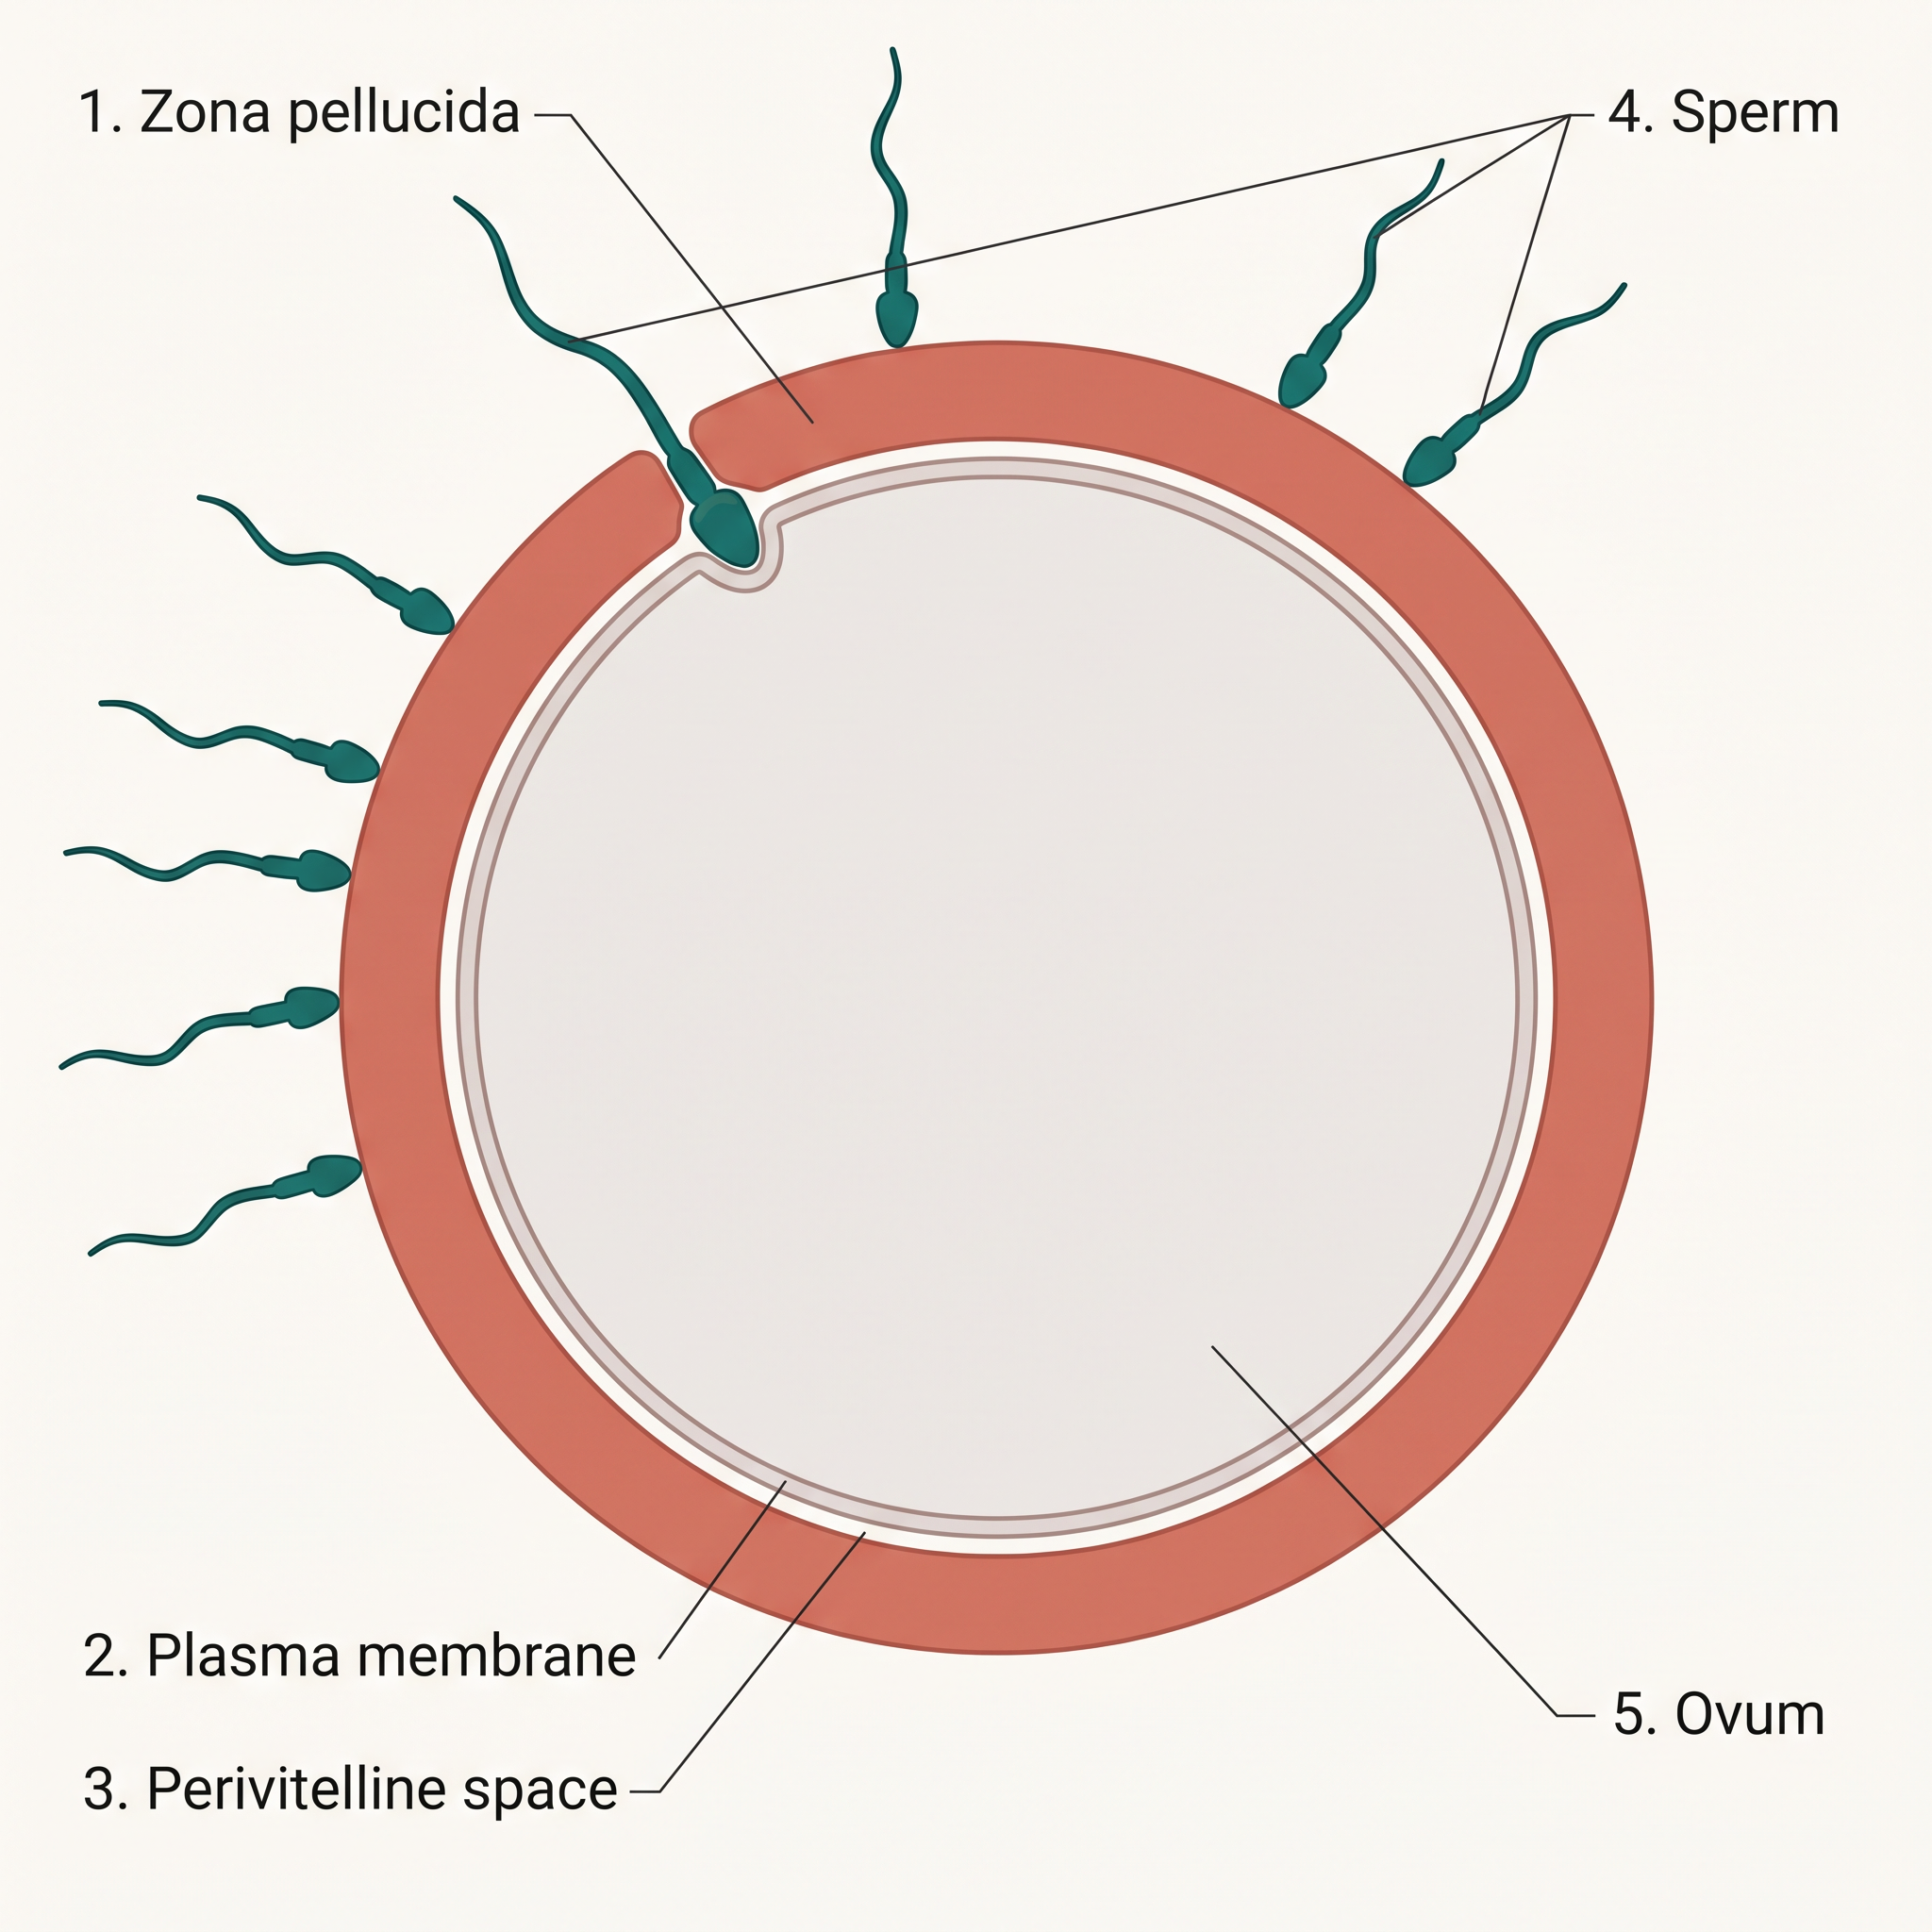
Fig. 2.13 – Ovum surrounded by sperms.
The enzymes released from the acrosome now help the sperm push its way through the zona pellucida and the plasma membrane into the cytoplasm of the ovum. The sperm’s entry stirs the secondary oocyte into completing its second meiotic division. Like the first, this division is unequal: it produces a second polar body and a haploid ovum (also called the ootid).
Then the haploid nucleus of the sperm and the haploid nucleus of the ovum fuse together to form a diploid zygote.
How the Baby’s Sex Is Decided
The sex of the baby is actually settled at this very moment of fertilisation. The sex-chromosome pattern is XX in the human female and XY in the male.
Because a female is XX, every ovum she produces carries an X chromosome. A male is XY, so his sperms are of two kinds: about 50 per cent carry an X chromosome and the other 50 per cent carry a Y. After fusion, the zygote will be XX if an X-bearing sperm fertilises the ovum, or XY if a Y-bearing sperm does. An XX zygote develops into a female baby and an XY zygote into a male (you will study these chromosomal patterns in detail in Chapter 5).
This is why, scientifically, it is correct to say that the sex of the baby is determined by the father, not the mother.
Cleavage and Formation of the Blastocyst
As the zygote moves through the isthmus of the oviduct toward the uterus, it begins dividing by mitosis — a series of divisions called cleavage (Fig. 2.12). Cleavage produces 2, 4, 8 and then 16 daughter cells called blastomeres.
An embryo with 8 to 16 blastomeres is called a morula (Fig. 2.12e). The morula keeps dividing and, as it moves deeper into the uterus, transforms into a blastocyst (Fig. 2.12g).
Inside the blastocyst, the blastomeres are arranged into two groups: an outer layer called the trophoblast, and an inner cluster of cells attached to the trophoblast called the inner cell mass. The complete sequence from insemination to implantation is summarised in FC 2.8.
Flowchart
FC 2.8 – Fertilisation to implantation: insemination → sperms swim through cervix → uterus → ampulla; ovum reaches ampulla → fertilisation → zygote → cleavage (2 → 4 → 8 → 16 blastomeres) → morula → blastocyst (trophoblast + inner cell mass) → implantation → pregnancy
Implantation
The trophoblast layer next attaches itself to the endometrium, while the inner cell mass becomes the developing embryo. After attachment, the uterine cells divide rapidly and grow over the blastocyst, so that the blastocyst becomes embedded within the endometrium of the uterus (Fig. 2.12, step h). This embedding is called implantation, and it leads to pregnancy.
2.6 Pregnancy and Embryonic Development
The Placenta
After implantation, finger-like outgrowths called chorionic villi appear on the trophoblast. These villi are surrounded by the uterine tissue and by maternal blood.
The chorionic villi and the uterine tissue interlock closely with each other (they become interdigitated) and together form a single structural and functional unit that links the developing embryo (the foetus) with the mother’s body. This unit is the placenta (Fig. 2.14).
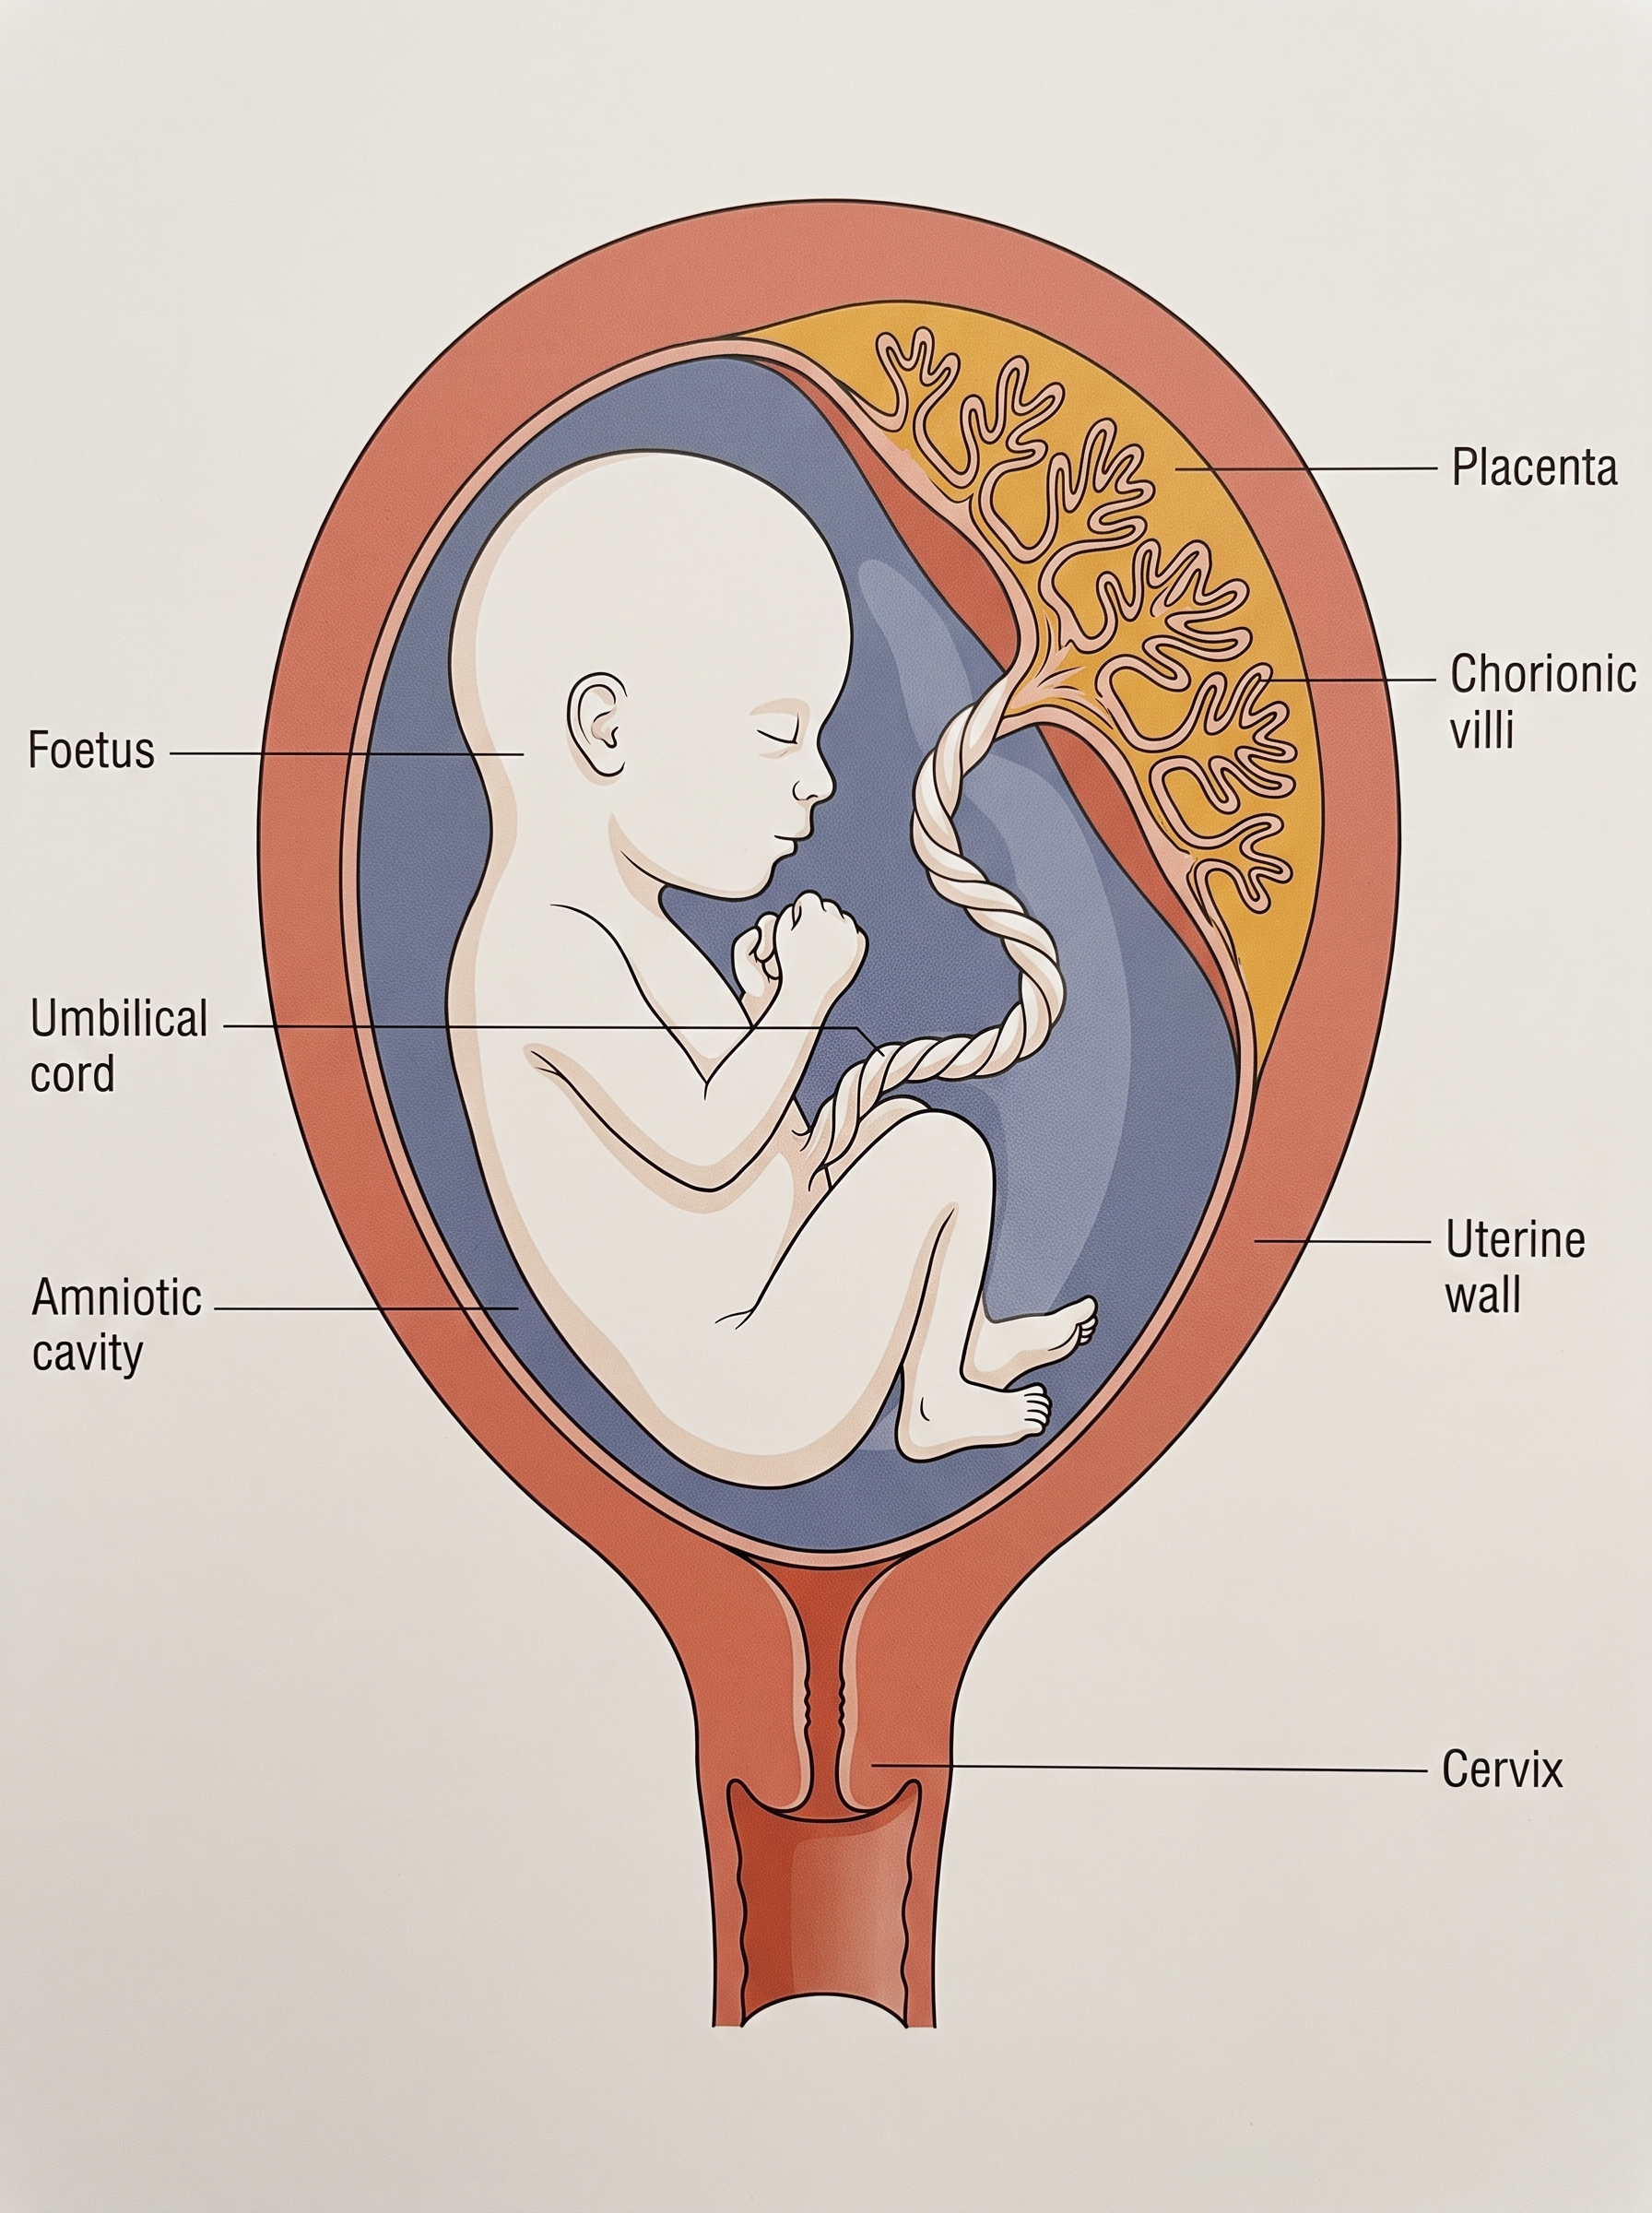
Fig. 2.14 – Human foetus within the uterus.
The placenta supplies oxygen and nutrients to the embryo, and it carries away the carbon dioxide and waste materials the embryo produces. It is connected to the embryo by the umbilical cord, which transports these substances to and from the embryo.
The placenta is not only an exchange organ; it also acts as an endocrine tissue — a hormone-producing tissue. It makes several hormones, including human chorionic gonadotropin (hCG), human placental lactogen (hPL), estrogens and progestogens. In the later phase of pregnancy, another hormone, relaxin, is secreted by the ovary.
It is worth remembering that hCG, hPL and relaxin are produced in a woman only during pregnancy. Alongside these, the levels of other hormones — estrogens, progestogens, cortisol, prolactin and thyroxine — rise several-fold in the mother’s blood. This increased hormone production is essential for supporting the growth of the foetus, for the metabolic changes in the mother, and for maintaining the pregnancy itself.
The Three Germ Layers
Immediately after implantation, the inner cell mass (the embryo) begins to differentiate. It first forms an outer layer, the ectoderm, and an inner layer, the endoderm. Soon a third layer, the mesoderm, appears between them. These three layers — the germ layers — go on to give rise to all the tissues and organs of the adult body.
The inner cell mass also contains special cells called stem cells, which have the potency to give rise to all the different tissues and organs of the body.
Month-by-Month Development
Human pregnancy lasts about 9 months, and the foetus reaches a series of milestones along the way (FC 2.9).
After one month, the embryo’s heart is formed; the first sign of the growing foetus can be picked up by listening to the heart sounds through a stethoscope. By the end of the second month, the foetus develops limbs and digits. By the end of 12 weeks — the end of the first trimester (each trimester is a period of about three months) — most of the major organ systems are formed; for example, the limbs and external genital organs are well developed.
The first movements of the foetus and the appearance of hair on the head are usually noticed during the fifth month. By the end of about 24 weeks — the end of the second trimester — the body is covered with fine hair, the eyelids separate, and the eyelashes form. By the end of nine months, the foetus is fully developed and ready for delivery.
Flowchart
FC 2.9 – Milestones of foetal development: 1 month (heart formed) → 2 months (limbs and digits) → 12 weeks / end of first trimester (major organ systems; limbs and external genitalia well developed) → 5th month (first movements; hair on head) → 24 weeks / end of second trimester (fine body hair; eyelids separate; eyelashes) → 9 months (fully developed, ready for delivery)
2.7 Parturition and Lactation
Parturition
The average length of human pregnancy is about 9 months, a period called the gestation period. At the end of pregnancy, vigorous contractions of the uterus push the fully formed foetus out of the mother’s body. This process of delivering the foetus — that is, childbirth — is called parturition.
Parturition is set off by a complex neuroendocrine mechanism — one that involves both the nervous system and hormones working together. The signals for parturition come from the fully developed foetus and the placenta, and they induce mild uterine contractions known as the foetal ejection reflex.
This reflex triggers the release of the hormone oxytocin from the mother’s pituitary gland. Oxytocin acts on the uterine muscle and produces stronger contractions, and these stronger contractions in turn cause even more oxytocin to be released. This self-amplifying loop — contraction leading to more oxytocin, and more oxytocin leading to still stronger contraction — continues until the contractions are powerful enough to expel the baby through the birth canal. This delivery is parturition. Soon after the infant is born, the placenta too is expelled from the uterus. The whole self-reinforcing sequence is shown in FC 2.10.
Flowchart
FC 2.10 – Parturition (a positive-feedback loop): fully developed foetus + placenta → signals → mild uterine contractions (foetal ejection reflex) → oxytocin released from maternal pituitary → stronger uterine contractions → (loop back) more oxytocin → progressively stronger contractions → baby expelled through birth canal (parturition) → placenta expelled
Lactation
The mammary glands of the female undergo differentiation during pregnancy and begin producing milk towards the end of pregnancy, by the process called lactation. This is what allows the mother to feed the newborn baby.
The milk produced during the first few days of lactation is called colostrum. Colostrum contains several antibodies — protective defence proteins — that are absolutely essential for building resistance in the newborn.
2.8 Summary
- Humans are sexually reproducing and viviparous (they give birth to live young).
- The male reproductive system is made up of a pair of testes, the male sex accessory ducts, the accessory glands, and the external genitalia.
- Each testis contains about 250 testicular lobules, and each lobule holds one to three highly coiled seminiferous tubules.
- Each seminiferous tubule is lined inside by spermatogonia and Sertoli cells. The spermatogonia undergo meiotic divisions to form sperms, while the Sertoli cells nourish the dividing germ cells.
- The Leydig cells, lying outside the seminiferous tubules, synthesise and secrete the male hormones called androgens. The male external genitalia is the penis.
- The female reproductive system consists of a pair of ovaries, a pair of oviducts, a uterus, a vagina, the external genitalia, and a pair of mammary glands.
- The ovaries produce the female gamete (ovum) and some steroid (ovarian) hormones. Ovarian follicles at different stages of development lie embedded in the stroma.
- The oviducts, uterus and vagina are the female accessory ducts. The uterine wall has three layers: perimetrium, myometrium and endometrium.
- The female external genitalia include the mons pubis, labia majora, labia minora, hymen and clitoris. The mammary glands are one of the female secondary sexual characteristics.
- Spermatogenesis produces sperms, which are then carried by the male accessory ducts. A normal sperm has a head, neck, middle piece and tail.
- The formation of the mature female gamete is called oogenesis.
- The reproductive cycle of female primates is the menstrual cycle. It begins only after puberty is reached, and during each cycle just one ovum is released at ovulation. The cyclical changes in the ovary and the uterus are driven by changing levels of pituitary and ovarian hormones.
- After coitus, sperms travel to the ampulla, where a sperm fertilises the ovum to form a diploid zygote.
- The presence of an X or a Y chromosome in the fertilising sperm decides the sex of the embryo.
- The zygote divides repeatedly by mitosis to form a blastocyst, which is implanted in the uterus, establishing pregnancy. After about nine months, the fully developed foetus is ready for delivery.
- Childbirth is called parturition and is brought about by a complex neuroendocrine mechanism involving cortisol, estrogens and oxytocin.
- The mammary glands differentiate during pregnancy and secrete milk after childbirth; the newborn is fed this milk (lactation) during its early months of growth.
Flowchart
FC 2.11 – The overall course of human reproduction: gametogenesis (spermatogenesis + oogenesis) → insemination → fertilisation in the ampulla → diploid zygote → cleavage → morula → blastocyst → implantation → pregnancy and embryonic development (placenta) → parturition → lactation
2.9 Points to Ponder
- Sperm formation needs the testes to stay a few degrees cooler than the body core. What might this suggest about how heat, lifestyle, or clothing could affect male fertility?
- A female is born with a fixed stock of egg-precursor cells, while a male keeps making fresh sperm throughout life. What could this basic difference mean for how the reproductive systems of men and women change with age?
- The chapter notes that we are not yet certain whether the first polar body divides again or simply degenerates. Why might such a small, unresolved detail still be worth a scientist’s careful study?
- The placenta is at once an organ of exchange and a gland that makes hormones. Why might it be an advantage for a single temporary structure to carry out both of these very different roles during pregnancy?
- Colostrum carries ready-made antibodies to the newborn in the very first days of feeding. What does this tell you about why the timing of a baby’s first feeds can matter so much?
- Parturition is driven by a self-amplifying (positive-feedback) loop, whereas most body processes rely on negative feedback to stay steady. Why might childbirth be one of the few situations where positive feedback is useful rather than harmful?
- Scientifically, it is the father’s sperm — carrying an X or a Y — that decides a baby’s sex, yet mothers are often wrongly blamed for the sex of a child. How might a clear understanding of this biology help change such attitudes in society?
2.10 NCERT Questions
- Fill in the blanks:
- Humans reproduce __________ (asexually/sexually)
- Humans are __________ (oviparous, viviparous, ovoviviparous)
- Fertilisation is __________ in humans (external/internal)
- Male and female gametes are __________ (diploid/haploid)
- Zygote is __________ (diploid/haploid)
- The process of release of ovum from a mature follicle is called __________
- Ovulation is induced by a hormone called __________
- The fusion of male and female gametes is called __________
- Fertilisation takes place in __________
- Zygote divides to form __________ which is implanted in uterus.
- The structure which provides vascular connection between foetus and uterus is called __________
- Draw a labelled diagram of the male reproductive system.
- Draw a labelled diagram of the female reproductive system.
- Write two major functions each of the testis and the ovary.
- Describe the structure of a seminiferous tubule.
- What is spermatogenesis? Briefly describe the process of spermatogenesis.
- Name the hormones involved in the regulation of spermatogenesis.
- Define spermiogenesis and spermiation.
- Draw a labelled diagram of a sperm.
- What are the major components of seminal plasma?
- What are the major functions of the male accessory ducts and glands?
- What is oogenesis? Give a brief account of oogenesis.
- Draw a labelled diagram of a section through the ovary.
- Draw a labelled diagram of a Graafian follicle.
- Name the functions of the following:
- Corpus luteum
- Endometrium
- Acrosome
- Sperm tail
- Fimbriae
- Identify True/False statements. Correct each false statement to make it true.
- Androgens are produced by Sertoli cells. (True/False)
- Spermatozoa get nutrition from Sertoli cells. (True/False)
- Leydig cells are found in the ovary. (True/False)
- Leydig cells synthesise androgens. (True/False)
- Oogenesis takes place in the corpus luteum. (True/False)
- Menstrual cycle ceases during pregnancy. (True/False)
- Presence or absence of hymen is not a reliable indicator of virginity or sexual experience. (True/False)
- What is menstrual cycle? Which hormones regulate the menstrual cycle?
- What is parturition? Which hormones are involved in the induction of parturition?
- In our society, women are often blamed for giving birth to daughters. Can you explain why this is not correct?
- How many eggs are released by a human ovary in a month? How many eggs do you think would have been released if the mother gave birth to identical twins? Would your answer change if the twins born were fraternal?
- How many eggs do you think were released by the ovary of a female dog which gave birth to 6 puppies?
2.11 Check Your Concepts
- Why are the testes located in the scrotum, outside the abdominal cavity, rather than inside the body like most other organs? Explain the functional reason.
- Distinguish between Sertoli cells and Leydig cells with respect to their location and function.
- Assertion (A): The middle piece of a sperm is packed with numerous mitochondria. Reason (R): The mitochondria supply the energy needed for the beating of the sperm’s tail. Choose the correct option:
- Both A and R are true, and R is the correct explanation of A.
- Both A and R are true, but R is not the correct explanation of A.
- A is true, but R is false.
- A is false, but R is true.
- Trace the correct path of a sperm from its site of formation to its exit from the body by arranging the following in the proper sequence: vas deferens, seminiferous tubules, urethra, rete testis, epididymis, vasa efferentia, ejaculatory duct.
- A spermatogonium contains 46 chromosomes. State the number of chromosomes present in (a) a primary spermatocyte, (b) a secondary spermatocyte, and (c) a spermatid, and explain why the number changes.
- Give two major differences between spermatogenesis and oogenesis.
- Why does the secondary oocyte retain almost all of the cytoplasm during the first meiotic division, leaving the first polar body very small? What advantage does this offer?
- Arrange the following stages of follicle development in the correct sequence: Graafian follicle, primary follicle, secondary follicle, tertiary follicle.
- What is the LH surge? State its role in the menstrual cycle.
- What happens to the corpus luteum if fertilisation does not occur, and how does this lead to menstruation?
- Assertion (A): During pregnancy, menstruation does not occur. Reason (R): The endometrium is maintained during pregnancy and is not shed. Choose the correct option:
- Both A and R are true, and R is the correct explanation of A.
- Both A and R are true, but R is not the correct explanation of A.
- A is true, but R is false.
- A is false, but R is true.
- Explain why only a single sperm is normally able to fertilise an ovum, even though millions of sperms reach the female tract.
- Arrange the following developmental stages in the correct order: blastocyst, zygote, morula, 8-celled embryo. At which stage does implantation occur?
- Match the structures in Column I with their correct roles in Column II.
| Column I | Column II |
|---|---|
| a. Placenta | i. attaches to the endometrium during implantation |
| b. Umbilical cord | ii. supplies oxygen and nutrients to the foetus and removes wastes |
| c. Colostrum | iii. carries antibodies to the newborn |
| d. Trophoblast | iv. transports substances between the placenta and the embryo |
- Parturition is described as a positive-feedback (self-amplifying) process. Explain how the interaction between uterine contractions and oxytocin makes the contractions progressively stronger.
- Name the three germ layers formed from the inner cell mass, and state their overall significance in the developing embryo.
- Why is a fallopian tube blocked by scarring a common cause of female infertility? Relate your answer to the site where fertilisation normally takes place.
- Differentiate between menarche and menopause.