Chapter 14: Breathing and Exchange of Gases
In the 1770s, the English scientist Joseph Priestley performed a set of simple but striking experiments with sealed glass jars. When he placed a burning candle inside a closed jar, the flame soon flickered and died. When he shut a live mouse into a similar jar, the animal grew distressed and could not survive for long. Something in the trapped air, Priestley realised, was being “used up” — and something else was being added that made the air unfit.
Then came the experiment that made him famous. Priestley placed a sprig of green mint into a jar of this “spoiled” air and left it in sunlight for several days. To his surprise, the air was somehow refreshed: a candle could burn in it again, and a mouse could breathe in it once more. The plant had restored what the flame and the animal had taken away.
Priestley had stumbled upon oxygen — the gas that living cells consume — and upon the fact that breathing removes it from the air while returning carbon dioxide. A few years later, Antoine Lavoisier explained that respiration is, in effect, a slow, controlled burning inside the body.
Every breath you take is part of this same exchange. But how exactly does air move in and out of your lungs, and how does oxygen reach every cell hidden deep inside you?

Fig. 14.0 – Priestley’s bell jar experiments.
By the end of this chapter, you will be able to answer each of these questions.
14.1 Respiratory Organs
Why Every Cell Needs Oxygen
Every living cell is like a tiny engine that must keep working — building materials, moving substances, and carrying out its daily activities. All of this needs energy. Cells obtain this energy by breaking down simple food molecules such as glucose (a sugar), amino acids (the building blocks of proteins), and fatty acids (parts of fats). These breakdown reactions that release energy are called catabolic reactions.
Oxygen (\(O_2\)) is used, indirectly, to carry out this breakdown of food inside the cells. But there is a catch: the same reactions also produce carbon dioxide (\(CO_2\)), a waste gas that is harmful if it builds up. So a cell has two constant needs — a steady supply of \(O_2\) coming in, and continuous removal of the \(CO_2\) it makes.
The process by which an organism draws in \(O_2\) from its surroundings and gives out the \(CO_2\) produced by its cells is called breathing, more commonly known as respiration. Place your hands on your chest and you will feel it move up and down — that steady rise and fall is breathing in action.
There is an important word-trap hidden here. The “respiration” we mean in this chapter is the exchange of gases with the outside world. It is not the same as cellular respiration, which is the chemical breakdown of glucose inside the cell to release energy (studied in the chapter on respiration in plants). Breathing supplies the raw \(O_2\) and carries away the \(CO_2\); cellular respiration is the actual burning of fuel deep inside the cell.
How Different Animals Breathe
Not all animals breathe the same way. The mechanism an animal uses depends mainly on two things — the habitat it lives in (water or land) and its level of organisation (how simple or complex its body is).
In the simplest animals, gas exchange needs no special organ at all. Lower invertebrates such as sponges, coelenterates (like Hydra), and flatworms simply let \(O_2\) and \(CO_2\) pass in and out across their entire body surface by diffusion — the natural movement of a gas from where it is more concentrated to where it is less concentrated. This works only because these animals are small and thin, so no cell is ever far from the surface.
As animals become larger and more complex, dedicated structures appear. Earthworms breathe through their moist cuticle — the thin, damp outer skin — a mode called cutaneous respiration. Insects have a branching network of tiny air tubes called tracheal tubes that carry atmospheric air directly to the tissues inside the body.
Many water-dwelling animals use gills — special outgrowths richly supplied with blood vessels (vascularised), through which dissolved \(O_2\) is picked up from water. Breathing through gills is called branchial respiration, and it is used by most aquatic arthropods (like prawns) and molluscs, and by fishes.
Land animals face a different problem: they must protect a moist exchange surface from drying out. For this, terrestrial forms use lungs — vascularised, bag-like organs kept inside the body — in a mode called pulmonary respiration. Among vertebrates, fishes rely on gills, while amphibians, reptiles, birds and mammals all breathe through lungs. Amphibians such as frogs are versatile: besides lungs, they can also exchange gases through their moist skin (cutaneous respiration).
Notice the common thread running through all these structures: each provides a thin, moist, richly vascularised surface across which gases can diffuse. Whether it is a flatworm’s body wall or a mammal’s lung, the exchange surface always follows the same design logic.
In NEET and board exams, this section is most often tested by matching an animal group to its respiratory organ, or through assertion–reason statements (for example, “frogs can survive underwater for a while — because they can respire through their skin”). Keeping the compare table clear in your mind handles most such questions.
14.1.1 Human Respiratory System
The Path Air Takes
Air enters the human body through a pair of external nostrils that open just above the upper lips. From there it passes through the nasal passage into a nasal chamber, where it is filtered and warmed.
The nasal chamber opens into the pharynx — a region of the throat that is shared by both food and air, making it a common passage for the two. The pharynx then opens, through the larynx, into the trachea (the windpipe). The larynx is a cartilaginous box (a box made of firm but flexible cartilage) that helps produce sound, which is why it is popularly called the sound box.
Sharing one passage for food and air creates a risk: food could slip into the airway. To prevent this, during swallowing a thin, elastic, cartilaginous flap called the epiglottis folds over the opening of the larynx (the glottis), sealing off the air route so that food is guided into the food pipe instead. The whole route from nostrils down to the trachea is summarised in FC 14.1.
Flowchart
FC 14.1 – Path of air through the human respiratory tract: External nostrils → nasal chamber → pharynx → larynx (glottis) → trachea → primary bronchi → secondary bronchi → tertiary bronchi → bronchioles → terminal bronchioles → alveoli.
From Windpipe to Air Sacs
The trachea is a straight tube that runs down to the mid-thoracic cavity. At the level of the 5th thoracic vertebra, it divides into a right and a left primary bronchus (plural: bronchi), one entering each lung.
Inside the lungs, each primary bronchus divides again and again — into secondary and tertiary bronchi, then into finer and finer bronchioles, ending in extremely thin terminal bronchioles. This repeated branching is often compared to an upside-down tree, with the trachea as the trunk and the bronchioles as its twigs.
To stay open against the pressure changes of breathing, the trachea, the primary, secondary and tertiary bronchi, and the initial bronchioles are supported by incomplete cartilaginous rings (C-shaped rings of cartilage).
Each terminal bronchiole finally opens into a cluster of very thin, irregular-walled, richly vascularised, bag-like structures called alveoli (singular: alveolus). It is here — and only here — that gases are actually exchanged with the blood. The entire branching network of bronchi, bronchioles and alveoli together makes up the lungs, as shown in Fig. 14.1.
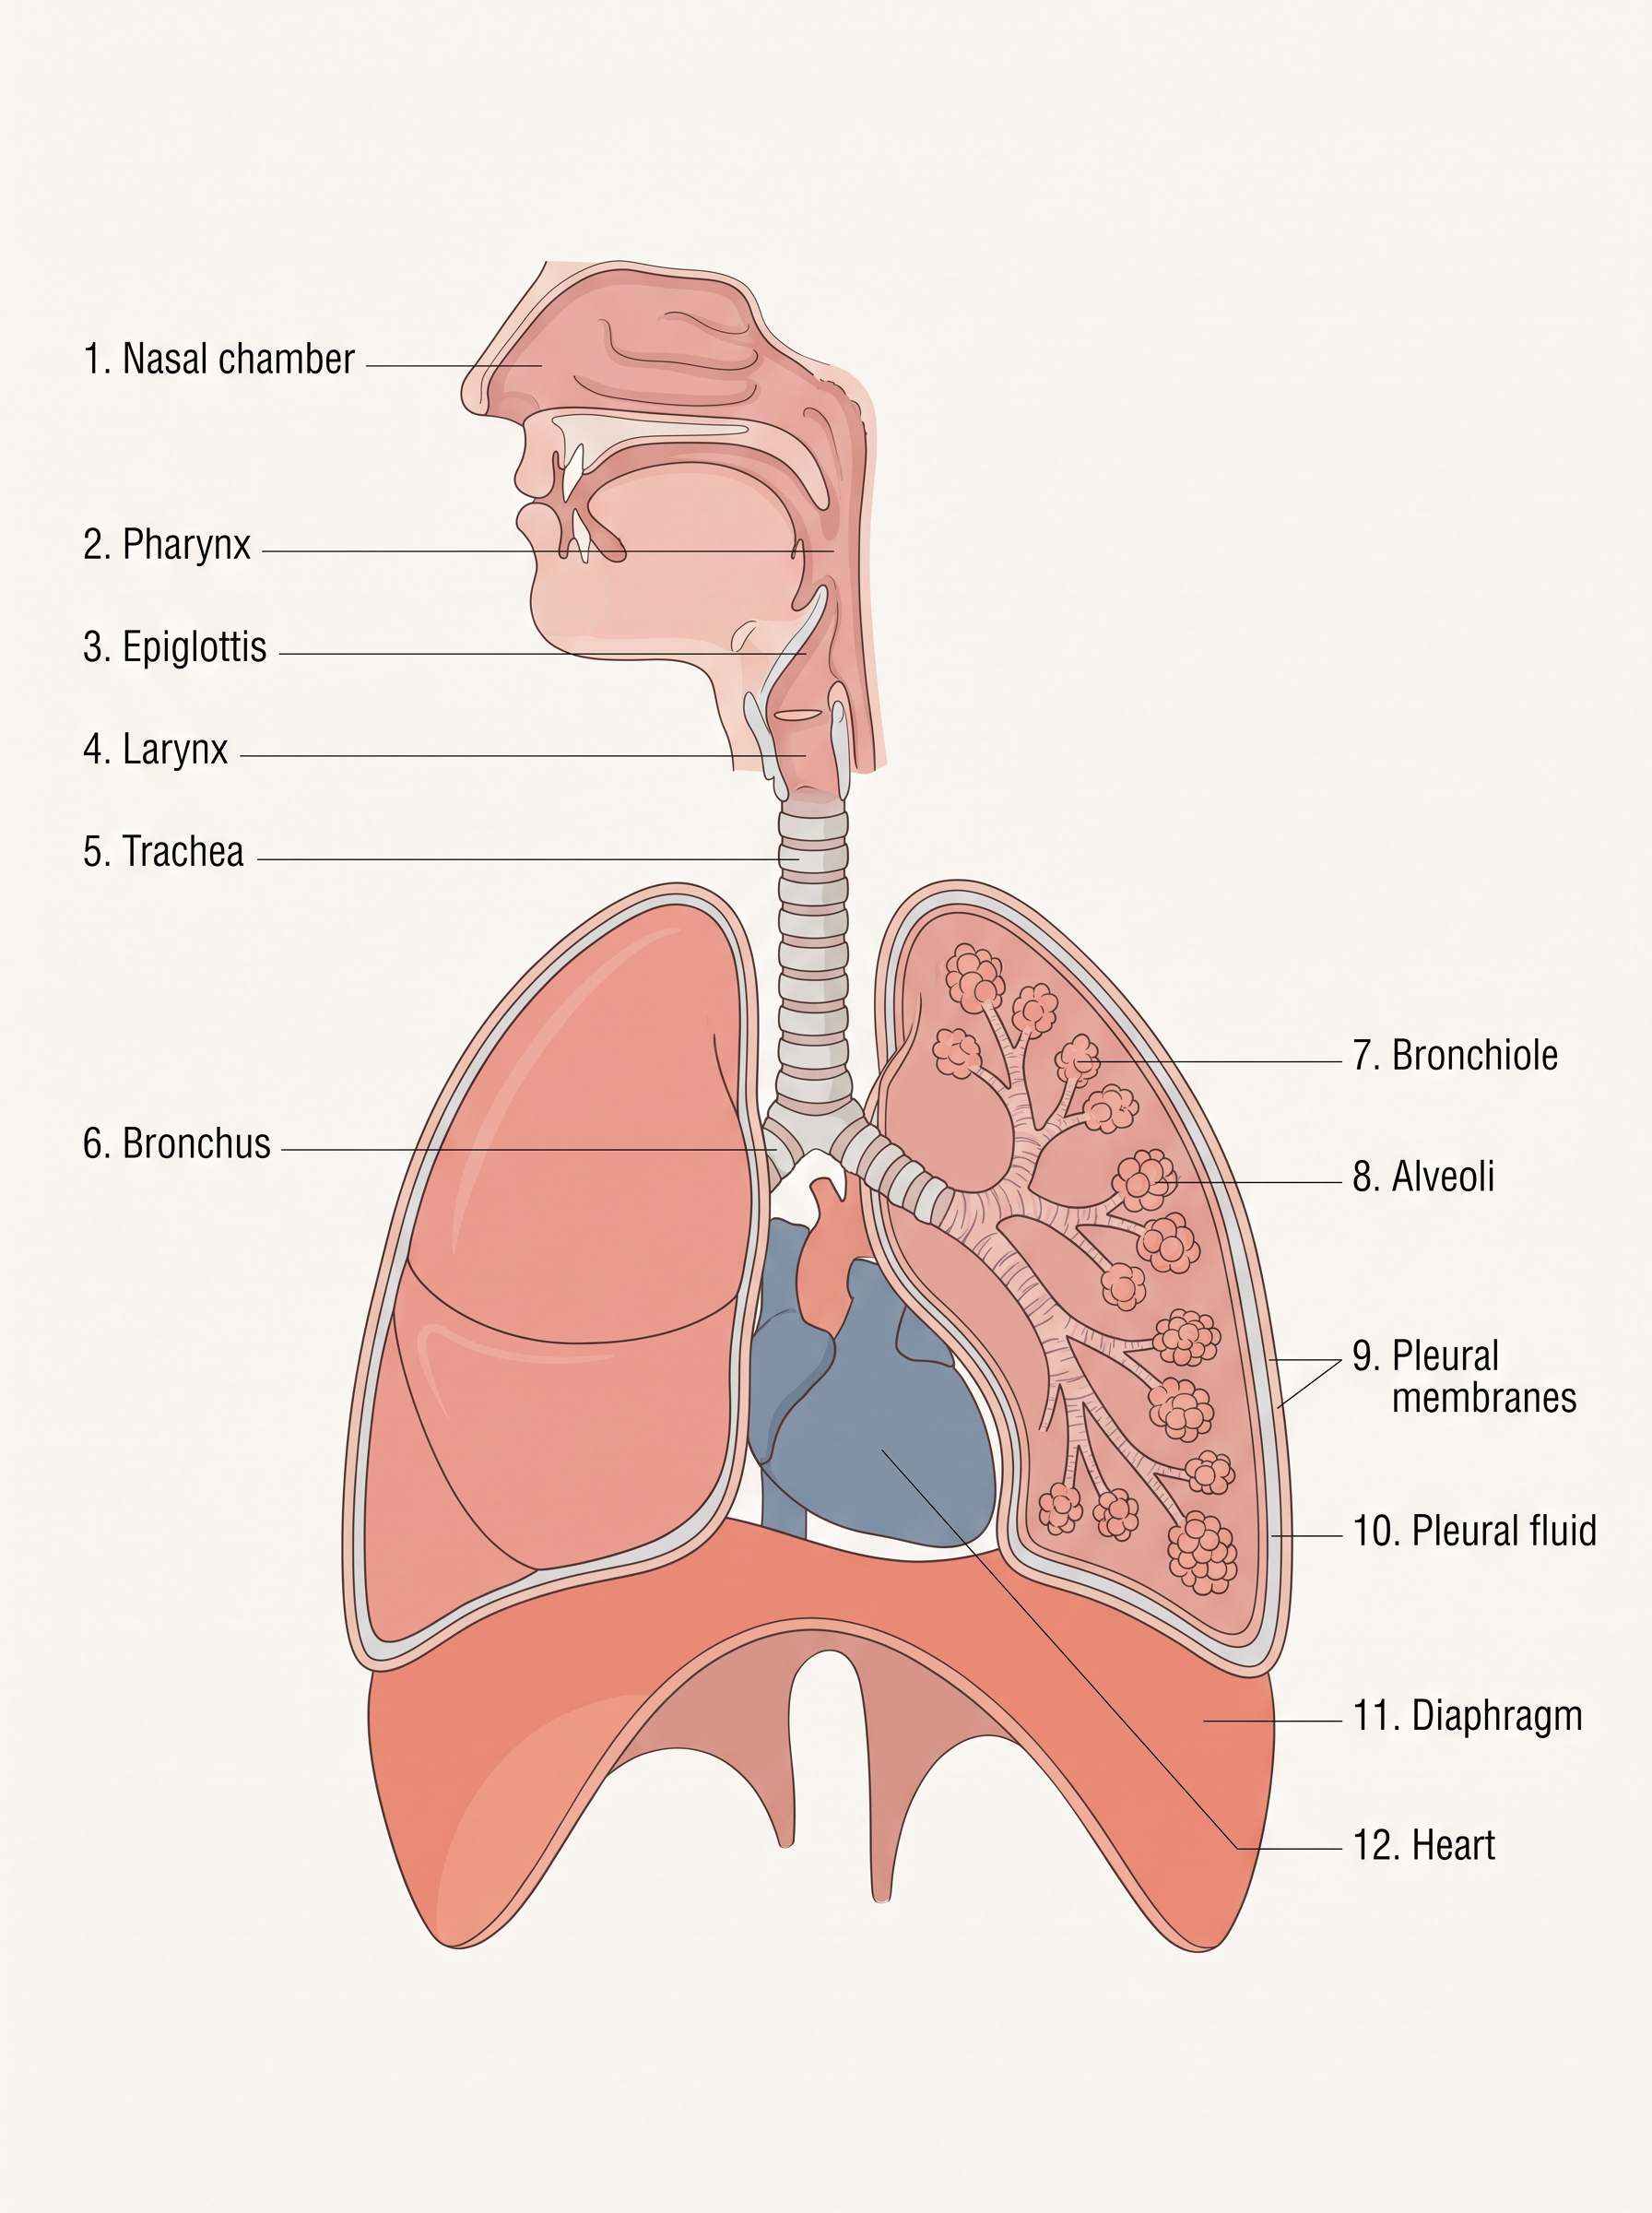
Fig. 14.1 – The human respiratory system.
The Lungs and Their Coverings
We have two lungs, and each is wrapped in a double-layered pleura — two thin membranes with a little pleural fluid in the space between them. This fluid acts as a lubricant, reducing friction as the lung surface rubs against the chest wall with every breath.
The outer pleural membrane stays in close contact with the thoracic (chest) wall lining, while the inner pleural membrane clings to the lung surface itself. This snug arrangement lets the lungs follow the movements of the chest wall faithfully.
Two Working Zones of the Airway
The respiratory system is not one uniform tube; it has two functional zones. The stretch running from the external nostrils down to the terminal bronchioles is the conducting part. The alveoli and their ducts form the respiratory or exchange part.
The conducting part does exactly what its name suggests — it conducts (transports) atmospheric air to the alveoli. Along the way it also cleans the air of dust and foreign particles, moistens (humidifies) it, and warms it to body temperature. The exchange part is where the real business happens: the actual diffusion of \(O_2\) and \(CO_2\) between the blood and the air.
The Air-Tight Thoracic Chamber
The lungs sit inside the thoracic chamber (chest cavity), which is anatomically an air-tight box. Its walls are formed on the back (dorsal side) by the vertebral column, on the front (ventral side) by the sternum (breastbone), on the sides by the ribs, and on the floor by the dome-shaped diaphragm (a sheet of muscle separating chest from abdomen).
This sealed design matters enormously. Because the chamber is air-tight, any change in the volume of the thoracic cavity is immediately passed on to the lung (pulmonary) cavity inside it. We cannot squeeze or stretch our lungs directly with our hands — so the only way to move air in and out is to change the volume of the chamber around them. That is precisely how breathing works, as the next section will show.
The Complete Sequence of Respiration
Putting it all together, respiration in humans is not a single event but a chain of five linked steps, summarised in FC 14.2:
Breathing (pulmonary ventilation) — atmospheric air is drawn in, and \(CO_2\)-rich alveolar air is pushed out.
Diffusion of gases (\(O_2\) and \(CO_2\)) across the alveolar membrane.
Transport of gases by the blood.
Diffusion of \(O_2\) and \(CO_2\) between the blood and the body tissues.
Utilisation of \(O_2\) by the cells for catabolic reactions, with the resulting release of \(CO_2\) (this is cellular respiration, studied in the chapter on respiration in plants).
Flowchart
FC 14.2 – The five steps of respiration: breathing (air in / \(CO_2\) out at lungs) → diffusion of gases across alveolar membrane → transport of gases by blood → diffusion of gases between blood and tissues → utilisation of \(O_2\) by cells (cellular respiration) releasing \(CO_2\) → (the \(CO_2\) returns via blood to the lungs).
In exams, this subsection is a favourite for diagram-labelling of Fig. 14.1 and for sequence-ordering questions (arranging the path of air correctly) — so trace FC 14.1 until the order feels automatic.
14.2 Mechanism of Breathing
Air Moves Down a Pressure Gradient
Breathing happens in two stages. Inspiration is the stage in which fresh atmospheric air is drawn into the lungs, and expiration is the stage in which the used, \(CO_2\)-rich alveolar air is pushed back out.
But what makes air actually move in a chosen direction? Air, like any gas, flows from a region of higher pressure to a region of lower pressure. So to move air into or out of the lungs, the body creates a pressure gradient — a difference in pressure between the lungs and the outside atmosphere.
The pressure of air inside the lungs is called the intra-pulmonary pressure. For air to rush in (inspiration), this intra-pulmonary pressure must drop below the atmospheric pressure — in other words, a slight negative pressure must build up inside the lungs relative to the outside. For air to be pushed out (expiration), the intra-pulmonary pressure must rise above the atmospheric pressure.
This all rests on a simple physical rule: in a closed container, if you increase the volume the pressure of the gas inside falls, and if you decrease the volume the pressure rises. Since we cannot touch our lungs directly, the body changes lung pressure by changing the volume of the air-tight thoracic chamber around them.
The two muscle groups that change the chamber’s volume are the diaphragm (the dome-shaped muscle floor of the chest) and the intercostal muscles — the external and internal intercostals that lie between the ribs.
How We Breathe In
Inspiration is an active process — it is driven by muscle contraction. It begins when the diaphragm contracts. As it contracts, the dome flattens and pulls downward, increasing the volume of the thoracic chamber along its front-to-back length (the antero-posterior axis).
At the same time, the external intercostal muscles contract, lifting the ribs and the sternum upward and outward. This enlarges the chest from front to back and side to side (the dorso-ventral axis). The two actions together produce an overall increase in thoracic volume, and because the chamber is air-tight, the lungs expand to match it — pulmonary volume increases too. This whole sequence is shown in Fig. 14.2a and summarised in FC 14.3.
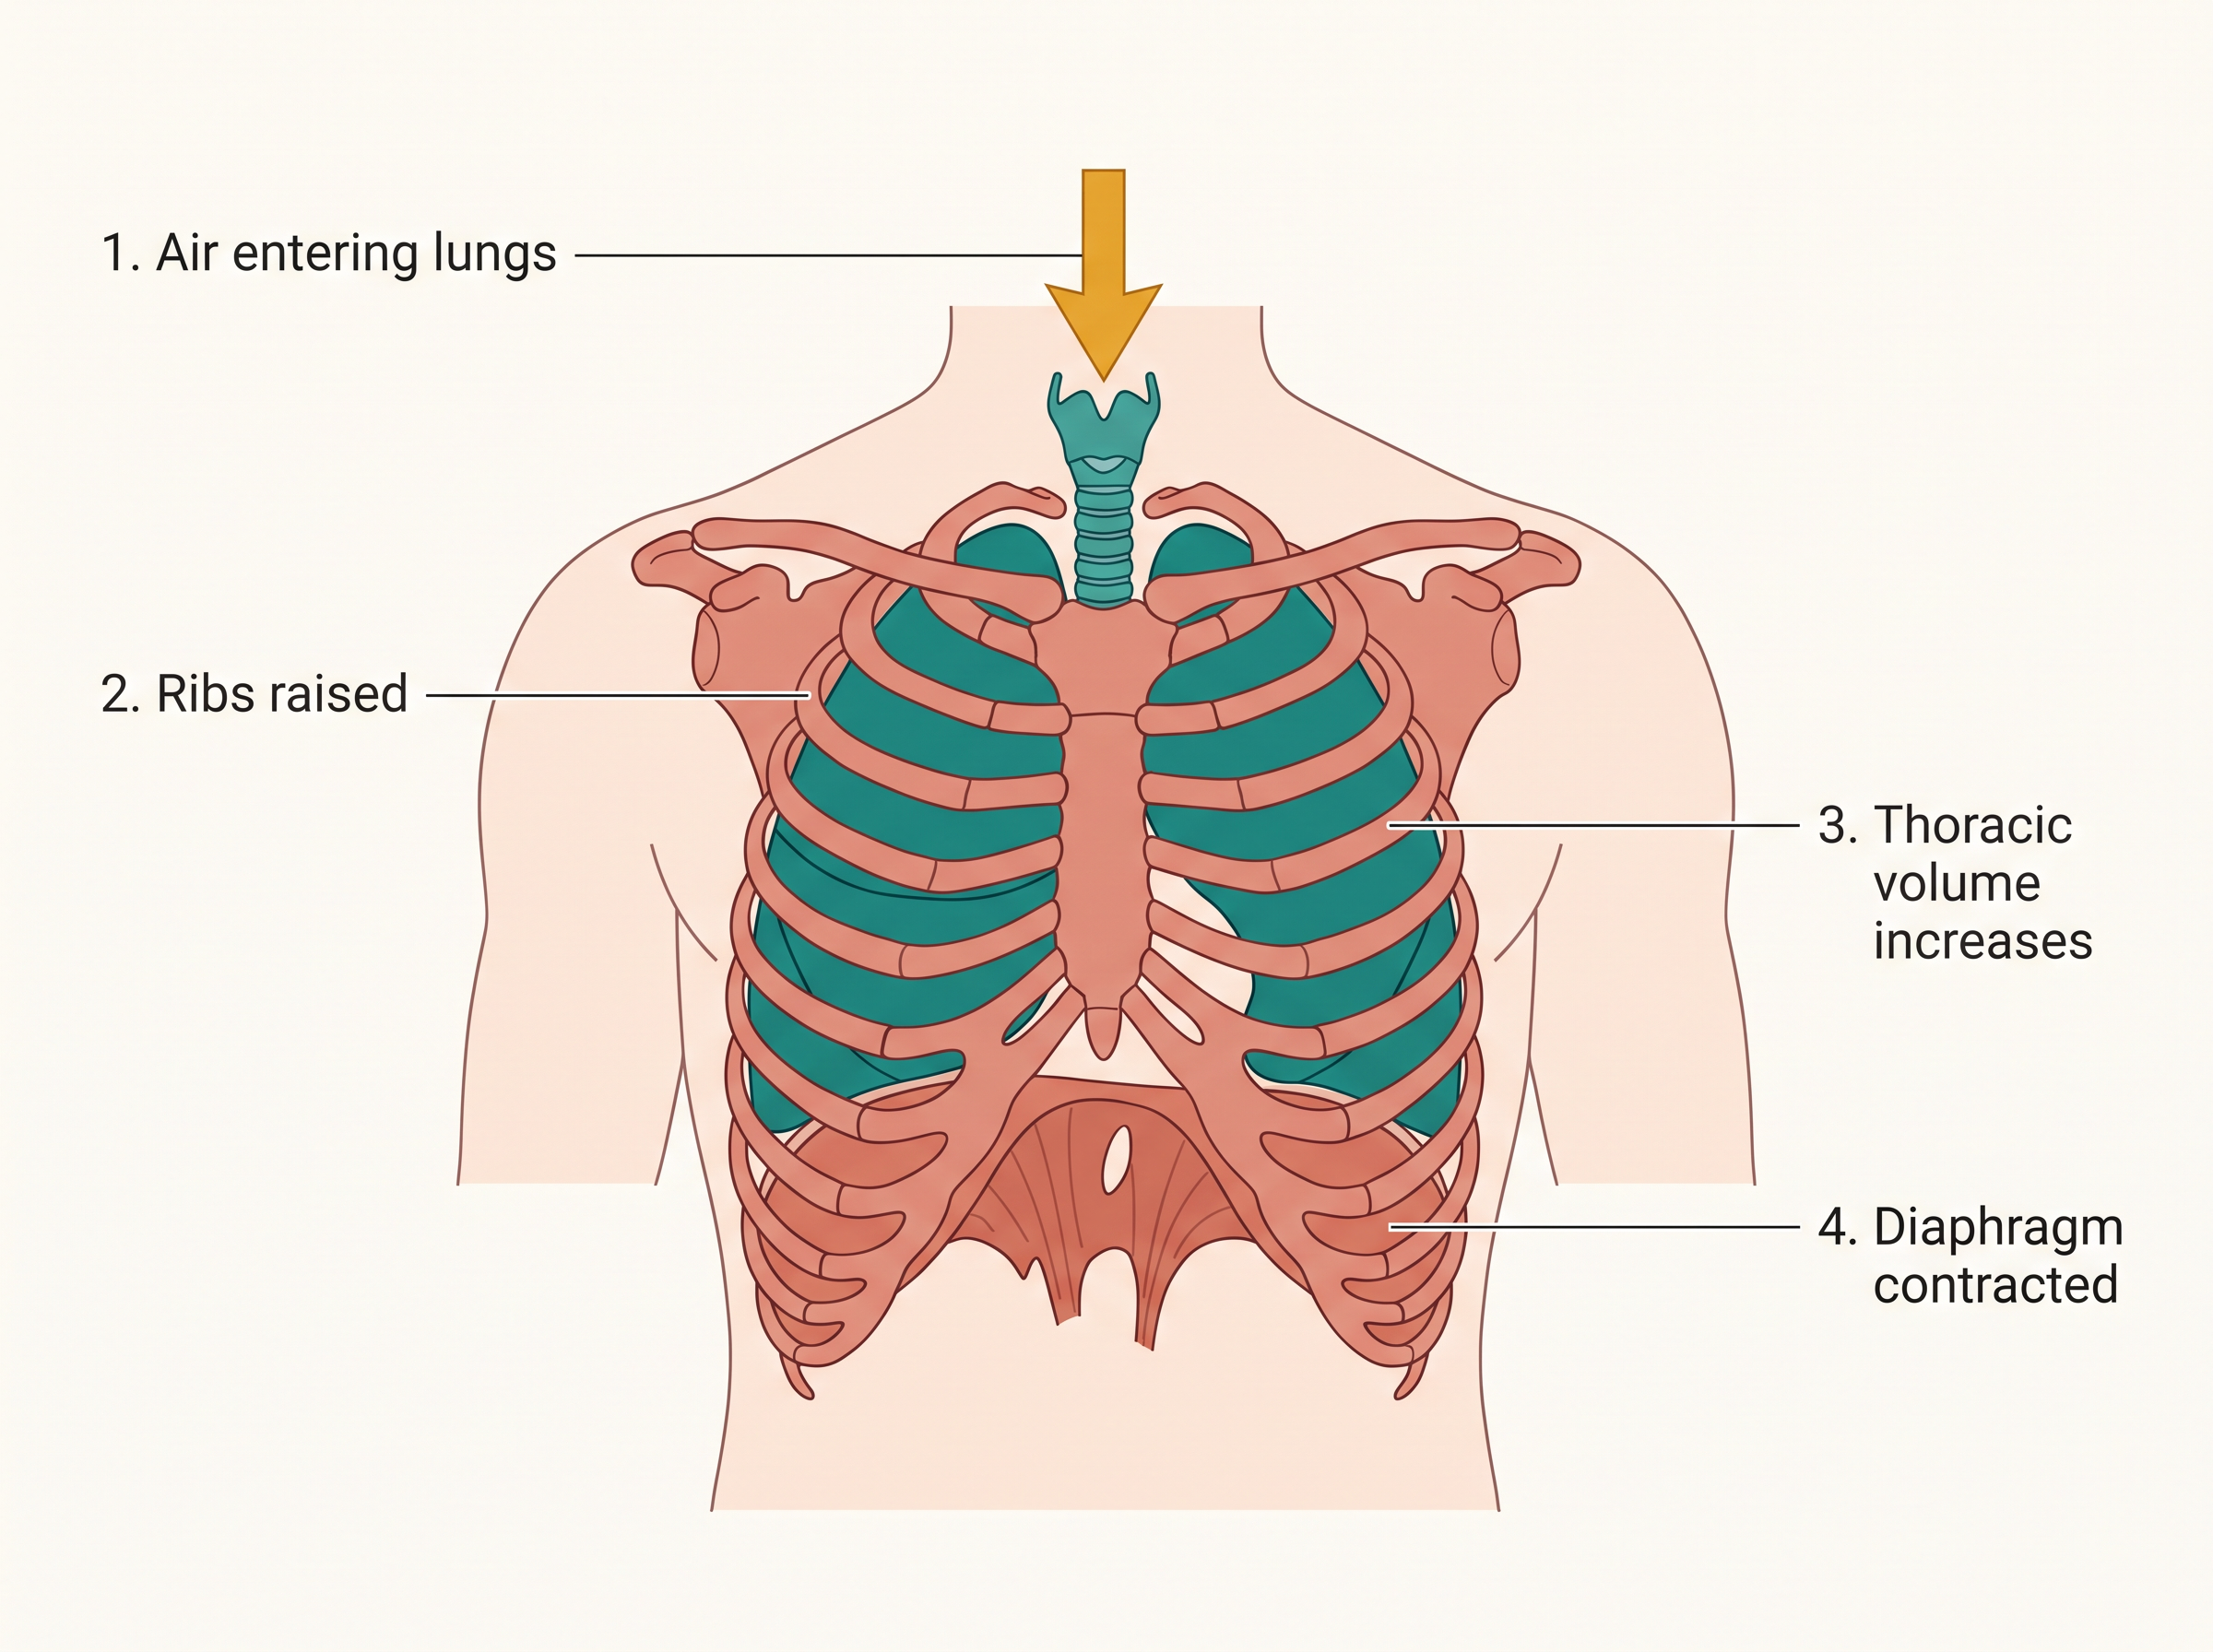
Fig. 14.2a – Mechanism of breathing: Inspiration.
Flowchart
FC 14.3 – Inspiration cascade: diaphragm contracts (flattens) + external intercostals contract (ribs and sternum lift) → thoracic volume increases → pulmonary volume increases → intra-pulmonary pressure falls below atmospheric → air rushes into the lungs.
As the lungs expand, their internal volume rises and — following the pressure–volume principle — the intra-pulmonary pressure falls below the atmospheric pressure. This pressure difference forces air from outside to flow into the lungs. That is inspiration.
How We Breathe Out
Expiration is largely a passive process during quiet breathing — it happens mostly by relaxation, not effort. When the diaphragm and the external intercostal muscles relax, the diaphragm springs back into its dome shape and the ribs and sternum sink to their normal positions.
This reduces the thoracic volume, and therefore the pulmonary volume, as shown in Fig. 14.2b. The lungs are squeezed slightly, raising the intra-pulmonary pressure to just above atmospheric pressure — and the higher inside pressure expels air out of the lungs. That is expiration. The reverse cascade is summarised in FC 14.4.
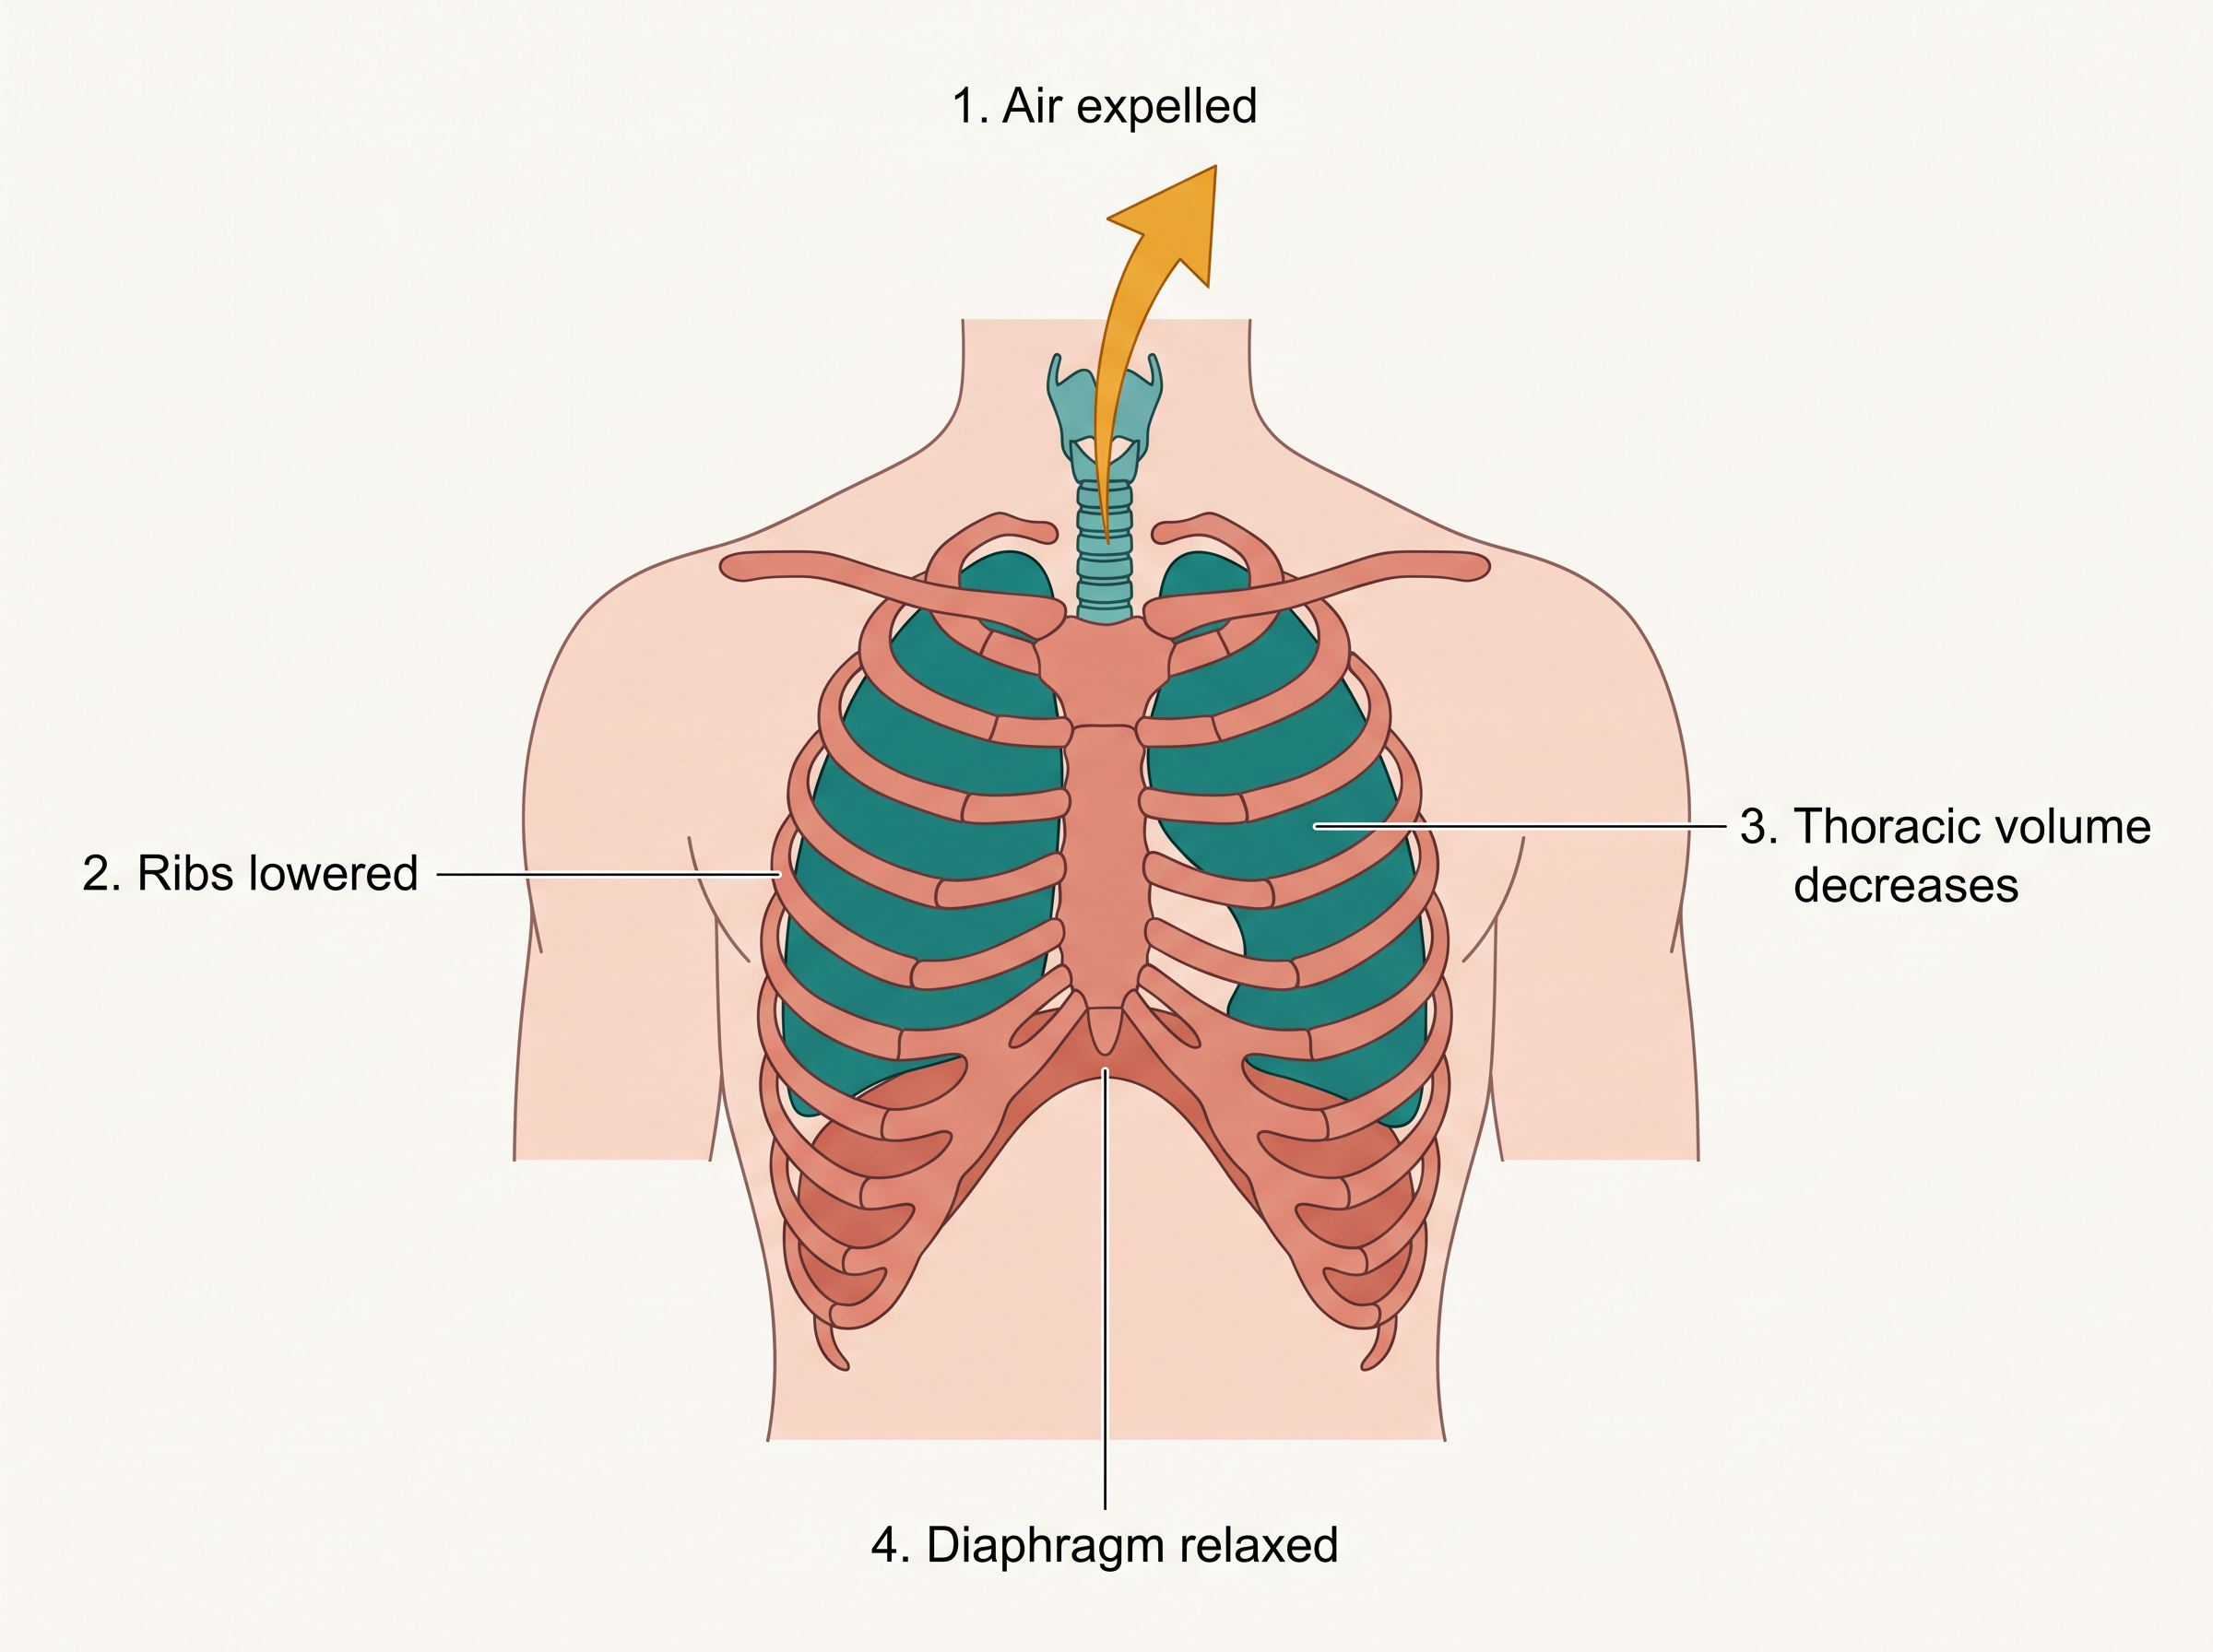
Fig. 14.2b – Mechanism of breathing: Expiration.
Flowchart
FC 14.4 – Expiration cascade: diaphragm relaxes (arches up) + external intercostals relax (ribs and sternum lower) → thoracic volume decreases → pulmonary volume decreases → intra-pulmonary pressure rises above atmospheric → air is pushed out of the lungs.
Forced Breathing and Measuring the Breath
The breathing described above is quiet, resting breathing. We can also breathe more forcefully. During deep or laboured breathing, extra muscles pitch in — the internal intercostal muscles and additional muscles of the abdomen — to increase the strength of both inspiration and expiration.
On average, a healthy human breathes about 12–16 times per minute. The volume of air moved during these breathing movements can be measured with an instrument called a spirometer, which is widely used in clinics to assess how well a person’s lungs are working. The specific volumes and capacities it measures are described in the next subsection.
For exams, inspiration and expiration are commonly tested through assertion–reason questions on pressure changes and through diagram-based questions on Fig. 14.2 — so link each muscle action firmly to the volume and pressure change it causes.
14.2.1 Respiratory Volumes and Capacities
The spirometer introduced in the previous section does more than confirm that we are breathing — it measures exactly how much air we move. These measurements fall into two groups. Respiratory volumes are the basic, directly measured amounts of air, and pulmonary capacities are larger quantities obtained by adding two or more volumes together. Capacities are especially useful in clinical diagnosis, since a fall in a person’s capacity can signal lung disease.
The Four Respiratory Volumes
The first volume is the ordinary breath. Tidal Volume (TV) is the volume of air breathed in or breathed out during a single normal, quiet breath — about 500 mL. Multiply this by a normal breathing rate and you can see how much air a person moves each minute: a healthy adult inspires or expires roughly 6000 to 8000 mL of air per minute.
Beyond a normal breath, we can always breathe in more if we try. Inspiratory Reserve Volume (IRV) is the extra air a person can force in over and above a normal inspiration — averaging 2500 mL to 3000 mL.
Similarly, after a normal breath out, we can still squeeze more air out. Expiratory Reserve Volume (ERV) is the extra air a person can force out beyond a normal expiration — averaging 1000 mL to 1100 mL.
Even after the hardest possible breath out, the lungs never empty completely. Residual Volume (RV) is the air that always remains behind — averaging 1100 mL to 1200 mL. This leftover air keeps the alveoli from collapsing and allows gas exchange to continue even between breaths.
Pulmonary Capacities
A capacity is simply two or more of these volumes added together. Because the lung’s volumes overlap in useful ways, these sums describe breathing situations that doctors care about.
The Inspiratory Capacity (IC) is the total air a person can breathe in starting from the end of a normal expiration — that is, a normal breath plus the reserve on top of it: \[IC = TV + IRV\]
The Expiratory Capacity (EC) is the total air a person can breathe out starting from the end of a normal inspiration: \[EC = TV + ERV\]
The Functional Residual Capacity (FRC) is the air still left in the lungs after a normal (not forced) expiration — the reserve you could still push out, plus the residual air you never can: \[FRC = ERV + RV\]
The Vital Capacity (VC) is one of the most important clinical measures — the maximum air a person can move in one huge breath. It is the maximum volume a person can breathe in after a forced expiration (or, equivalently, the maximum they can breathe out after a forced inspiration): \[VC = ERV + TV + IRV\]
Finally, the Total Lung Capacity (TLC) is everything the lungs can hold at the peak of a forced inspiration — the vital capacity plus the air that can never be expelled: \[TLC = RV + ERV + TV + IRV = VC + RV\]
All of these can be read off a single tracing produced by a spirometer, called a spirogram, shown in Fig. 14.3.
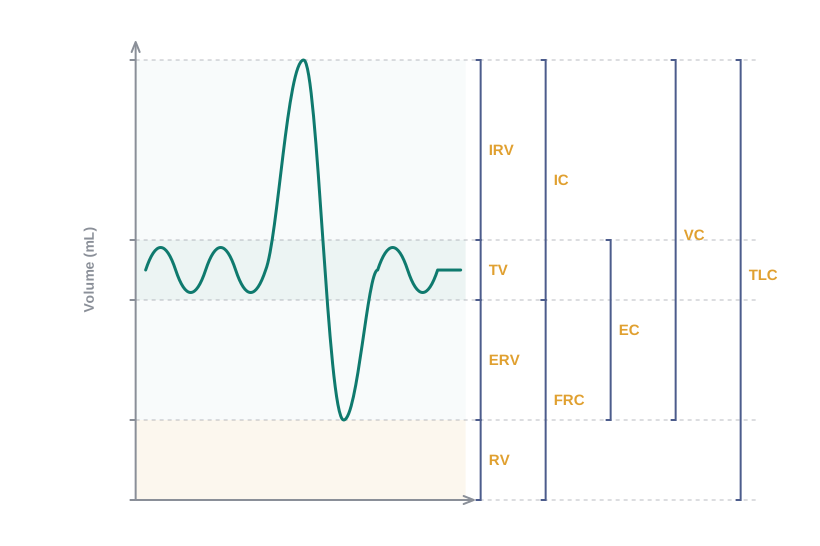
Fig. 14.3 – Spirogram showing respiratory volumes and capacities.
In exams, this subsection is tested heavily through numerical problems (adding volumes to find a capacity) and through match-the-following and assertion–reason items on the definitions — so keep the formulas and the spirogram picture firmly linked in your mind.
14.3 Exchange of Gases
The air we have worked so hard to pull into the lungs is only useful if the oxygen in it can actually cross into the blood. This crossing — the exchange of gases — happens at two places in the body. The alveoli are the primary sites, where gases pass between the air and the blood. A second exchange happens between the blood and the body tissues, where oxygen is finally handed over to the cells and their \(CO_2\) is collected. As shown in Fig. 14.4, these two exchanges are linked by the blood that shuttles between them.
Fig. 14.4 – Gas exchange and transport in the body.
What Drives the Exchange
Both exchanges happen by diffusion — the passive movement of a gas from where its pressure is higher to where it is lower. No energy is spent; the gases simply move down their pressure gradients.
Three factors decide how fast this diffusion occurs: the pressure (or concentration) gradient of the gas, the solubility of the gas, and the thickness of the membrane the gas must cross. A steeper gradient, a more soluble gas, and a thinner membrane all speed up diffusion. As we will see, the human body is beautifully set up so that all three factors favour rapid gas exchange.
Partial Pressure — the Key Idea
Air is a mixture of gases, and each gas in the mixture pushes with its own share of the total pressure. The pressure contributed by one individual gas in a mixture is called its partial pressure. Oxygen’s partial pressure is written as \(pO_2\) and carbon dioxide’s as \(pCO_2\).
Partial pressure is what actually drives diffusion: a gas moves from where its partial pressure is high to where it is low. Table 14.1 lists the partial pressures (in mm Hg) of \(O_2\) and \(CO_2\) in the atmosphere and at the two sites of diffusion.
| Respiratory Gas | Atmospheric Air | Alveoli | Blood (Deoxygenated) | Blood (Oxygenated) | Tissues |
|---|---|---|---|---|---|
| \(O_2\) | 159 | 104 | 40 | 95 | 40 |
| \(CO_2\) | 0.3 | 40 | 45 | 40 | 45 |
(Read across each row and watch the numbers fall in the direction the gas travels. For \(O_2\): it is 104 in the alveoli but only 40 in the deoxygenated blood arriving there — so oxygen diffuses into the blood. That blood, now oxygenated at 95, meets tissues at only 40 — so oxygen diffuses out into the tissues. For \(CO_2\) the numbers run the other way: 45 in the tissues versus 40 in the arriving blood pushes \(CO_2\) into the blood, and 45 in the blood versus 40 in the alveoli pushes \(CO_2\) out into the alveoli. Each gas simply slides down its own gradient.)
So there is a concentration gradient for oxygen running from alveoli → blood → tissues, and an opposite gradient for carbon dioxide running from tissues → blood → alveoli. The blood ferries each gas from where it is picked up to where it is released.
Why CO2 Keeps Up Despite a Smaller Gradient
Look again at Table 14.1 and something puzzling appears. Oxygen has a large gradient to work with (104 down to 40 at the alveoli), but carbon dioxide has only a tiny one (45 down to 40). How does \(CO_2\) still leave the blood fast enough?
The Diffusion Membrane
For gases to move between alveolar air and blood, they must cross the diffusion membrane — the barrier separating the two. As shown in Fig. 14.5, this membrane is built from three major layers: the thin squamous epithelium of the alveoli (a single sheet of flat cells), the endothelium of the alveolar capillaries (the flat cells lining the tiny blood vessels), and a basement substance sandwiched in between (a thin basement membrane supporting the alveolar epithelium together with the basement membrane wrapping the single-layered capillary cells).
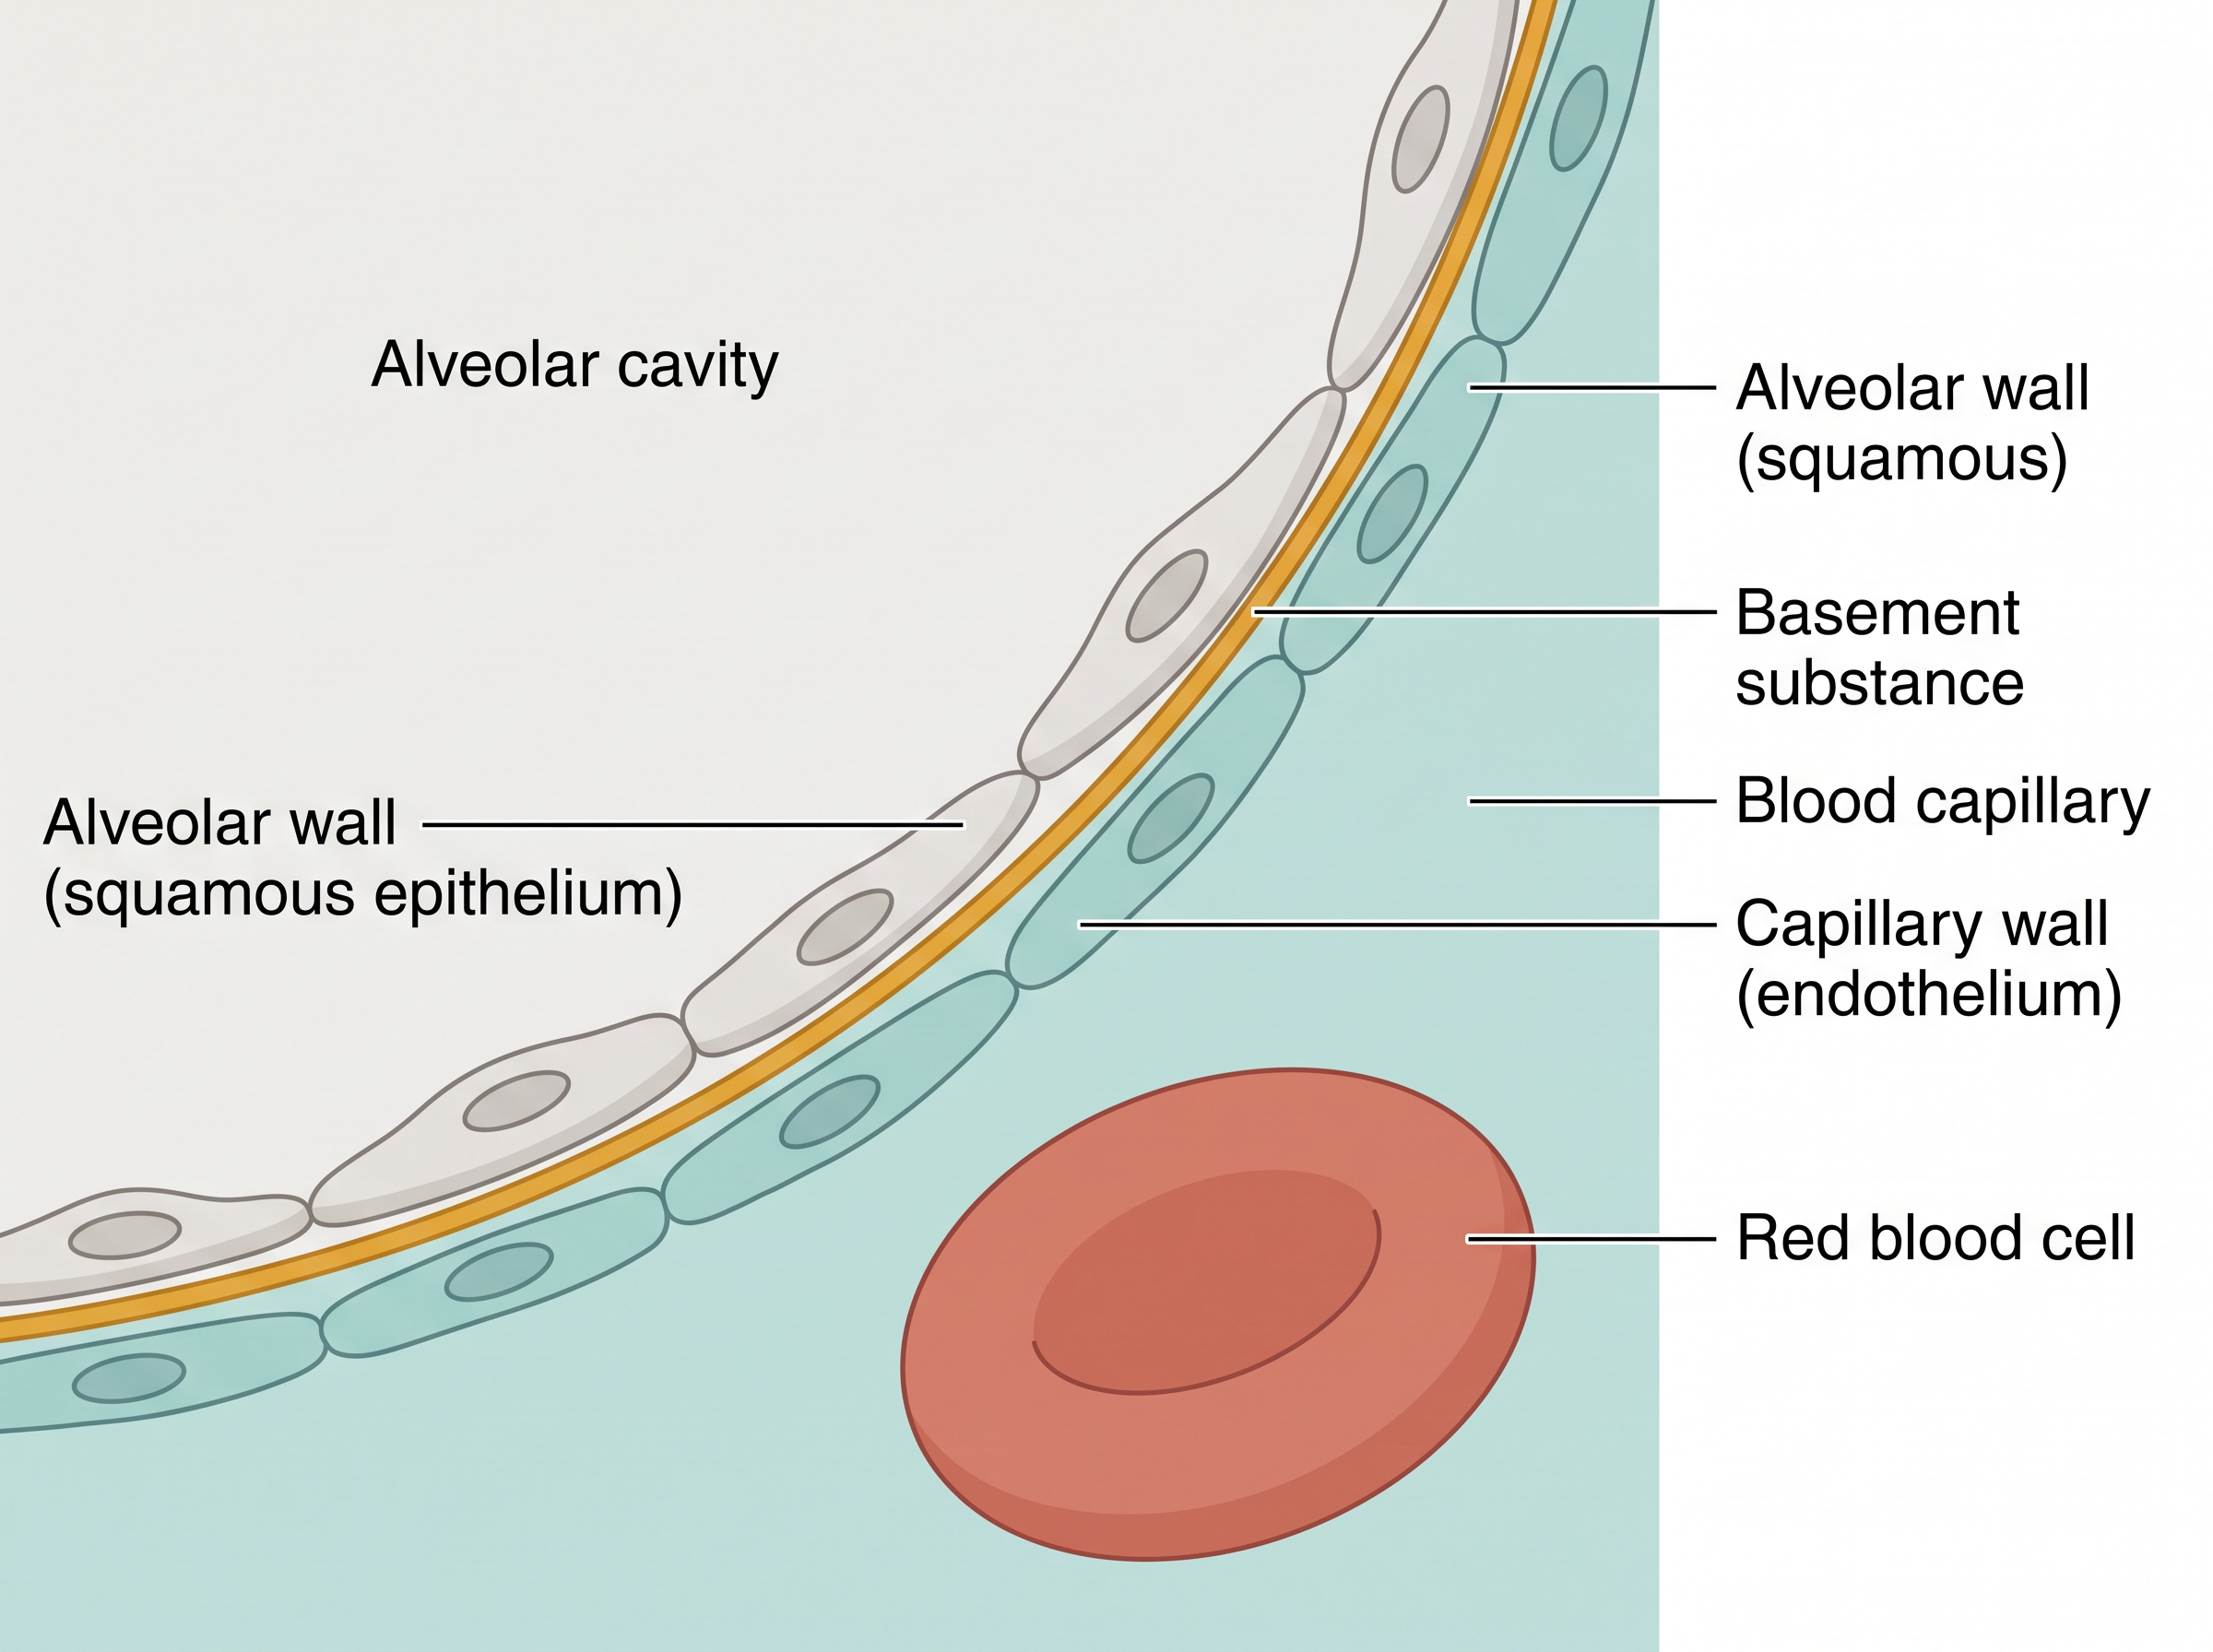
Fig. 14.5 – The three-layered diffusion membrane.
Although it has three layers, the entire diffusion membrane is astonishingly thin — its total thickness is much less than a millimetre. That thinness is the whole point.
Putting all of this together — a steep gradient for oxygen, high solubility for carbon dioxide, and a membrane thinner than a millimetre — every factor in our body favours the diffusion of \(O_2\) from the alveoli towards the tissues, and of \(CO_2\) from the tissues towards the alveoli.
For exams, this section is commonly tested through data-reading questions on Table 14.1, assertion–reason items on the solubility of \(CO_2\), and diagram-labelling of the three-layered diffusion membrane in Fig. 14.5.
14.4 Transport of Gases
Once gases have diffused into the blood, they must be carried to their destinations — oxygen from the lungs to the tissues, and carbon dioxide from the tissues back to the lungs. Blood is the medium of transport for both. Blood has a fluid part called plasma and cells suspended in it, the most numerous being the red blood cells (RBCs), which do most of the carrying work.
Oxygen is transported in two forms. About 97 per cent of \(O_2\) is carried by the RBCs in the blood, while the remaining 3 per cent travels dissolved in the plasma. So only a tiny fraction relies on simple dissolving — the bulk is ferried by the red cells, as the next subsection explains.
Carbon dioxide is transported in three forms. Nearly 20–25 per cent of \(CO_2\) is carried by the RBCs, about 70 per cent is carried as bicarbonate (in the plasma), and roughly 7 per cent is carried dissolved in the plasma. The detailed chemistry of these forms is covered in the subsection on the transport of carbon dioxide.
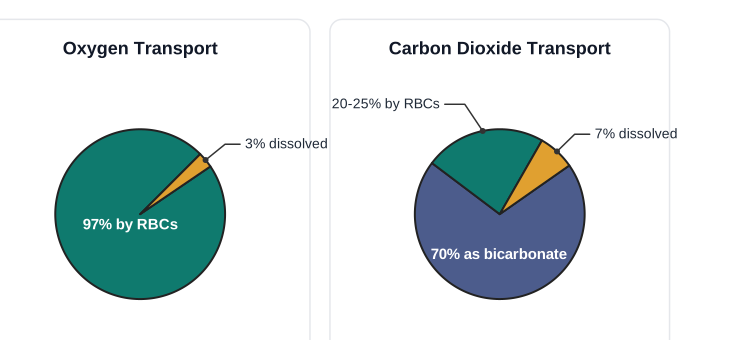
Fig. 14.6 – Transport forms of respiratory gases.
In exams, these figures are frequently tested directly — for example, “what percentage of \(CO_2\) is transported as bicarbonate?” — so commit the exact numbers to memory.
14.4.1 Transport of Oxygen
Haemoglobin, the Oxygen Carrier
The reason blood can carry so much oxygen despite oxygen’s poor solubility is a remarkable molecule: haemoglobin. It is a red-coloured, iron-containing pigment packed inside the red blood cells — and the iron in it is what actually grips oxygen.
Oxygen binds to haemoglobin in a reversible manner, forming oxyhaemoglobin. “Reversible” is the key word: the same haemoglobin that picks up oxygen in the lungs can let it go again in the tissues. Each haemoglobin molecule can hold a maximum of four molecules of \(O_2\) at once.
What Controls Loading and Unloading
Whether haemoglobin loads oxygen or releases it depends mainly on the partial pressure of oxygen (\(pO_2\)). Three other factors also influence the binding: the partial pressure of carbon dioxide (\(pCO_2\)), the hydrogen ion (\(H^+\)) concentration, and the temperature.
These factors line up perfectly at the two places that matter. In the alveoli there is high \(pO_2\), low \(pCO_2\), lower \(H^+\) concentration and lower temperature — all favouring the formation of oxyhaemoglobin, so oxygen loads onto haemoglobin. In the tissues the opposite conditions exist — low \(pO_2\), high \(pCO_2\), high \(H^+\) concentration and higher temperature — all favouring the dissociation of oxygen from oxyhaemoglobin, so oxygen is released.
The result is exactly what the body needs: oxygen gets bound to haemoglobin at the lung surface and gets unloaded at the tissues, entirely automatically.
The Oxygen Dissociation Curve
If we plot the percentage saturation of haemoglobin with oxygen against the \(pO_2\), we do not get a straight line — we get an S-shaped, or sigmoid, curve. This is the Oxygen dissociation curve, shown in Fig. 14.7, and it is a powerful tool for studying how factors such as \(pCO_2\) and \(H^+\) concentration affect oxygen binding.
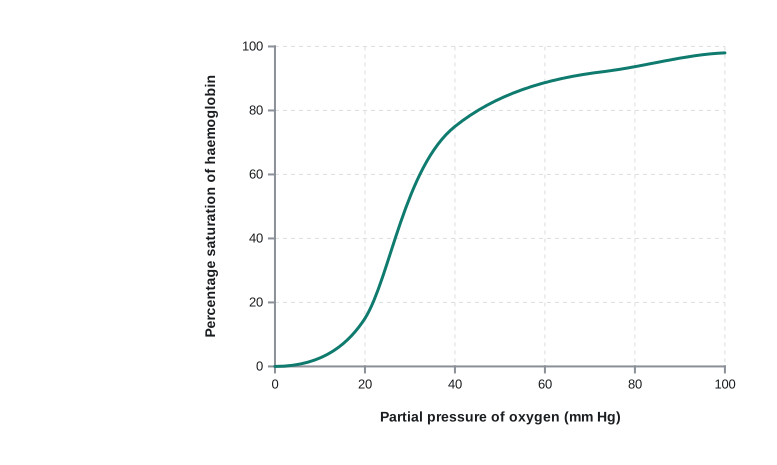
Fig. 14.7 – The oxygen dissociation curve.
Under normal physiological conditions, this efficient loading and unloading means that every 100 mL of oxygenated blood delivers about 5 mL of \(O_2\) to the tissues.
For exams, expect to define the oxygen dissociation curve and explain its sigmoid shape (Exercise question), to interpret shifts in the curve caused by \(pCO_2\), \(H^+\) and temperature, and to answer assertion–reason items on why oxygen loads in the lungs but unloads in the tissues.
14.4.2 Transport of Carbon dioxide
Carbon dioxide produced by the tissues must be carried back to the lungs and removed. As we saw in the overview, it travels in three forms — a small amount dissolved in plasma, some bound to haemoglobin, and the bulk as bicarbonate. This subsection looks at the two important carrier mechanisms in detail.
Carbon Dioxide Carried on Haemoglobin
Haemoglobin does not carry only oxygen. About 20–25 per cent of carbon dioxide is carried by haemoglobin as carbamino-haemoglobin. This binding is controlled by the partial pressure of \(CO_2\) (\(pCO_2\)), with the partial pressure of oxygen (\(pO_2\)) acting as a major influencing factor.
The conditions again suit the body’s needs perfectly. In the tissues, where \(pCO_2\) is high and \(pO_2\) is low, more \(CO_2\) binds to haemoglobin. In the alveoli, where \(pCO_2\) is low and \(pO_2\) is high, the reverse happens — \(CO_2\) dissociates from carbamino-haemoglobin. So the very \(CO_2\) picked up from the tissues is delivered at the alveoli to be breathed out.
Carbon Dioxide Carried as Bicarbonate
The largest share of \(CO_2\) (about 70%) is carried as bicarbonate ions (\(HCO_3^-\)). This depends on an enzyme — a biological catalyst that speeds up a reaction — called carbonic anhydrase. Red blood cells contain a very high concentration of carbonic anhydrase, with only minute quantities present in the plasma.
This enzyme speeds up the following reaction, and importantly it works in both directions:
\[CO_2 + H_2O \;\underset{\text{carbonic anhydrase}}{\rightleftharpoons}\; H_2CO_3 \;\underset{\text{carbonic anhydrase}}{\rightleftharpoons}\; HCO_3^- + H^+\]
Here \(CO_2\) is carbon dioxide, \(H_2O\) is water, \(H_2CO_3\) is carbonic acid, \(HCO_3^-\) is the bicarbonate ion, and \(H^+\) is a hydrogen ion.
At the tissue site, where \(pCO_2\) is high because of catabolism (the energy-releasing breakdown of food), \(CO_2\) diffuses into the blood — into both the RBCs and the plasma — and the reaction runs forward, forming \(HCO_3^-\) and \(H^+\). At the alveolar site, where \(pCO_2\) is low, the same reaction runs backward, reforming \(CO_2\) and \(H_2O\). In this way the \(CO_2\) that was trapped as bicarbonate at the tissues and carried through the blood is finally released as \(CO_2\) at the alveoli and breathed out (Fig. 14.5).
Flowchart
FC 14.5 – Bicarbonate transport of \(CO_2\): at tissues (high \(pCO_2\)) \(CO_2\) diffuses into blood → carbonic anhydrase → \(H_2CO_3\) → \(HCO_3^- + H^+\) (bicarbonate carried in blood to lungs) → at alveoli (low \(pCO_2\)) reaction reverses → \(H_2CO_3\) → \(CO_2 + H_2O\) → \(CO_2\) exhaled.
Under normal physiological conditions, every 100 mL of deoxygenated blood delivers approximately 4 mL of \(CO_2\) to the alveoli.
For exams, this subsection is tested through the carbonic anhydrase reaction (write it and state its direction at tissues vs alveoli), the exact transport percentages, and assertion–reason questions distinguishing carbamino-haemoglobin from bicarbonate transport.
14.5 Regulation of Respiration
Your breathing rate is not fixed. When you sleep it slows; when you climb stairs it speeds up. Human beings have a remarkable ability to maintain a steady breathing rhythm and yet adjust it moment to moment to suit the changing demands of the body tissues. This fine control is managed by the neural system (the nervous system) — which is why you keep breathing all night without ever having to think about it.
The Control Centres in the Brain
The master control lies in the medulla region of the brain, in a specialised centre called the respiratory rhythm centre. This centre is primarily responsible for generating and maintaining the basic rhythm of breathing.
A second centre, the pneumotaxic centre, sits in the pons region of the brain. It does not create the rhythm; instead it moderates the rhythm centre’s activity. Neural signals from the pneumotaxic centre can shorten the duration of inspiration, and by doing so, alter the respiratory rate — for example, making breaths quicker and shallower when needed.
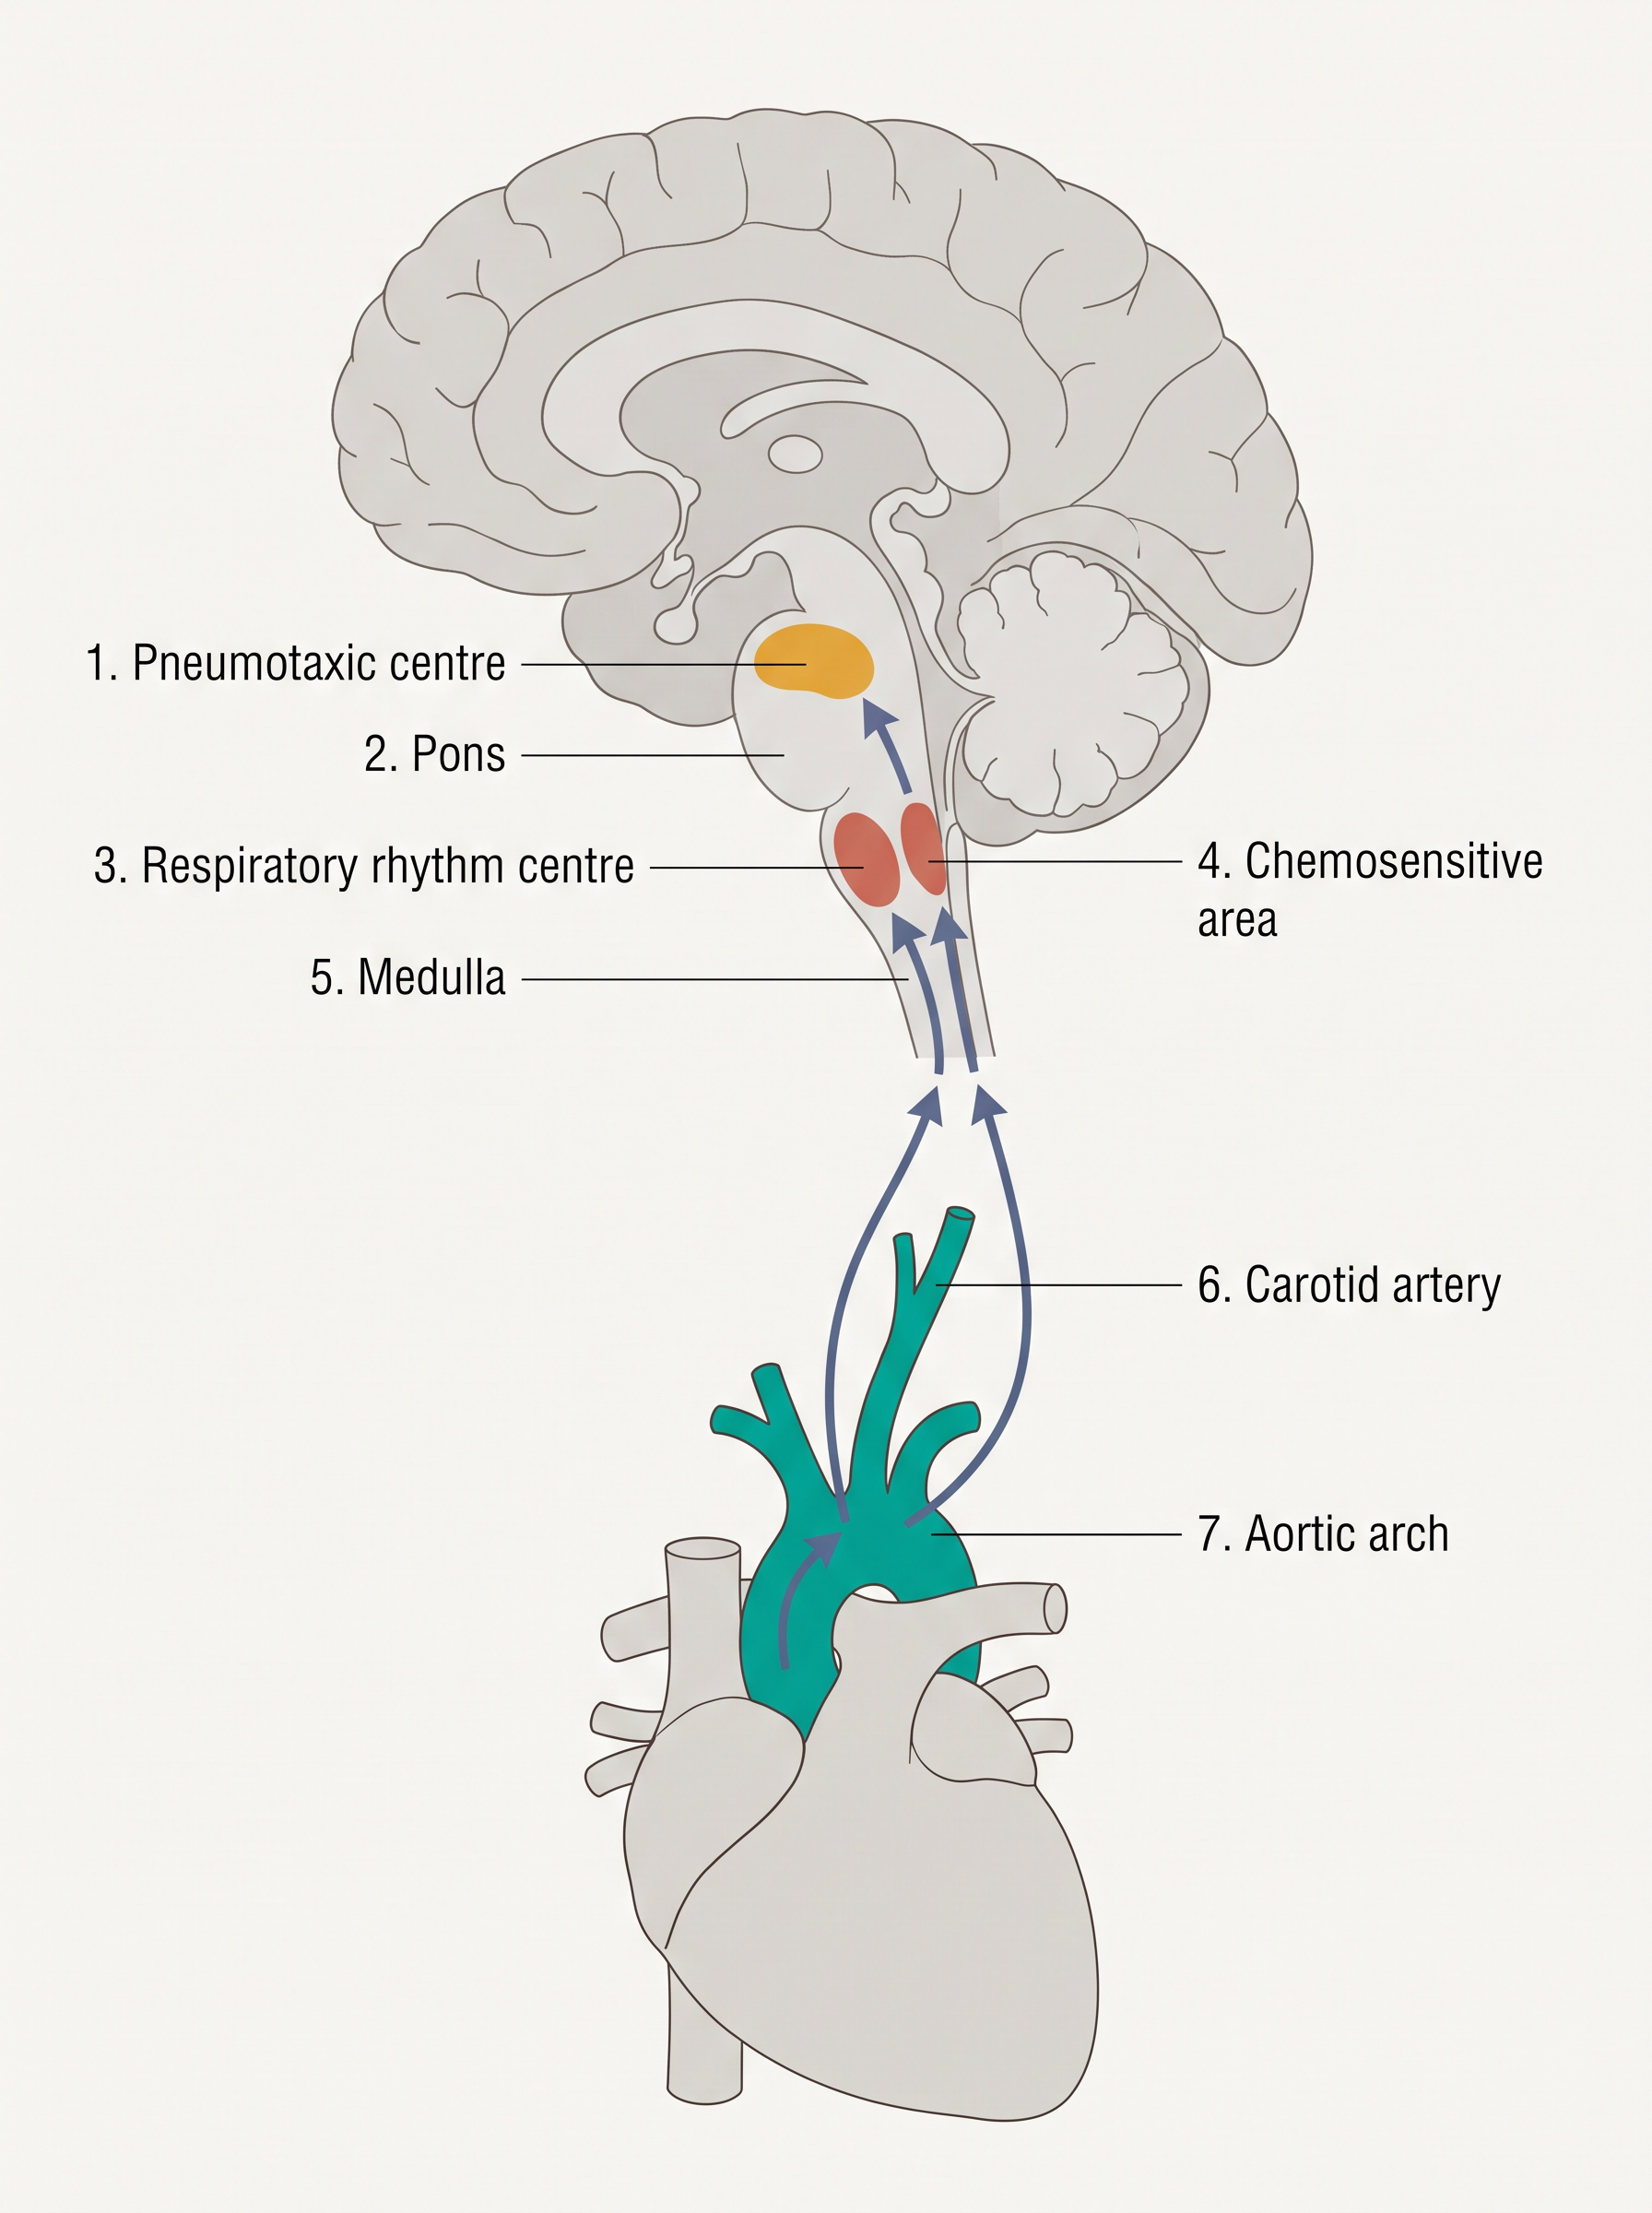
Fig. 14.8 – Neural control of respiration.
Sensing Carbon Dioxide
How does the brain know when to change your breathing? The answer is that it constantly monitors the blood chemistry, not the oxygen level.
Right next to the rhythm centre lies a chemosensitive area that is highly sensitive to carbon dioxide and hydrogen ions (\(H^+\)). When these substances rise in the blood, this area is activated and signals the rhythm centre to make the necessary adjustments — usually by increasing breathing — so that the excess \(CO_2\) and \(H^+\) can be eliminated.
Backing this up, special receptors associated with the aortic arch (the great curve of the aorta leaving the heart) and the carotid artery (in the neck) can also detect changes in \(CO_2\) and \(H^+\) concentration. They too send signals to the rhythm centre so that corrective action can be taken.
Notice what is missing from all of this: oxygen. The role of oxygen in the regulation of respiratory rhythm is quite insignificant. It is the build-up of carbon dioxide, not the shortage of oxygen, that mainly tells the body to breathe.
Flowchart
FC 14.6 – The respiratory feedback loop: \(CO_2\) / \(H^+\) rise in blood → chemosensitive area (medulla) and aortic/carotid receptors activated → signals sent to respiratory rhythm centre → breathing rate and depth increased → excess \(CO_2\) and \(H^+\) eliminated → blood levels return to normal → back to normal breathing.
For exams, this section is tested through the locations and roles of the three centres, assertion–reason items on \(CO_2\) (not \(O_2\)) driving respiration, and match-the-following linking each centre or receptor to its function.
14.6 Disorders of Respiratory System
Like any organ system, the respiratory system can fall ill or be damaged. A few important disorders show what happens when its structures — the airways, the alveoli, or the exchange surface — stop working normally.
Asthma
Asthma is a difficulty in breathing that produces a whistling sound called wheezing. It is caused by inflammation (swelling and irritation) of the bronchi and bronchioles, which narrows these airways and makes it harder for air to move through them.
Emphysema
Emphysema is a chronic (long-lasting) disorder in which the walls of the alveoli are damaged. Because it is the alveoli that provide the surface for gas exchange, destroying their walls decreases the respiratory surface available for diffusion. With less surface, less oxygen can be taken up, and the person becomes breathless. One of the major causes of emphysema is cigarette smoking.
Occupational Respiratory Disorders
Some lung diseases come from a person’s workplace. In certain industries — especially those involving grinding or stone-breaking — so much dust is produced that the body’s natural defence mechanisms (which normally trap and clear particles) cannot fully cope. Over long exposure, this leads to inflammation, and then to fibrosis — the proliferation (overgrowth) of fibrous tissue in the lungs — causing serious lung damage. To prevent this, workers in such industries should wear protective masks.
For exams, this section is tested through direct definitions and through match-the-following linking each disorder to the part of the respiratory system it affects and its cause.
14.7 Summary
Cells use oxygen for metabolism to release energy, producing harmful waste substances such as carbon dioxide. Animals have evolved different mechanisms to supply \(O_2\) to their cells and to remove \(CO_2\). In humans this job is done by a well-developed respiratory system of two lungs and their associated air passages.
The first step in respiration is breathing: atmospheric air is taken in (inspiration) and alveolar air is released out (expiration). The remaining steps are the exchange of \(O_2\) and \(CO_2\) between the deoxygenated blood and the alveoli, the transport of these gases throughout the body by the blood, the exchange of \(O_2\) and \(CO_2\) between the oxygenated blood and the tissues, and the utilisation of \(O_2\) by the cells (cellular respiration).
Inspiration and expiration are brought about by creating pressure gradients between the atmosphere and the alveoli, using specialised muscles — the intercostals and the diaphragm. The volumes of air moved can be measured with a spirometer and are of clinical significance.
Exchange of \(O_2\) and \(CO_2\) at the alveoli and at the tissues occurs by diffusion. Its rate depends on the partial pressure gradients of \(O_2\) (\(pO_2\)) and \(CO_2\) (\(pCO_2\)), the solubility of the gases, and the thickness of the diffusion surface. In our body these factors favour the diffusion of \(O_2\) from the alveoli into the deoxygenated blood and from the oxygenated blood into the tissues, and favour the diffusion of \(CO_2\) in the opposite direction, from the tissues to the alveoli.
Oxygen is transported mainly as oxyhaemoglobin. In the alveoli, where \(pO_2\) is high, \(O_2\) binds to haemoglobin; this is easily released at the tissues, where \(pO_2\) is low and \(pCO_2\) and \(H^+\) concentration are high.
Nearly 70 per cent of carbon dioxide is transported as bicarbonate (\(HCO_3^-\)) with the help of the enzyme carbonic anhydrase, and about 20–25 per cent is carried by haemoglobin as carbamino-haemoglobin. In the tissues, where \(pCO_2\) is high, \(CO_2\) binds to the blood; in the alveoli, where \(pCO_2\) is low and \(pO_2\) is high, it is removed from the blood.
The respiratory rhythm is maintained by the respiratory rhythm centre in the medulla of the brain. A pneumotaxic centre in the pons and a chemosensitive area in the medulla can alter the respiratory mechanism.
Flowchart
FC 14.7 – The whole chapter in one line: inspiration (air in) → gas exchange at alveoli by diffusion (\(O_2\) in, \(CO_2\) out) → transport by blood (\(O_2\) as oxyhaemoglobin; \(CO_2\) mostly as bicarbonate) → gas exchange at tissues (\(O_2\) to cells, \(CO_2\) to blood) → cells use \(O_2\) (cellular respiration) → \(CO_2\) carried back → expiration (air out); the whole cycle regulated by the medulla and pons.
14.8 Points to Ponder
Your body decides how fast to breathe by monitoring carbon dioxide, not oxygen. What might go wrong if someone in a low-oxygen situation, such as high on a mountain, kept feeling “fine” simply because their \(CO_2\) levels were normal?
The diffusion membrane between air and blood is thinner than a millimetre. Such thinness makes gas exchange fast — but what risks might come with having so delicate a barrier separating the outside air from your bloodstream?
Emphysema slowly destroys the walls of the alveoli and shrinks the exchange surface. Why might a long-time smoker feel perfectly healthy for years, and only later become breathless, even though the damage began much earlier?
You cannot squeeze your lungs directly, yet you can hold your breath whenever you choose. How do you think the automatic control of breathing and your voluntary control of it manage to share command of the same muscles?
Carbon dioxide has only a tiny partial-pressure gradient across the alveoli, yet it is removed from the blood very efficiently. What does this tell you about how a living system can make up for a weak gradient in one property by relying on another?
The oxygen dissociation curve is S-shaped rather than a straight line. Why might a system that responds cooperatively — reluctant at first, then eager — deliver oxygen to the tissues more usefully than one that responds in simple proportion?
Insects deliver air directly to their tissues through tiny tubes instead of using blood the way we do. Could the design of this breathing system be one reason we never see insects the size of dogs? What would have to change for a giant insect to breathe?
14.9 NCERT Questions
Define vital capacity. What is its significance?
State the volume of air remaining in the lungs after a normal breathing.
Diffusion of gases occurs in the alveolar region only and not in the other parts of the respiratory system. Why?
What are the major transport mechanisms for \(CO_2\)? Explain.
What will be the \(pO_2\) and \(pCO_2\) in the atmospheric air compared to those in the alveolar air?
- \(pO_2\) lesser, \(pCO_2\) higher
- \(pO_2\) higher, \(pCO_2\) lesser
- \(pO_2\) higher, \(pCO_2\) higher
- \(pO_2\) lesser, \(pCO_2\) lesser
Explain the process of inspiration under normal conditions.
How is respiration regulated?
What is the effect of \(pCO_2\) on oxygen transport?
What happens to the respiratory process in a man going up a hill?
What is the site of gaseous exchange in an insect?
Define oxygen dissociation curve. Can you suggest any reason for its sigmoidal pattern?
Distinguish between
- IRV and ERV
- Inspiratory capacity and Expiratory capacity
- Vital capacity and Total lung capacity
What is Tidal volume? Find out the Tidal volume (approximate value) for a healthy human in an hour.
14.10 Check Your Concepts
Assertion–Reason. Assertion: During inspiration, the diaphragm contracts and flattens. Reason: Contraction of the diaphragm decreases the volume of the thoracic cavity. State whether the assertion and reason are true, and whether the reason correctly explains the assertion.
Why are the cartilaginous rings that support the trachea incomplete (C-shaped) rather than complete circles?
Arrange the following in the correct sequence through which inhaled air passes: alveoli, trachea, terminal bronchioles, pharynx, primary bronchi, bronchioles.
Draw a labelled diagram of the three-layered diffusion membrane at an alveolus, and explain how its structure suits rapid gas exchange.
Match each item in Column I with its correct description in Column II.
| Column I | Column II |
|---|---|
| a. Respiratory rhythm centre | i. Pons; moderates the rhythm centre |
| b. Pneumotaxic centre | ii. Enzyme catalysing \(CO_2\)–bicarbonate conversion |
| c. Chemosensitive area | iii. Medulla; generates the basic breathing rhythm |
| d. Carbonic anhydrase | iv. Sensitive to \(CO_2\) and \(H^+\) ions |
Even though carbon dioxide has a much smaller partial-pressure gradient than oxygen at the exchange surfaces, it still diffuses out efficiently. Explain why.
Assertion–Reason. Assertion: The role of oxygen in regulating the respiratory rhythm is insignificant. Reason: The chemosensitive area of the brain is highly sensitive to \(CO_2\) and hydrogen ions. Evaluate both statements and their relationship.
Differentiate between oxyhaemoglobin and carbamino-haemoglobin with respect to the gas carried, the site of loading, and the site of unloading.
Distinguish between the conducting part and the respiratory (exchange) part of the human respiratory system.
What would happen to gas exchange if the diffusion membrane became abnormally thickened, as occurs in pulmonary fibrosis? Explain your reasoning.
Explain how the structure of the alveoli makes them well suited for the exchange of gases.
Identify the odd one out and justify your choice: (a) Asthma, (b) Emphysema, (c) Oxyhaemoglobin, (d) Occupational fibrosis.
During quiet breathing, inspiration is described as an active process while expiration is largely passive. Explain the difference in terms of muscle activity.
Using the idea of partial pressures, explain why a person breathes faster and more deeply during vigorous exercise.
List the conditions present in the tissues that favour the dissociation of oxygen from oxyhaemoglobin, and explain why these conditions arise there.
14.11 Practice With Numericals
A healthy person has the following respiratory volumes: TV = 500 mL, IRV = 3000 mL, ERV = 1100 mL and RV = 1200 mL. Calculate (i) Inspiratory Capacity, (ii) Expiratory Capacity, (iii) Functional Residual Capacity, (iv) Vital Capacity and (v) Total Lung Capacity.
If a person’s tidal volume is 500 mL and the breathing rate is 15 breaths per minute, calculate the volume of air moved in and out of the lungs in one minute.
Using the partial-pressure values in Table 14.1, calculate the \(pO_2\) gradient (i) between the alveoli and the deoxygenated blood, and (ii) between the oxygenated blood and the tissues.
Using the partial-pressure values in Table 14.1, calculate the \(pCO_2\) gradient (i) between the tissues and the blood, and (ii) between the blood and the alveoli.
If every 100 mL of oxygenated blood delivers about 5 mL of oxygen to the tissues, how much oxygen is delivered by 5000 mL of oxygenated blood under the same conditions?
If every 100 mL of deoxygenated blood delivers about 4 mL of carbon dioxide to the alveoli, how much carbon dioxide is delivered by 4500 mL of deoxygenated blood?
A person’s vital capacity is measured as 4600 mL and residual volume as 1200 mL. Calculate the total lung capacity.