Chapter 19: Chemical Coordination and Integration
In the summer of 1921, in a small, hot laboratory at the University of Toronto, a young surgeon named Frederick Banting and a medical student named Charles Best set out to solve a deadly puzzle. For years, doctors had watched helplessly as patients with diabetes wasted away — endlessly thirsty, exhausted, and slowly starving even while they ate. Something inside the body was failing, but no one knew exactly what.
Banting and Best suspected the answer lay hidden in the pancreas. Working with dogs, they carefully extracted a substance from a cluster of cells buried deep inside the gland. When they injected this extract into a dog dying of diabetes, its dangerously high blood sugar began to fall. The mysterious substance was insulin.
In January 1922, a fourteen-year-old boy named Leonard Thompson, close to death from diabetes, became one of the first people to receive it. Within days he began to recover. A single chemical, produced by the body in astonishingly tiny amounts, had pulled him back from the edge.
That chemical was a hormone — one of the body’s silent messengers. This chapter is about those messengers: what they are, where they are made, and how such minute quantities can quietly control growth, energy, mood, and survival across the entire body.
Fig. 19.0 – The endocrine system and hormonal transport.
By the end of this chapter, you will be able to answer each of these questions.
19.1 Endocrine Glands and Hormones
Two Ways the Body Stays Coordinated
The many organs of the body cannot work in isolation; their activities must be matched to one another moment by moment. You have already studied one system that does this — the neural system, which carries electrical messages along nerve fibres. Neural coordination is like a direct telephone line: it is point-to-point and extremely fast, but its effect is short-lived, fading almost as soon as the signal stops.
This alone is not enough. Nerve fibres do not reach (innervate) every single cell of the body, yet the activities of all cells need to be regulated continuously, not just in quick bursts. The body therefore needs a second form of coordination — slower to begin, but longer-lasting. This job is carried out by hormones.
The neural system and the endocrine system (the hormone-producing system) do not compete. They work together, jointly coordinating and regulating the body’s physiological functions.
Ductless Glands and Their Secretions
Hormones are made by endocrine glands. The special feature of these glands is that they have no ducts (tubes) to carry their product away. For this reason they are called ductless glands. Instead of emptying into a duct, their secretions pass straight into the blood, which then transports them around the body. These secretions are the hormones.
This makes endocrine glands very different from exocrine glands (such as salivary or sweat glands), which do possess ducts and release their products onto a surface or into a cavity rather than into the blood.
What Exactly Is a Hormone?
The older, classical way of describing a hormone was: a chemical produced by an endocrine gland, released into the blood, and carried to a distantly located target organ where it acts. This description fits the familiar glands well. But scientists later found many other molecules in the body that behave like hormones without coming from an organised gland, so the definition had to be broadened.
Read this modern definition carefully, because every phrase matters. “Non-nutrient” means a hormone is not a food or fuel — it supplies no energy or building material; it only carries information. “Intercellular messenger” means it carries a signal from one cell to another. “Trace amounts” means the body needs only tiny quantities to produce a large effect.
This broader definition covers many new molecules, in addition to the hormones made by the well-organised endocrine glands. The pattern varies across the animal kingdom too: invertebrates possess very simple endocrine systems with only a few hormones, whereas in vertebrates a large number of chemicals act as hormones to provide coordination. In the sections that follow, it is the human endocrine system that we will study in detail.
19.2 Human Endocrine System
The endocrine system is not a single organ but a team. It is made up of all the endocrine glands together with the scattered (“diffused”) hormone-producing tissues and cells located in different parts of the body.
Some of these are well-organised, distinct endocrine glands. These are the pituitary, pineal, thyroid, adrenal, pancreas, parathyroid, thymus, and the gonads — the testis in males and the ovary in females. Their positions are shown in Fig. 19.1.
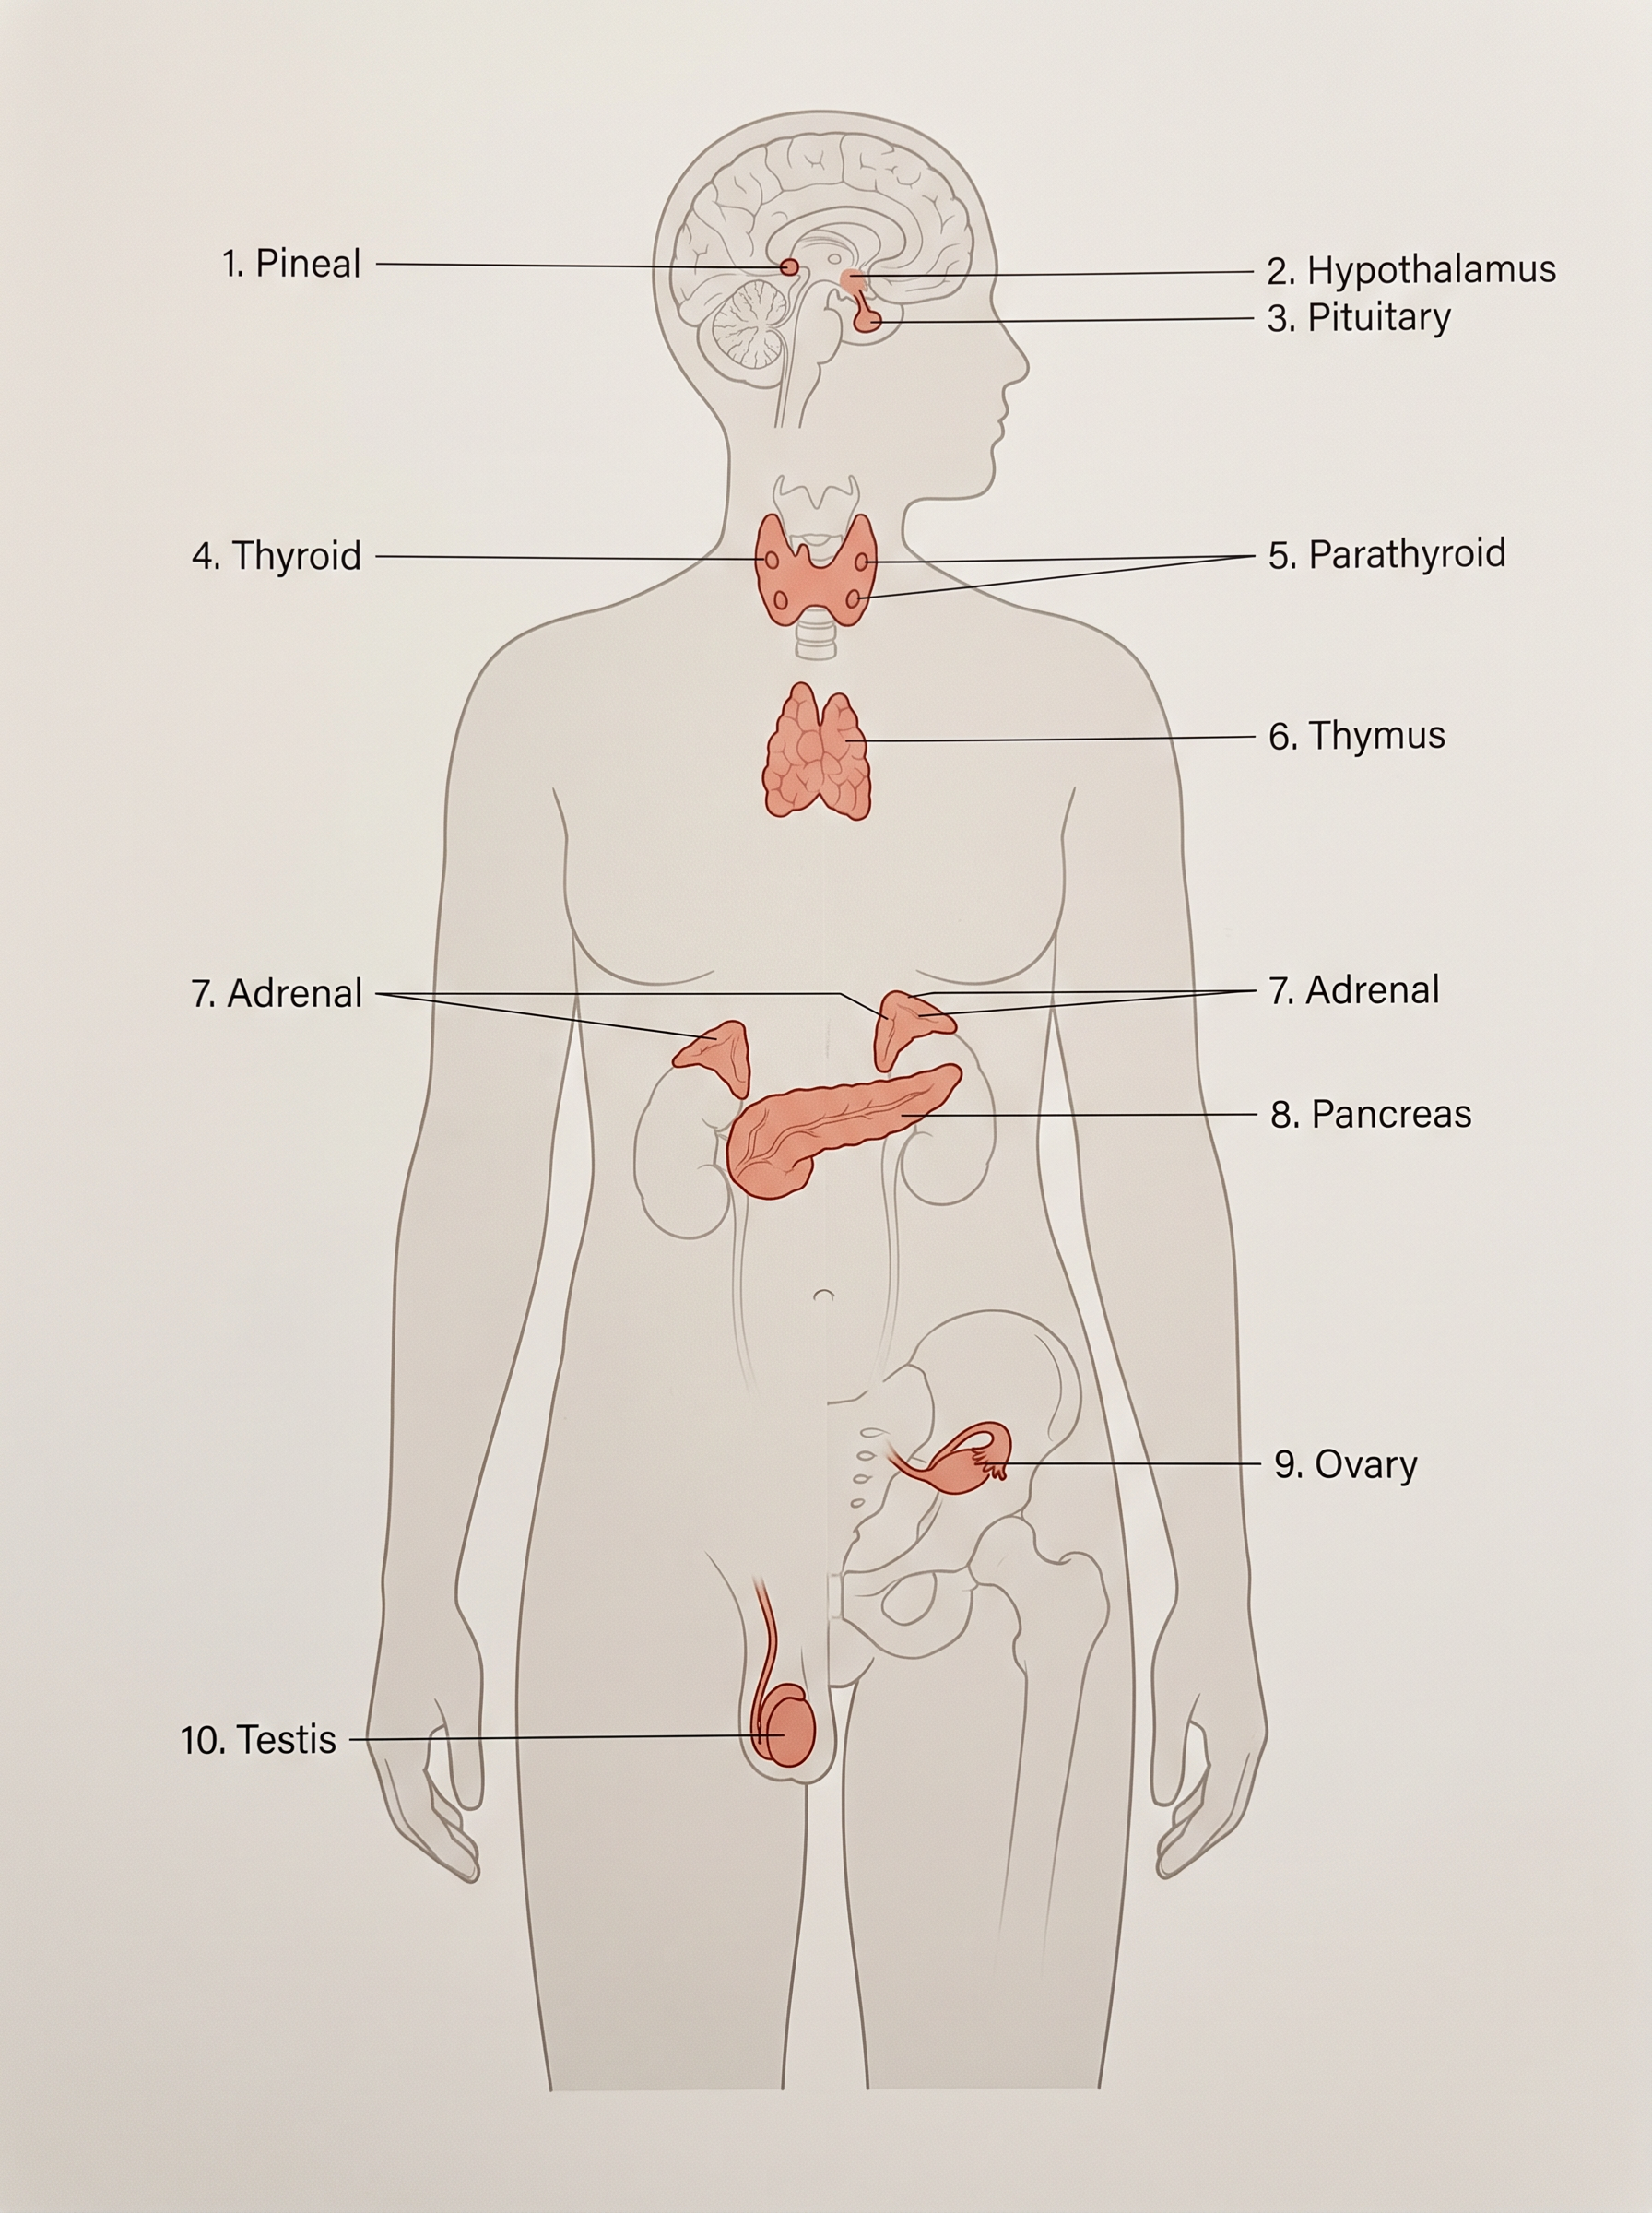
Fig. 19.1 – Location of endocrine glands in the human body.
Besides these organised glands, several other organs that have their own main jobs also secrete hormones on the side — for example, the gastrointestinal tract, liver, kidney, and heart.
The sections that follow give a brief account of the structure and functions of all the major endocrine glands, together with the hypothalamus, which we take up first.
19.2.1 The Hypothalamus
The hypothalamus is the basal (lowest) part of the diencephalon, a region of the forebrain (see Fig. 19.1). Though small, it acts as a master controller, regulating a wide spectrum of body functions — and, importantly for this chapter, the activity of the pituitary gland that hangs just below it.
Inside the hypothalamus lie several groups of special nerve cells called neurosecretory cells, gathered into clusters known as nuclei. These cells are unusual. Like all neurons they conduct nerve impulses, but they also behave like gland cells, producing hormones. In this way they form a living bridge between the nervous system and the endocrine system.
The hormones made by the hypothalamus have one main task: to regulate the synthesis and secretion of the pituitary’s own hormones. They come in two opposite types. Releasing hormones stimulate the pituitary to secrete a hormone, while inhibiting hormones do the reverse — they hold back, or inhibit, that secretion.
For example, the hypothalamic hormone gonadotrophin releasing hormone (GnRH) stimulates the pituitary to synthesise and release gonadotrophins (hormones that act on the gonads). In contrast, somatostatin from the hypothalamus inhibits the release of growth hormone from the pituitary.
How do these hormones actually reach the pituitary? They originate in the hypothalamic neurons, travel down the axons of those neurons, and are released from the nerve endings. From there they reach the pituitary gland through a special set of blood vessels called a portal circulatory system, and regulate the functions of the anterior pituitary. This control pathway is summarised in FC 19.1.
Flowchart
FC 19.1 – Hypothalamic control of the pituitary: hypothalamic neurosecretory cells → releasing / inhibiting hormones released at nerve endings → carried by the portal circulatory system → anterior pituitary → anterior pituitary hormones → target glands and tissues. Separate branch: hypothalamus → direct neural (nerve) control → posterior pituitary.
The posterior pituitary is handled differently. It is not controlled by portal blood but is under the direct neural regulation of the hypothalamus (Fig. 19.2) — a connection we will look at more closely in the next section.
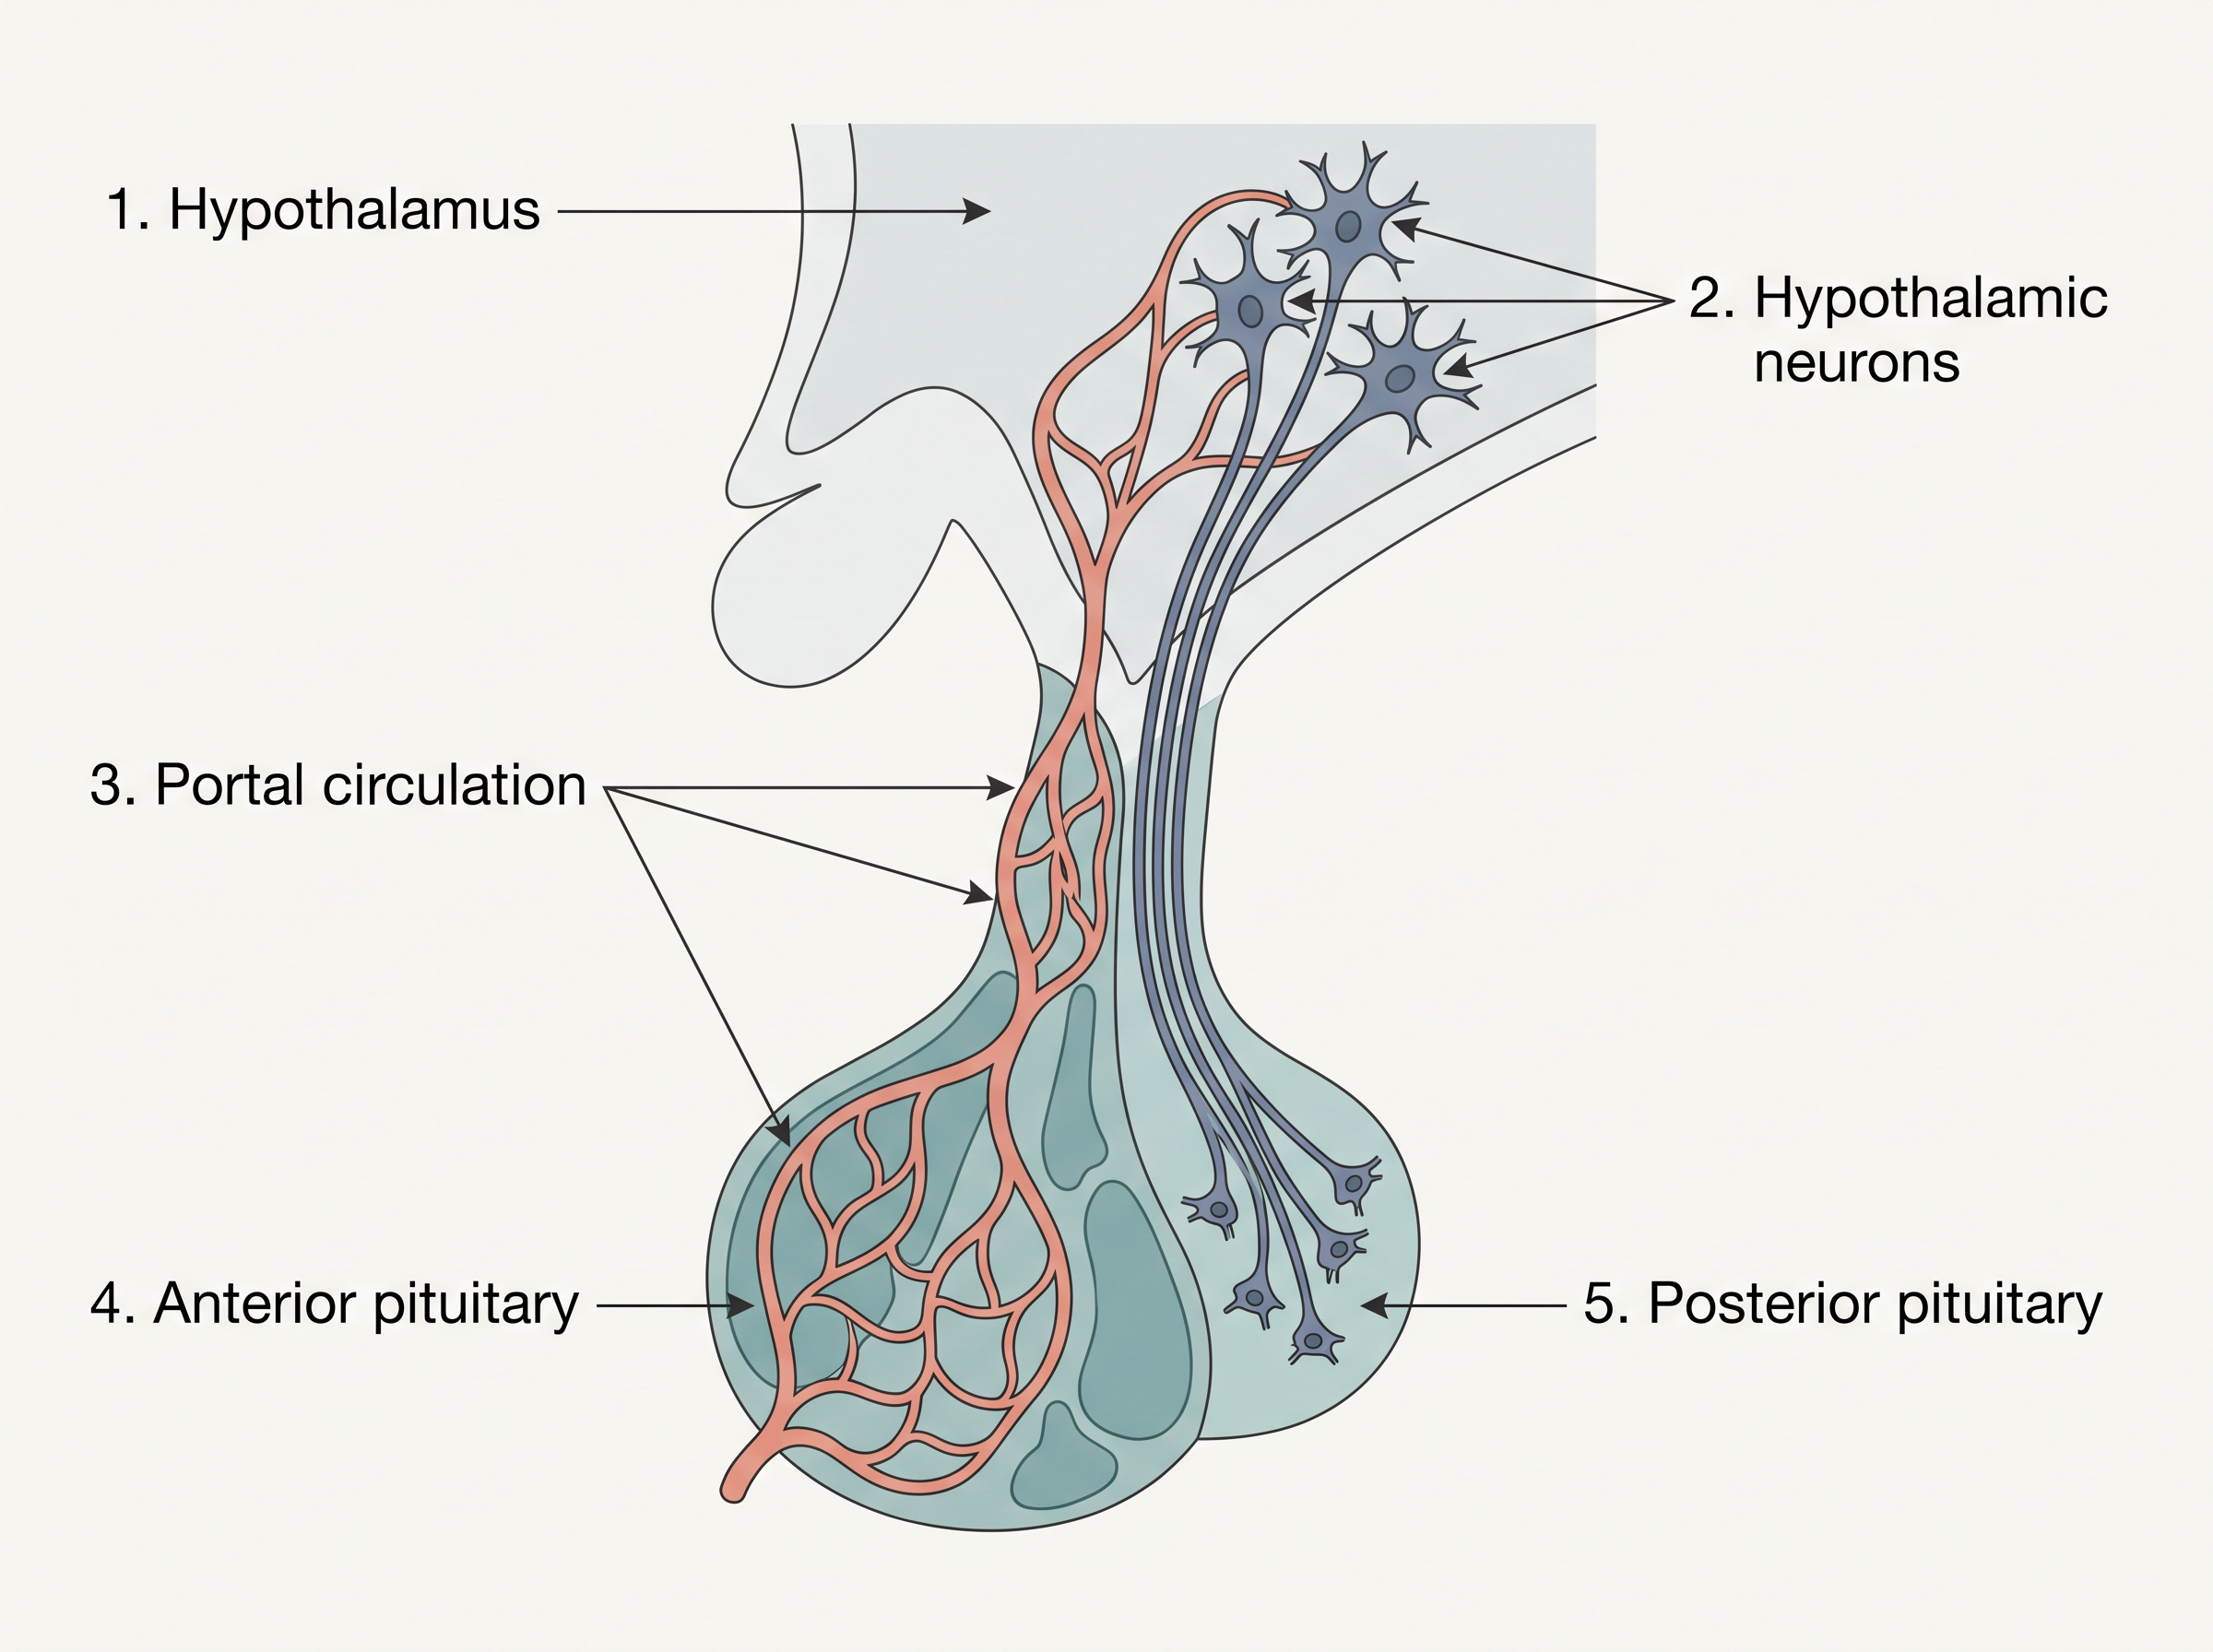
Fig. 19.2 – Hypothalamus and pituitary gland.
19.2.2 The Pituitary Gland
Structure and Divisions
The pituitary gland is a tiny gland that sits in a protective bony cavity of the skull called the sella tursica, and is joined to the hypothalamus above it by a short stalk (Fig. 19.2). Despite its small size, it controls the activity of several other endocrine glands, which is why it is often called the “master gland.”
Anatomically the pituitary is divided into two parts: the adenohypophysis and the neurohypophysis. The adenohypophysis itself has two portions — the pars distalis and the pars intermedia. The neurohypophysis is also called the pars nervosa. This organisation is summarised in FC 19.2.
Flowchart
FC 19.2 – Anatomical divisions of the pituitary gland: Pituitary → Adenohypophysis → (Pars distalis = anterior pituitary) and (Pars intermedia); Pituitary → Neurohypophysis (Pars nervosa) = posterior pituitary.
The pars distalis is commonly called the anterior pituitary. It is the busiest part, producing six important hormones: growth hormone (GH), prolactin (PRL), thyroid stimulating hormone (TSH), adrenocorticotrophic hormone (ACTH), luteinizing hormone (LH), and follicle stimulating hormone (FSH).
The pars intermedia secretes only one hormone, melanocyte stimulating hormone (MSH). In humans, however, the pars intermedia is almost completely merged with the pars distalis, so it is barely a separate region.
The neurohypophysis (pars nervosa), also known as the posterior pituitary, is different in a crucial way: it does not make its own hormones. Instead it stores and releases two hormones — oxytocin and vasopressin — which are actually synthesised by the hypothalamus and transported down axons (recall the neurosecretory cells from Section 19.2.1) to be stored here.
Actions of the Anterior Pituitary Hormones
Growth hormone controls the overall growth of the body, and both too much and too little of it cause clear disorders. Over-secretion of GH stimulates abnormal growth of the body, leading to gigantism, while low secretion of GH results in stunted growth, a condition called pituitary dwarfism.
If GH is over-secreted in adults, especially in middle age, the effect is different, because the long bones can no longer lengthen. Instead, the bones of the hands, feet, and face thicken, causing severe disfigurement (especially of the face) — a condition called acromegaly. Acromegaly may lead to serious complications, and premature death if unchecked. It is hard to diagnose in the early stages and often goes undetected for many years, until the changes in external features become noticeable.
Prolactin regulates the growth of the mammary glands and the formation of milk in them. TSH stimulates the synthesis and secretion of thyroid hormones from the thyroid gland. ACTH stimulates the synthesis and secretion of steroid hormones called glucocorticoids from the adrenal cortex (discussed in Section 19.2.7).
LH and FSH stimulate the activity of the gonads and are therefore together called gonadotrophins. Their actions differ between the sexes.
In males, LH stimulates the synthesis and secretion of hormones called androgens from the testis (Section 19.2.9), while FSH together with androgens regulates spermatogenesis (the formation of sperm).
In females, LH induces ovulation — the release of a fully mature follicle, called a graafian follicle — and then maintains the corpus luteum, the structure formed from the remnants of the graafian follicle after ovulation. FSH stimulates the growth and development of the ovarian follicles in females.
Actions of MSH and the Posterior Pituitary Hormones
MSH acts on the melanocytes, the melanin-containing cells of the skin, and regulates skin pigmentation.
Oxytocin acts on the smooth muscles of the body and stimulates their contraction. In females it produces two vital effects: it triggers a vigorous contraction of the uterus at the time of childbirth, and it causes milk ejection (the “let-down” of milk) from the mammary gland.
Vasopressin acts mainly on the kidney, where it stimulates the resorption (reabsorption) of water and electrolytes by the distal tubules. By pulling water back into the body, it reduces the loss of water through urine (diuresis). For this reason vasopressin is also called the anti-diuretic hormone (ADH).
If the synthesis or release of ADH is impaired, the kidney loses its ability to conserve water. Large amounts of water are then lost in the urine, leading to dehydration. This condition is called Diabetes Insipidus.
19.2.3 The Pineal Gland
The pineal gland is a small gland located on the dorsal (upper, back) side of the forebrain. It produces a single hormone called melatonin.
Melatonin is best thought of as the body’s timekeeper. It plays a very important role in regulating the 24-hour, or diurnal, rhythm of the body — the daily cycle of activity and rest often called the “biological clock.” For example, melatonin helps maintain the normal rhythms of the sleep-wake cycle and of body temperature across day and night.
Its influence does not stop there. Melatonin also affects metabolism, skin pigmentation, the menstrual cycle, and even our defence (immune) capability.
19.2.4 Thyroid Gland
Structure of the Thyroid
The thyroid gland is composed of two lobes, one on either side of the trachea (windpipe), as shown in Fig. 19.3(a). The two lobes are joined across the front by a thin flap of connective tissue called the isthmus, giving the whole gland a shape rather like a butterfly.
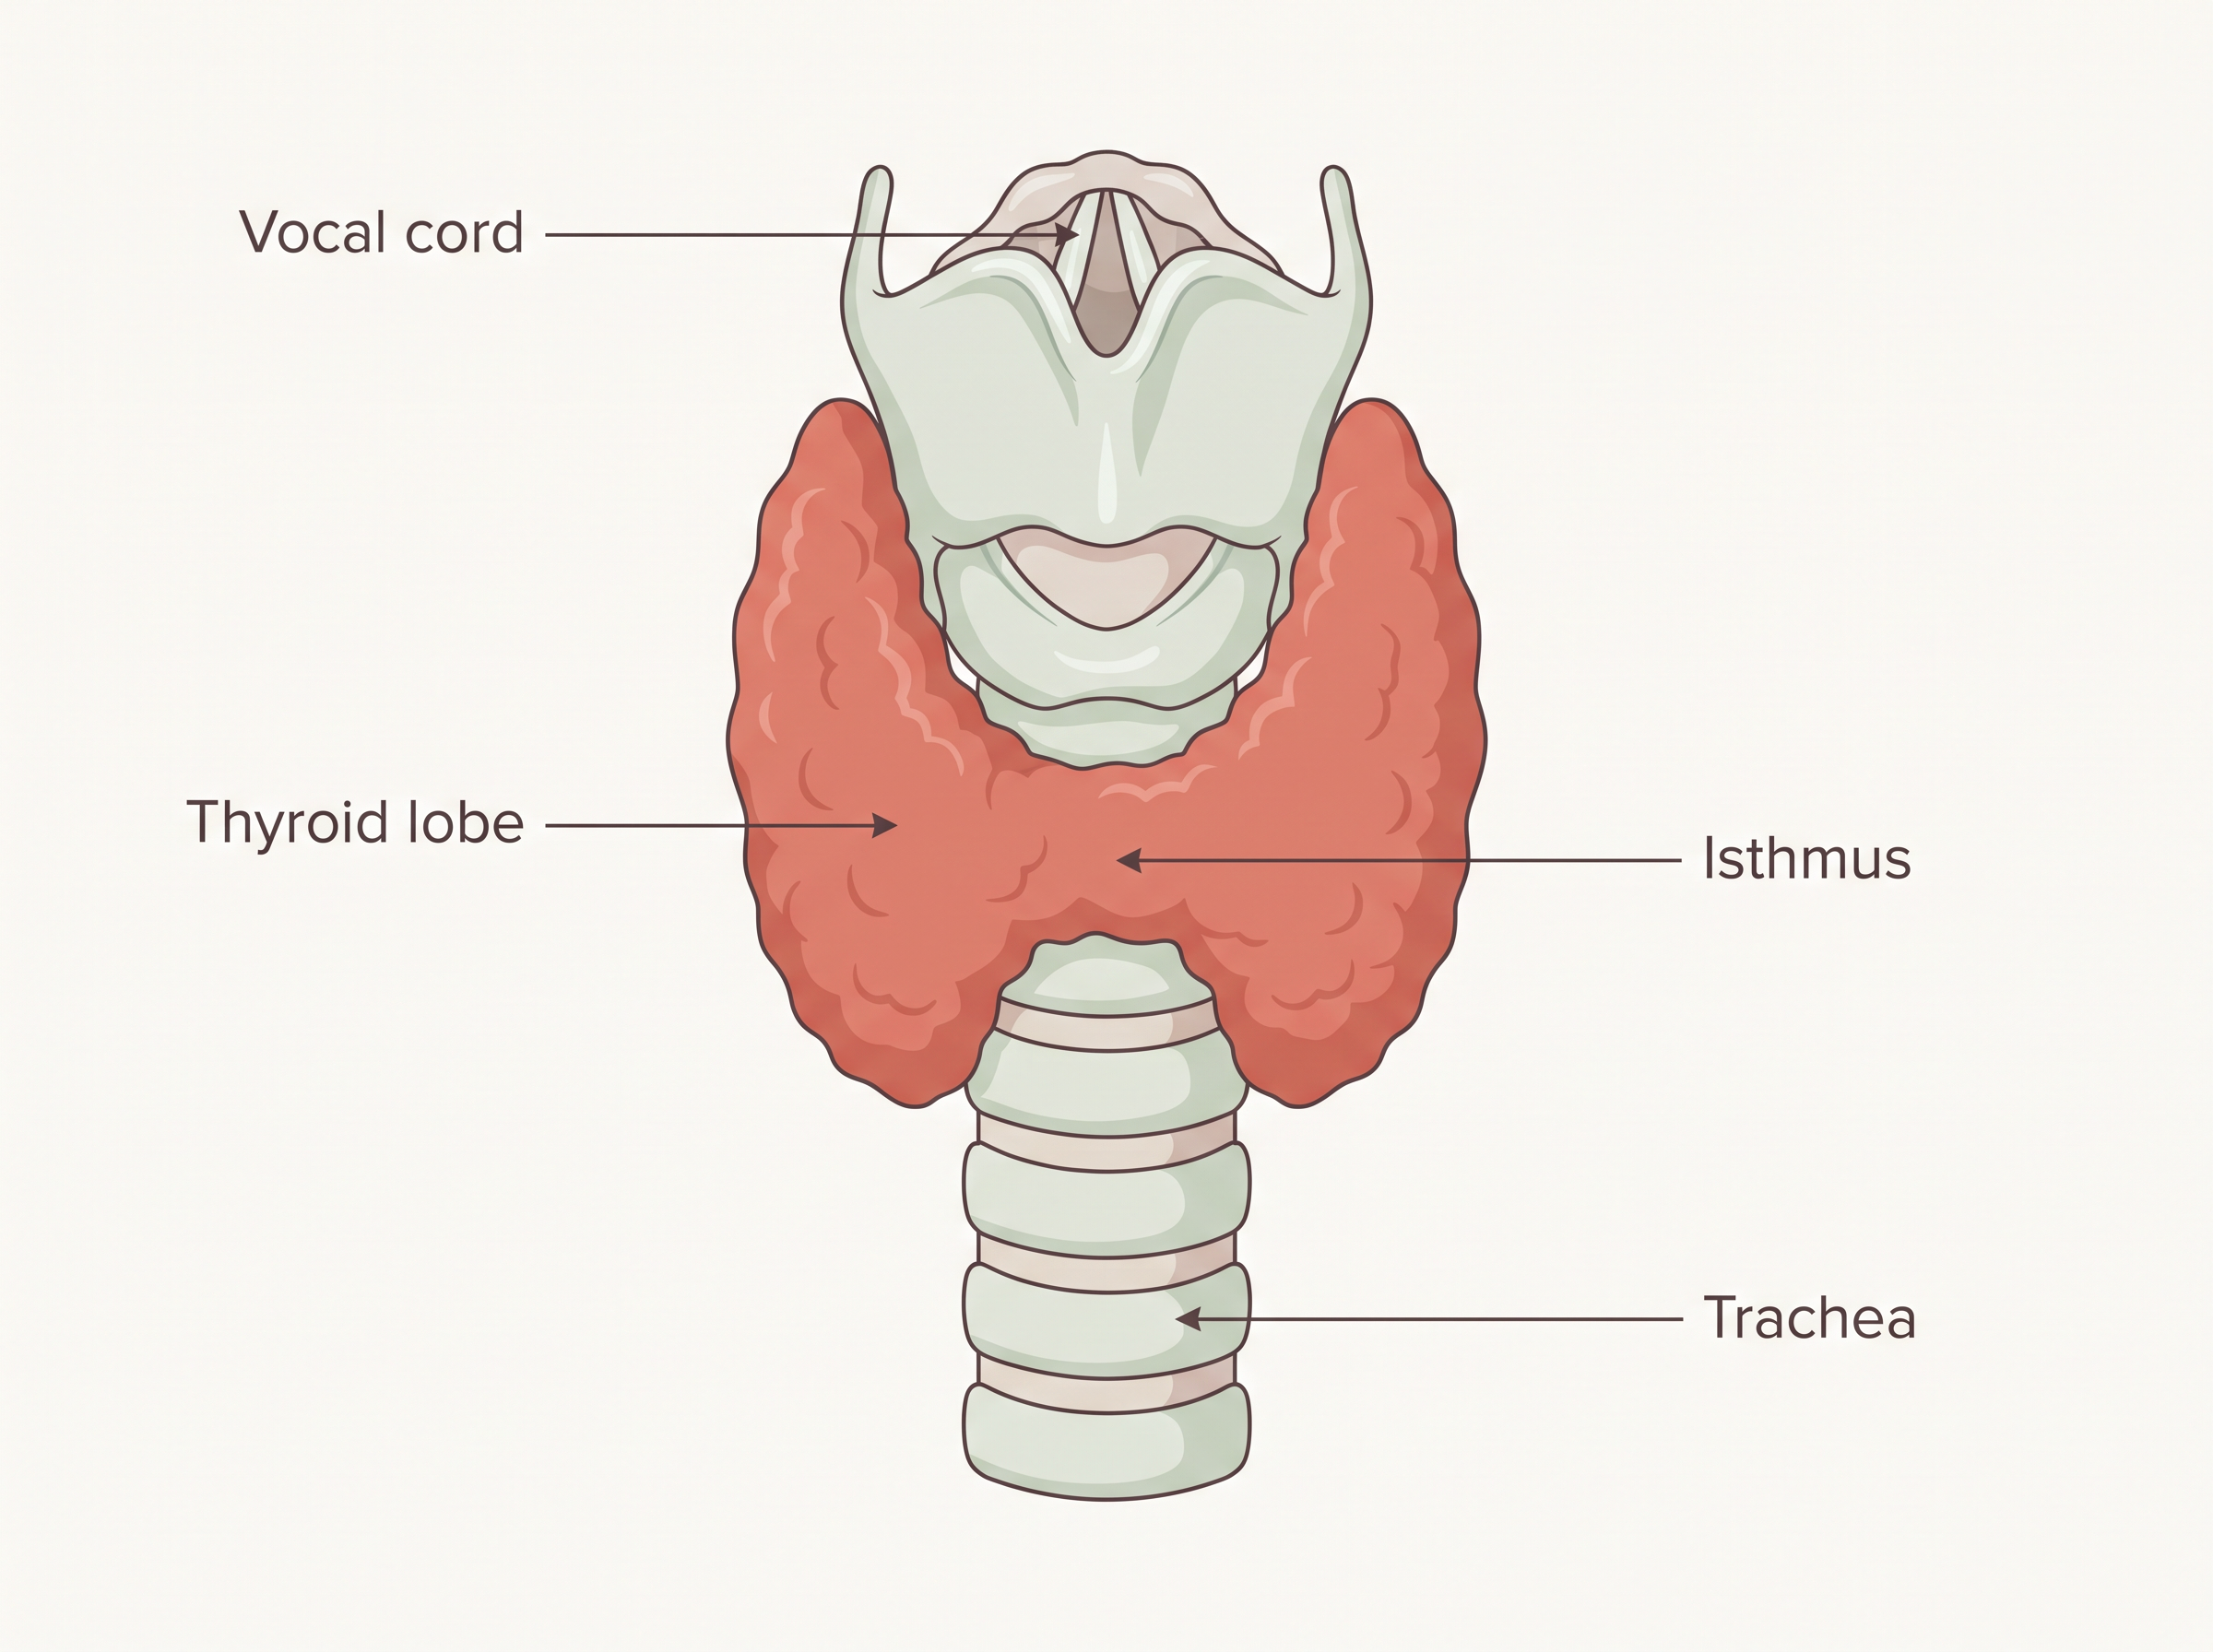
Fig. 19.3(a) – Ventral view of the thyroid gland.
Inside, the thyroid is built from two components: follicles and supporting stromal tissue. Each thyroid follicle is a tiny sac made of follicular cells surrounding a central cavity. It is these follicular cells that actually make the thyroid hormones.
The Thyroid Hormones and the Role of Iodine
The follicular cells synthesise two hormones: tetraiodothyronine, better known as thyroxine (T4), and triiodothyronine (T3). Their names describe their structure — “tetra” means the T4 molecule carries four iodine atoms, while “tri” means T3 carries three.
This is why iodine matters so much: iodine is essential for the normal rate of hormone synthesis in the thyroid. Without enough iodine, the gland simply cannot make enough T3 and T4.
When the Thyroid Makes Too Little: Hypothyroidism
A deficiency of iodine in the diet leads to hypothyroidism (an under-active thyroid) and enlargement of the thyroid gland, commonly called goitre.
Hypothyroidism is especially serious during pregnancy. It causes defective development and maturation of the growing baby, leading to stunted growth (cretinism), mental retardation, low intelligence quotient, abnormal skin, deaf-mutism, and similar problems. In adult women, hypothyroidism may make the menstrual cycle irregular.
When the Thyroid Makes Too Much: Hyperthyroidism
The opposite problem can also occur. Due to cancer of the thyroid gland, or the development of nodules in it, the rate of synthesis and secretion of thyroid hormones may rise to abnormally high levels — a condition called hyperthyroidism, which adversely affects the body’s physiology.
One form of hyperthyroidism is exophthalmic goitre, also called Graves’ disease. It is characterised by enlargement of the thyroid gland, protrusion of the eyeballs, an increased basal metabolic rate, and weight loss.
What Thyroid Hormones Do in a Healthy Body
In normal amounts, the thyroid hormones are essential regulators of the body’s chemistry. They play an important role in regulating the basal metabolic rate (BMR) — the baseline rate at which the body uses energy at rest. They also support the process of red blood cell formation.
Beyond this, thyroid hormones control the metabolism of carbohydrates, proteins, and fats, and they influence the maintenance of water and electrolyte balance in the body.
Finally, the thyroid gland has a second, separate job. It also secretes a protein hormone called thyrocalcitonin (TCT), which regulates the blood calcium levels by lowering them.
19.2.5 Parathyroid Gland
In humans there are four parathyroid glands, located on the back (dorsal) side of the thyroid gland — one pair embedded in each of the two thyroid lobes (Fig. 19.3b). Although they sit on the thyroid, they are entirely separate glands with a completely different job.
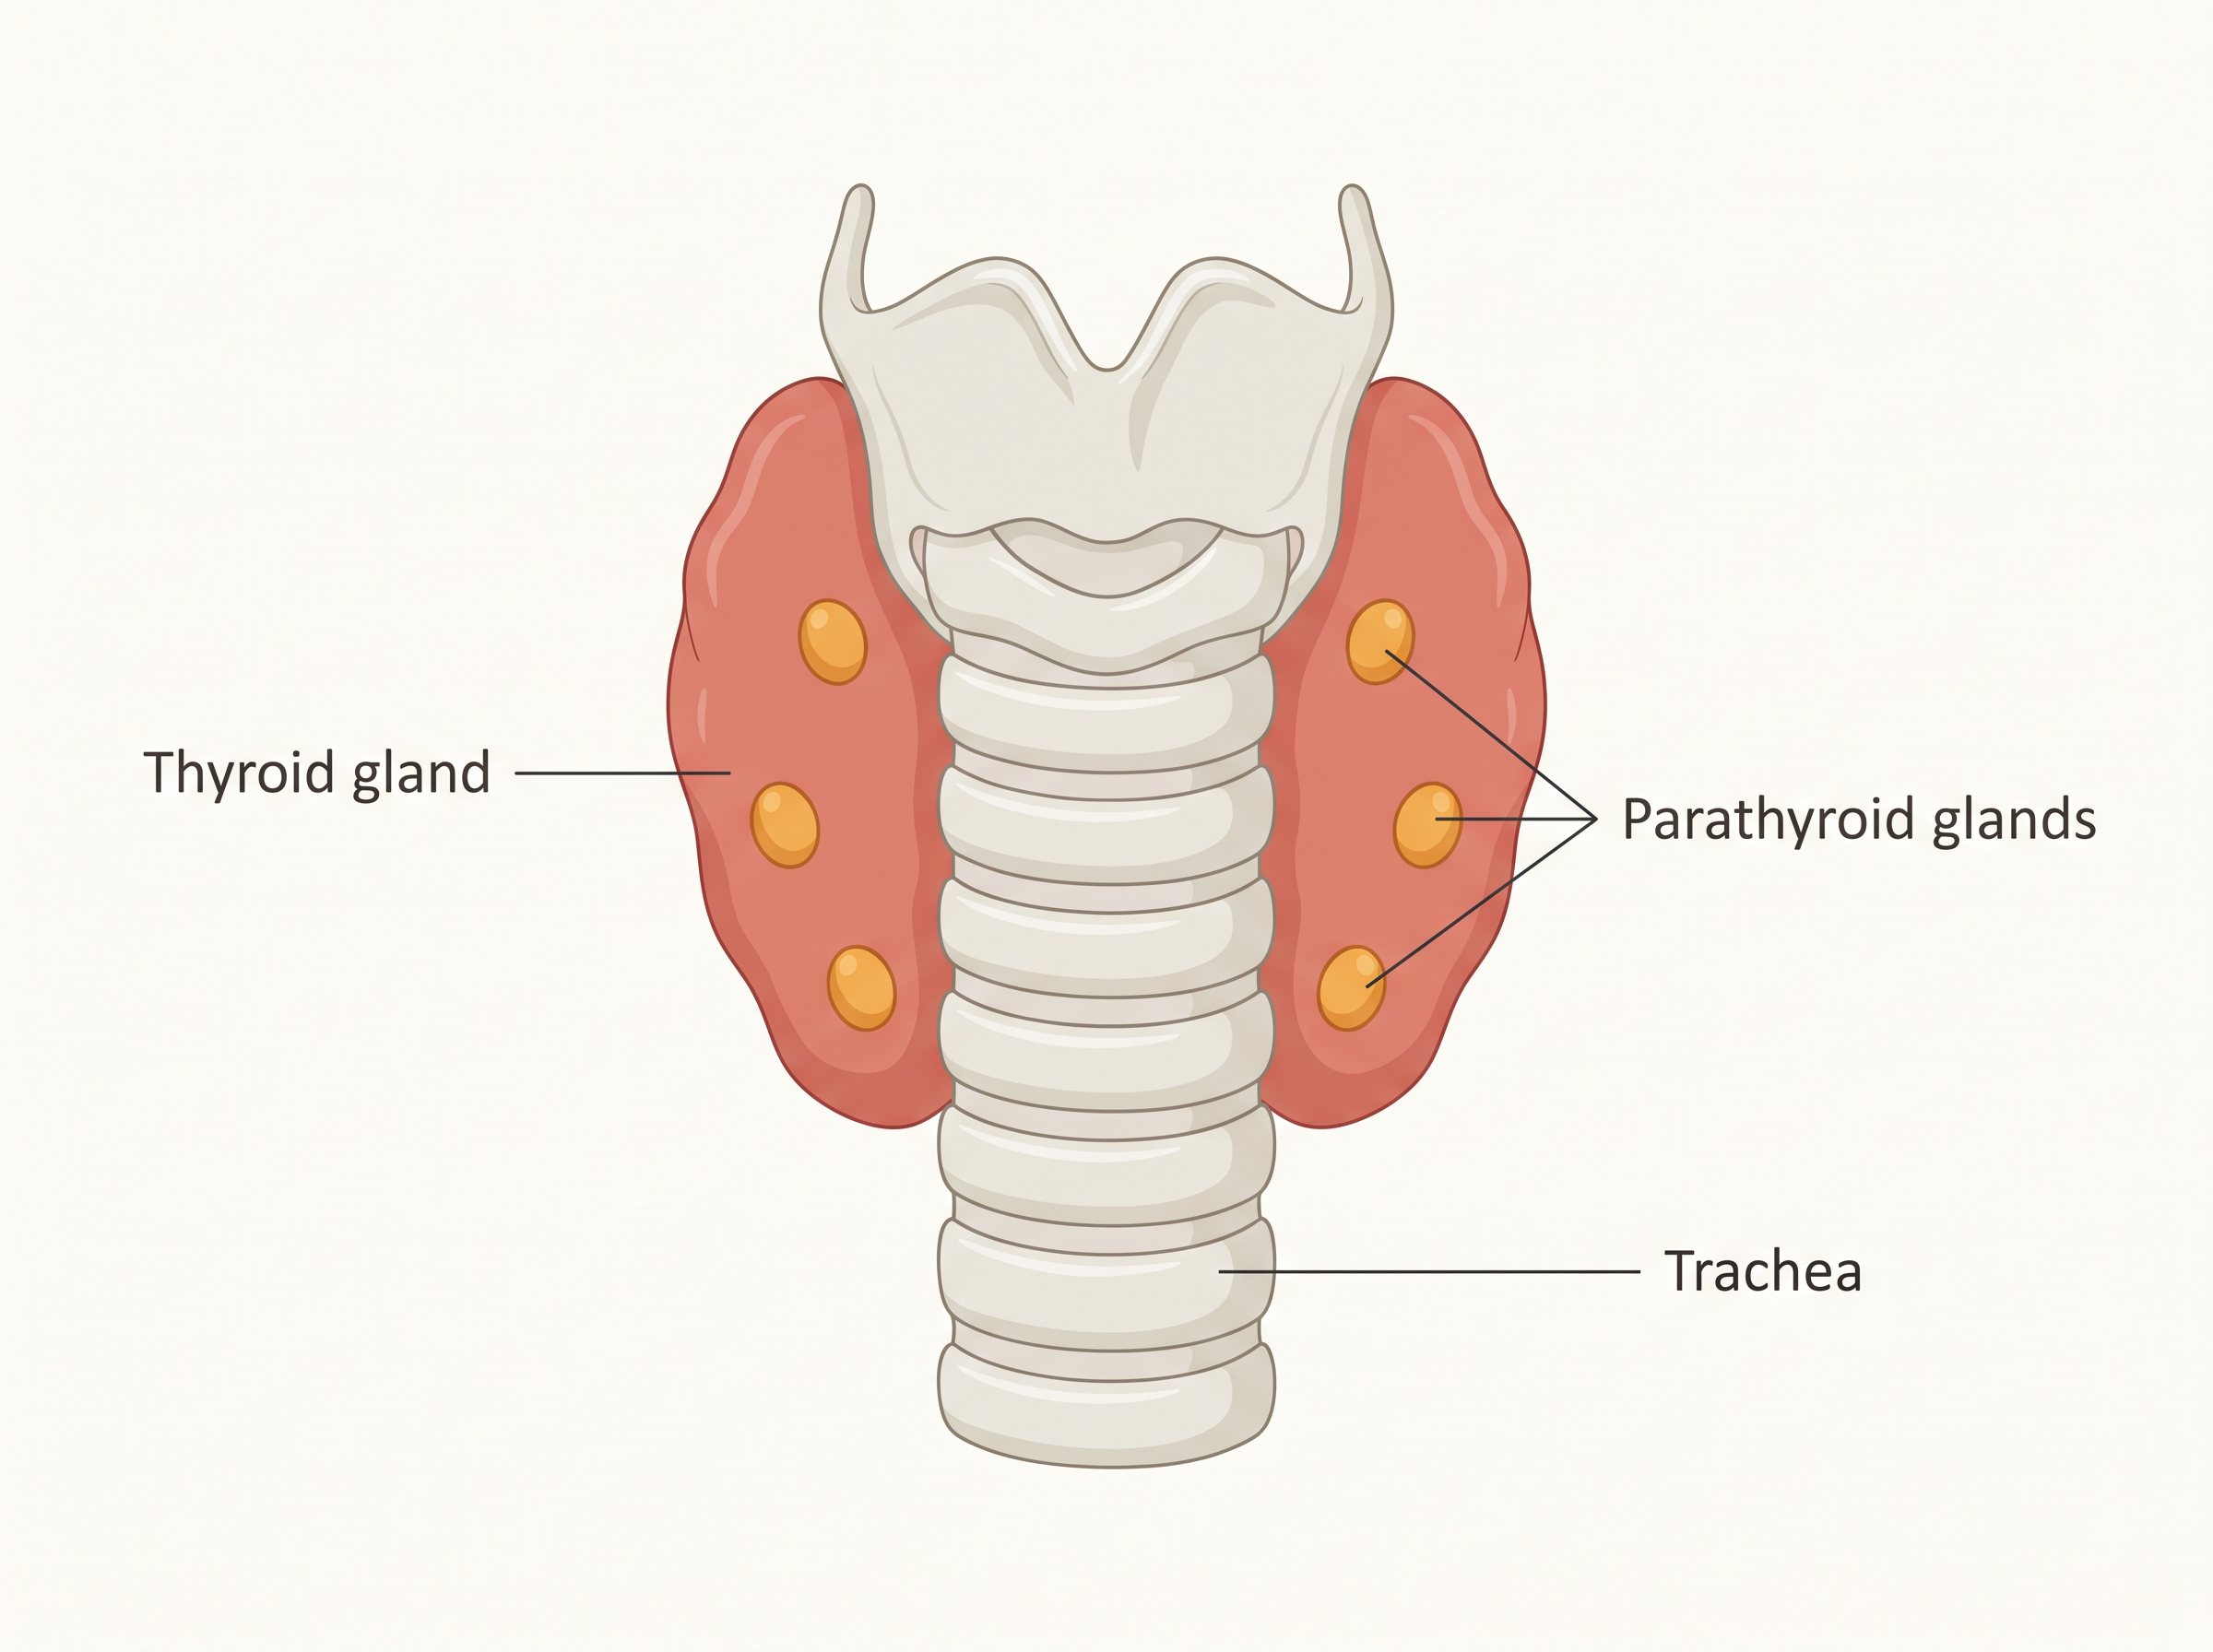
Fig. 19.3(b) – Dorsal view showing the parathyroid glands.
The parathyroid glands secrete a peptide (protein-based) hormone called parathyroid hormone (PTH). The secretion of PTH is not controlled by the pituitary; instead, it is regulated directly by the circulating levels of calcium ions (\(Ca^{2+}\)) in the blood. When blood calcium falls, the parathyroids release more PTH.
How PTH Raises Blood Calcium
PTH increases the \(Ca^{2+}\) level in the blood, and it does so from three directions at once. First, PTH acts on the bones and stimulates bone resorption — the dissolution or demineralisation of bone, which releases stored calcium into the blood. Second, PTH stimulates the reabsorption of \(Ca^{2+}\) by the renal tubules of the kidney, so less calcium is lost in urine. Third, PTH increases the absorption of \(Ca^{2+}\) from digested food in the gut. This combined action is summarised in FC 19.3.
Flowchart
FC 19.3 – Calcium control by PTH: blood \(Ca^{2+}\) falls → parathyroid glands sense it → secrete PTH → three actions (bone resorption ↑ ; renal reabsorption of \(Ca^{2+}\) ↑ ; intestinal absorption of \(Ca^{2+}\) ↑) → blood \(Ca^{2+}\) rises → returns to normal level.
Because it pushes blood calcium up, PTH is described as a hypercalcemic hormone — that is, a hormone that increases the blood \(Ca^{2+}\) level.
Working alongside thyrocalcitonin (TCT), which lowers blood calcium, PTH plays a significant role in keeping the body’s calcium balance steady.
19.2.6 Thymus
The thymus is a lobular (lobed) gland located in the chest, between the two lungs and behind the sternum (breastbone), lying on the ventral side of the aorta. This position, tucked close to the heart’s great vessel, places it right at the crossroads of the circulation — fitting for a gland that helps train the body’s defences.
The thymus plays a major role in the development of the immune system. It does this by secreting peptide hormones called thymosins.
Thymosins have two main immune roles. First, they play a major role in the differentiation (maturation into specialised cells) of T-lymphocytes, a type of white blood cell that provides cell-mediated immunity — defence carried out directly by cells. Second, thymosins also promote the production of antibodies, which provide humoral immunity — defence carried out by antibodies dissolved in body fluids.
An important feature of the thymus is that it does not stay at full strength for life. The thymus degenerates (shrinks and breaks down) in old individuals, resulting in decreased production of thymosins. As a result, the immune responses of old persons become weak.
19.2.7 Adrenal Gland
Structure: A Gland with Two Parts
The body has one pair of adrenal glands, one sitting like a cap on top of each kidney (Fig. 19.4a). Each adrenal gland is really two glands in one, because it is made of two different types of tissue. The centrally located tissue is called the adrenal medulla, and surrounding it on the outside lies the adrenal cortex (Fig. 19.4b).
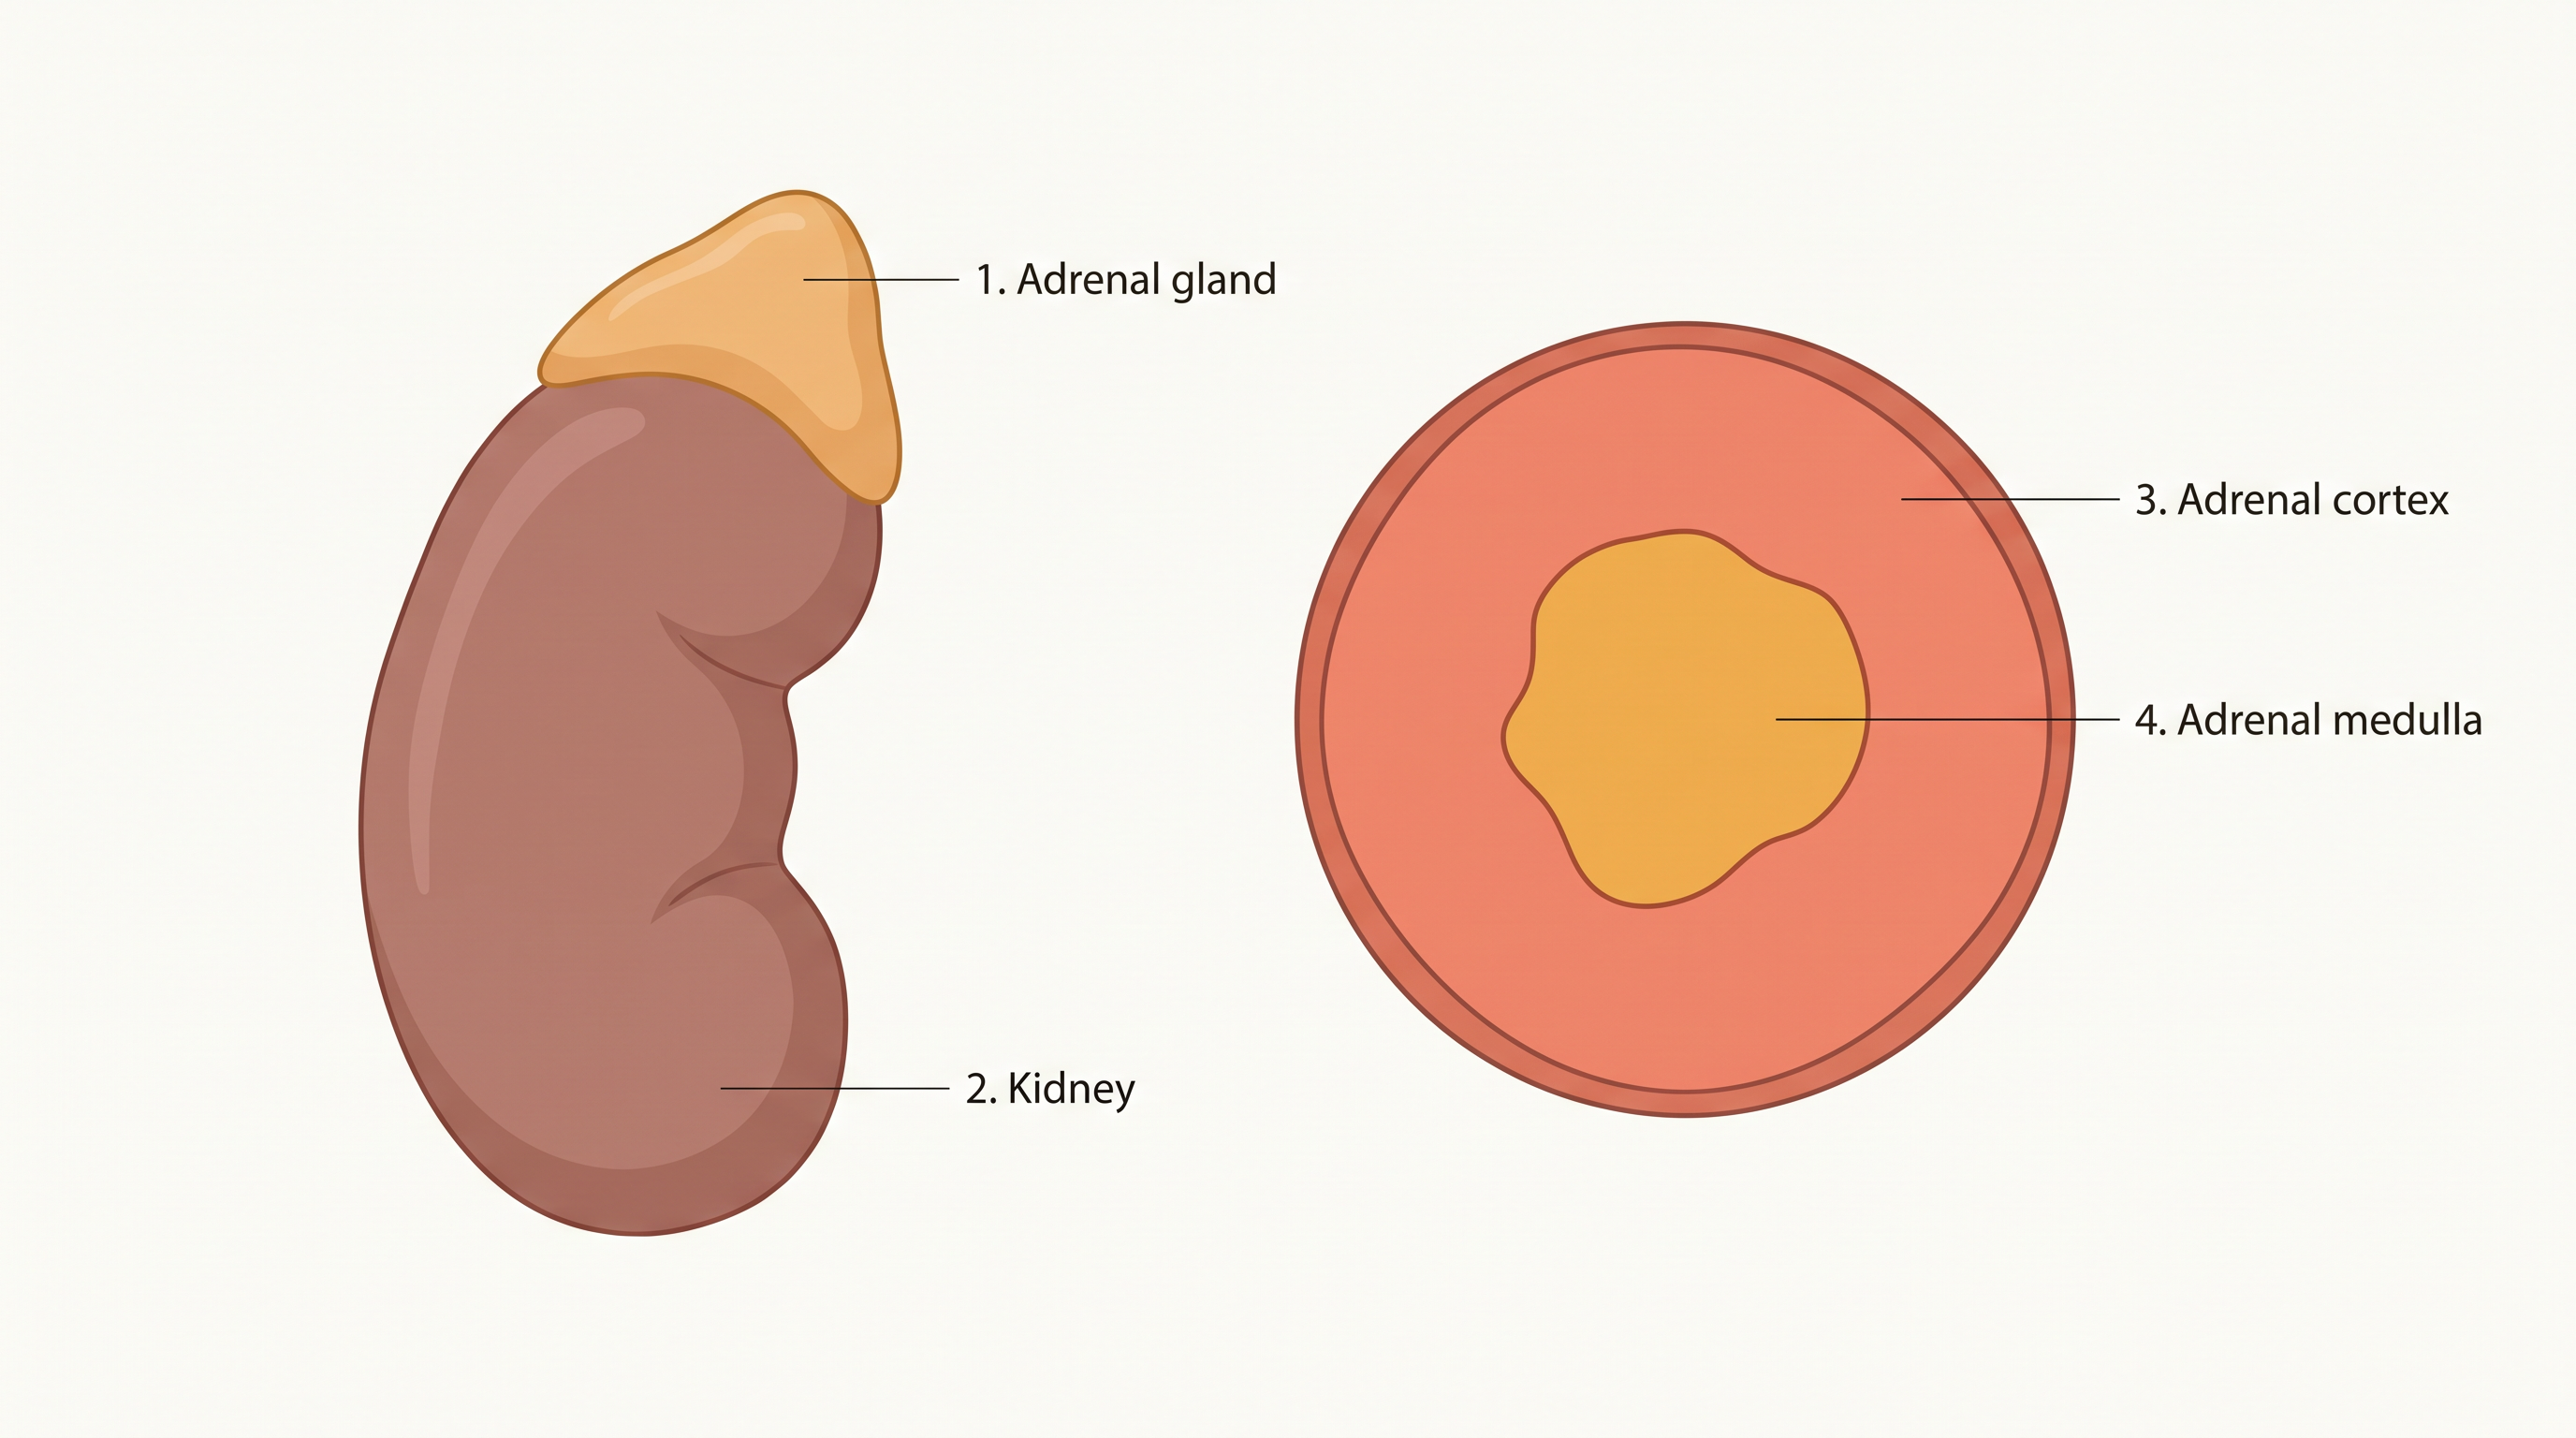
Fig. 19.4 – The adrenal gland: (a) location on kidney and (b) cross-section.
These two parts release completely different kinds of hormones, so it helps to keep them apart from the very start.
Before looking at what each part makes, note one important disorder linked to the cortex: underproduction of hormones by the adrenal cortex alters carbohydrate metabolism, causing acute weakness and fatigue, leading to a disease called Addison’s disease.
The Adrenal Medulla: Hormones of “Fight or Flight”
The adrenal medulla secretes two hormones — adrenaline (also called epinephrine) and noradrenaline (also called norepinephrine). Together these are commonly called catecholamines.
Catecholamines are rapidly secreted in response to stress of any kind and during emergency situations, which is why they are called emergency hormones or the hormones of “Fight or Flight.” Their job is to prepare the body, within seconds, for sudden and intense physical action.
Their effects are exactly what a body facing danger needs. They increase alertness, cause pupilary dilation (widening of the pupils), piloerection (raising of hairs), and sweating. Both hormones increase the heartbeat, the strength of heart contraction, and the rate of respiration — pushing more oxygen-rich blood to the muscles. Catecholamines also stimulate the breakdown of glycogen, resulting in an increased concentration of glucose in the blood for quick energy, and in addition they stimulate the breakdown of lipids and proteins to make still more fuel available.
The Adrenal Cortex: The Corticoids
The adrenal cortex can be divided into three layers: the zona reticularis (inner layer), the zona fasciculata (middle layer), and the zona glomerulosa (outer layer). The cortex secretes many hormones, which are commonly called corticoids.
The corticoids that are involved in carbohydrate metabolism are called glucocorticoids; in our body, cortisol is the main glucocorticoid. The corticoids that regulate the balance of water and electrolytes are called mineralocorticoids; aldosterone is the main mineralocorticoid in our body.
What the Corticoids Do
Glucocorticoids stimulate gluconeogenesis (the making of new glucose from non-carbohydrate sources), lipolysis (breakdown of fats), and proteolysis (breakdown of proteins), and they inhibit the cellular uptake and utilisation of amino acids. Cortisol is also involved in maintaining the cardio-vascular system and the kidney functions. Glucocorticoids, particularly cortisol, produce anti-inflammatory reactions and suppress the immune response, and cortisol stimulates RBC (red blood cell) production.
Aldosterone acts mainly at the renal tubules, where it stimulates the reabsorption of \(Na^+\) (sodium ions) and water, and the excretion of \(K^+\) (potassium ions) and phosphate ions. In this way, aldosterone helps maintain electrolyte balance, body fluid volume, osmotic pressure, and blood pressure.
Finally, small amounts of androgenic steroids are also secreted by the adrenal cortex. These play a role in the growth of axial hair, pubic hair, and facial hair during puberty.
19.2.8 Pancreas
A Gland with Two Roles
The pancreas is a composite gland (Fig. 19.1), meaning it works as both an exocrine and an endocrine gland at the same time. As you saw in Section 19.1, an exocrine gland releases its product through a duct — the pancreas does this by pouring digestive juice into the intestine. But scattered within it are patches of endocrine tissue that release hormones straight into the blood.
The endocrine part of the pancreas consists of the ‘Islets of Langerhans’. There are about 1 to 2 million Islets of Langerhans in a normal human pancreas, yet together they make up only 1 to 2 per cent of the total pancreatic tissue — a tiny fraction with an enormous influence.
Each islet contains two main types of cells: α-cells (alpha cells) and β-cells (beta cells). The α-cells secrete a hormone called glucagon, while the β-cells secrete insulin. These two hormones have opposite effects, and between them they keep blood sugar under control.
Glucagon: The Hormone that Raises Blood Sugar
Glucagon is a peptide hormone that plays an important role in maintaining normal blood glucose levels — specifically, in raising them when they fall too low.
Glucagon acts mainly on the liver cells (hepatocytes). There it stimulates glycogenolysis, the breakdown of stored glycogen back into glucose, which raises the blood sugar level (a state called hyperglycemia). It also stimulates gluconeogenesis (the making of fresh glucose), which further adds to blood sugar, and it reduces the cellular uptake and utilisation of glucose so that more stays in the blood. For all these reasons, glucagon is called a hyperglycemic hormone.
Insulin: The Hormone that Lowers Blood Sugar
Insulin is also a peptide hormone, and it plays a major role in the regulation of glucose homeostasis — the steady control of blood glucose. Keeping this level steady matters greatly: the brain relies on a constant supply of glucose for energy, so blood sugar must not swing too low, while sugar left too high for too long slowly damages the body’s tissues.
Insulin acts mainly on hepatocytes and adipocytes (the cells of adipose, or fat, tissue), and it enhances the cellular uptake and utilisation of glucose. As a result, glucose moves rapidly out of the blood and into these cells, so the blood glucose level falls (a state called hypoglycemia). Insulin also stimulates the conversion of glucose to glycogen (glycogenesis) inside the target cells, storing the sugar away for later.
Because insulin lowers blood sugar and glucagon raises it, glucose homeostasis in the blood is maintained jointly by the two hormones working against each other. This balance is shown in FC 19.4.
Flowchart
FC 19.4 – Joint control of blood glucose: after a meal, blood glucose rises → β-cells release insulin → glucose uptake by cells ↑ and glycogenesis ↑ → blood glucose falls to normal. During fasting, blood glucose falls → α-cells release glucagon → glycogenolysis ↑ and gluconeogenesis ↑ → blood glucose rises to normal. The cycle keeps returning blood glucose to its set level.
When Control Fails: Diabetes Mellitus
If blood sugar stays high for a long time, the result is a serious disorder. Prolonged hyperglycemia leads to a complex disorder called diabetes mellitus. It is associated with the loss of glucose through the urine and the formation of harmful compounds known as ketone bodies. Diabetic patients are successfully treated with insulin therapy.
19.2.9 Testis
Males have a pair of testes (singular: testis), held in a pouch of skin called the scrotal sac, which lies outside the abdomen (see Fig. 19.1). Keeping the testes outside the body holds them slightly cooler than the core temperature, which is important for healthy sperm formation.
The testis performs dual functions. It is a primary sex organ — the site where sperm are made — and it is also an endocrine gland that secretes hormones.
Inside the Testis
The testis is composed of seminiferous tubules and the stromal or interstitial tissue that lies between them. Sperm are produced inside the seminiferous tubules. In the intertubular spaces (between the tubules) are the Leydig cells, also called interstitial cells. These Leydig cells produce a group of hormones called androgens, mainly testosterone.
What Androgens Do
Androgens are responsible for shaping and maintaining the male body. They regulate the development, maturation, and functioning of the male accessory sex organs — such as the epididymis, vas deferens, seminal vesicles, prostate gland, and urethra.
They also drive the male features that appear at puberty: androgens stimulate muscular growth, the growth of facial and axillary (underarm) hair, greater aggressiveness, and a lowering (deepening) of the pitch of the voice.
Beyond these, androgens play a major stimulatory role in spermatogenesis, the formation of spermatozoa (sperm). They act on the central neural system and influence male sexual behaviour (libido). Finally, androgens produce anabolic (building-up, or synthetic) effects on protein and carbohydrate metabolism, helping to build body tissue.
19.2.10 Ovary
Females have a pair of ovaries located in the abdomen (Fig. 19.1). Like the testis in males, the ovary has a dual role.
As the primary female sex organ, the ovary produces one ovum (egg) during each menstrual cycle. As an endocrine gland, it also produces two groups of steroid hormones — estrogen and progesterone.
Where the Ovarian Hormones Come From
The ovary is composed of ovarian follicles and stromal tissue. Interestingly, its two hormones come from two different stages of the same structure.
Estrogen is synthesised and secreted mainly by the growing ovarian follicles. After ovulation (the release of the ovum), the ruptured follicle left behind is converted into a structure called the corpus luteum, which then secretes mainly progesterone. This changeover is shown in FC 19.5.
Flowchart
FC 19.5 – Ovarian hormone sources across the cycle: growing ovarian follicle (secretes estrogen) → ovulation (ovum released) → ruptured follicle becomes the corpus luteum (secretes progesterone).
What Estrogen Does
Estrogens produce wide-ranging actions. They stimulate the growth and activities of the female secondary sex organs and the development of the growing ovarian follicles. They bring about the appearance of the female secondary sex characters (for example, a high pitch of voice) and drive mammary gland (breast) development. Estrogens also regulate female sexual behaviour.
What Progesterone Does
Progesterone is chiefly the hormone that supports pregnancy, preparing and maintaining the body to carry a developing baby. Progesterone also acts on the mammary glands, where it stimulates the formation of alveoli — the sac-like structures that store milk — and promotes milk secretion.
19.3 Hormones of Heart, Kidney and Gastrointestinal Tract
By now you know the main endocrine glands and their hormones. But as noted earlier, hormones are also secreted by some tissues that are not endocrine glands at all — organs whose main jobs are something else entirely. This is exactly the kind of molecule that the broader, modern definition of a hormone (Section 19.1) was meant to include.
Hormones from the Heart
The atrial wall of the heart secretes a very important peptide hormone called atrial natriuretic factor (ANF), whose job is to decrease blood pressure. When blood pressure rises too high, ANF is secreted; it causes dilation (widening) of the blood vessels, and this widening reduces the blood pressure. The response is summarised in FC 19.6.
Flowchart
FC 19.6 – ANF control of blood pressure: blood pressure rises → atrial wall of the heart secretes ANF → blood vessels dilate (widen) → blood pressure falls back toward normal.
Hormones from the Kidney
The kidney, too, doubles as a source of hormones. Its juxtaglomerular cells produce a peptide hormone called erythropoietin, which stimulates erythropoiesis — the formation of red blood cells (RBCs).
Hormones from the Gastrointestinal Tract
Endocrine cells scattered through different parts of the gastro-intestinal (GI) tract secrete four major peptide hormones: gastrin, secretin, cholecystokinin (CCK), and gastric inhibitory peptide (GIP). Each one fine-tunes a different step of digestion.
Gastrin acts on the gastric glands of the stomach and stimulates the secretion of hydrochloric acid (HCl) and pepsinogen. Secretin acts on the exocrine pancreas and stimulates the secretion of water and bicarbonate ions. CCK acts on both the pancreas and the gall bladder, stimulating the secretion of pancreatic enzymes and bile juice, respectively. GIP works in the opposite direction — it inhibits gastric secretion and motility (the movement of the stomach).
Growth Factors
Finally, several other non-endocrine tissues secrete hormones called growth factors. These factors are essential for the normal growth of tissues and for their repair and regeneration after damage.
19.4 Mechanism of Hormone Action
A hormone travels in the blood and reaches almost every cell, yet it acts only on certain cells. How? The answer lies in receptors.
Hormones produce their effects on target tissues by binding to specific proteins called hormone receptors, which are located in the target tissues only. A cell responds to a hormone only if it carries the matching receptor.
There are two places these receptors can sit. Receptors present on the cell membrane of the target cell are called membrane-bound receptors. Receptors present inside the target cell are called intracellular receptors, and these are mostly nuclear receptors, found in the nucleus.
When a hormone binds to its receptor, the two join to form a hormone-receptor complex (Fig. 19.5 a, b). Crucially, each receptor is specific to one hormone only — this is why receptors are said to be specific. It is this specificity that decides which cells a hormone can affect.
Once formed, the hormone-receptor complex leads to certain biochemical changes in the target tissue. In this way, the target tissue’s metabolism — and hence the body’s physiological functions — are regulated by hormones.
Classifying Hormones by Chemical Nature
On the basis of their chemical nature, hormones can be divided into four groups: (i) peptide, polypeptide, and protein hormones (e.g., insulin, glucagon, pituitary hormones, hypothalamic hormones); (ii) steroids (e.g., cortisol, testosterone, estradiol, and progesterone); (iii) iodothyronines (the thyroid hormones); (iv) amino-acid derivatives (e.g., epinephrine).
Two Ways Hormones Act
This chemical difference matters, because it decides how a hormone delivers its message.
Hormones that interact with membrane-bound receptors normally do not enter the target cell. Instead, they trigger the cell to generate second messengers — such as cyclic AMP, \(IP_3\), or \(Ca^{2+}\) — inside the cell, and these second messengers in turn regulate cellular metabolism (Fig. 19.5a).
Hormones that interact with intracellular receptors — for example, the steroid hormones and iodothyronines — act differently. They mostly regulate gene expression or chromosome function, by the interaction of the hormone-receptor complex with the genome (the cell’s DNA) (Fig. 19.5b). The cumulative biochemical actions that follow result in physiological and developmental effects.
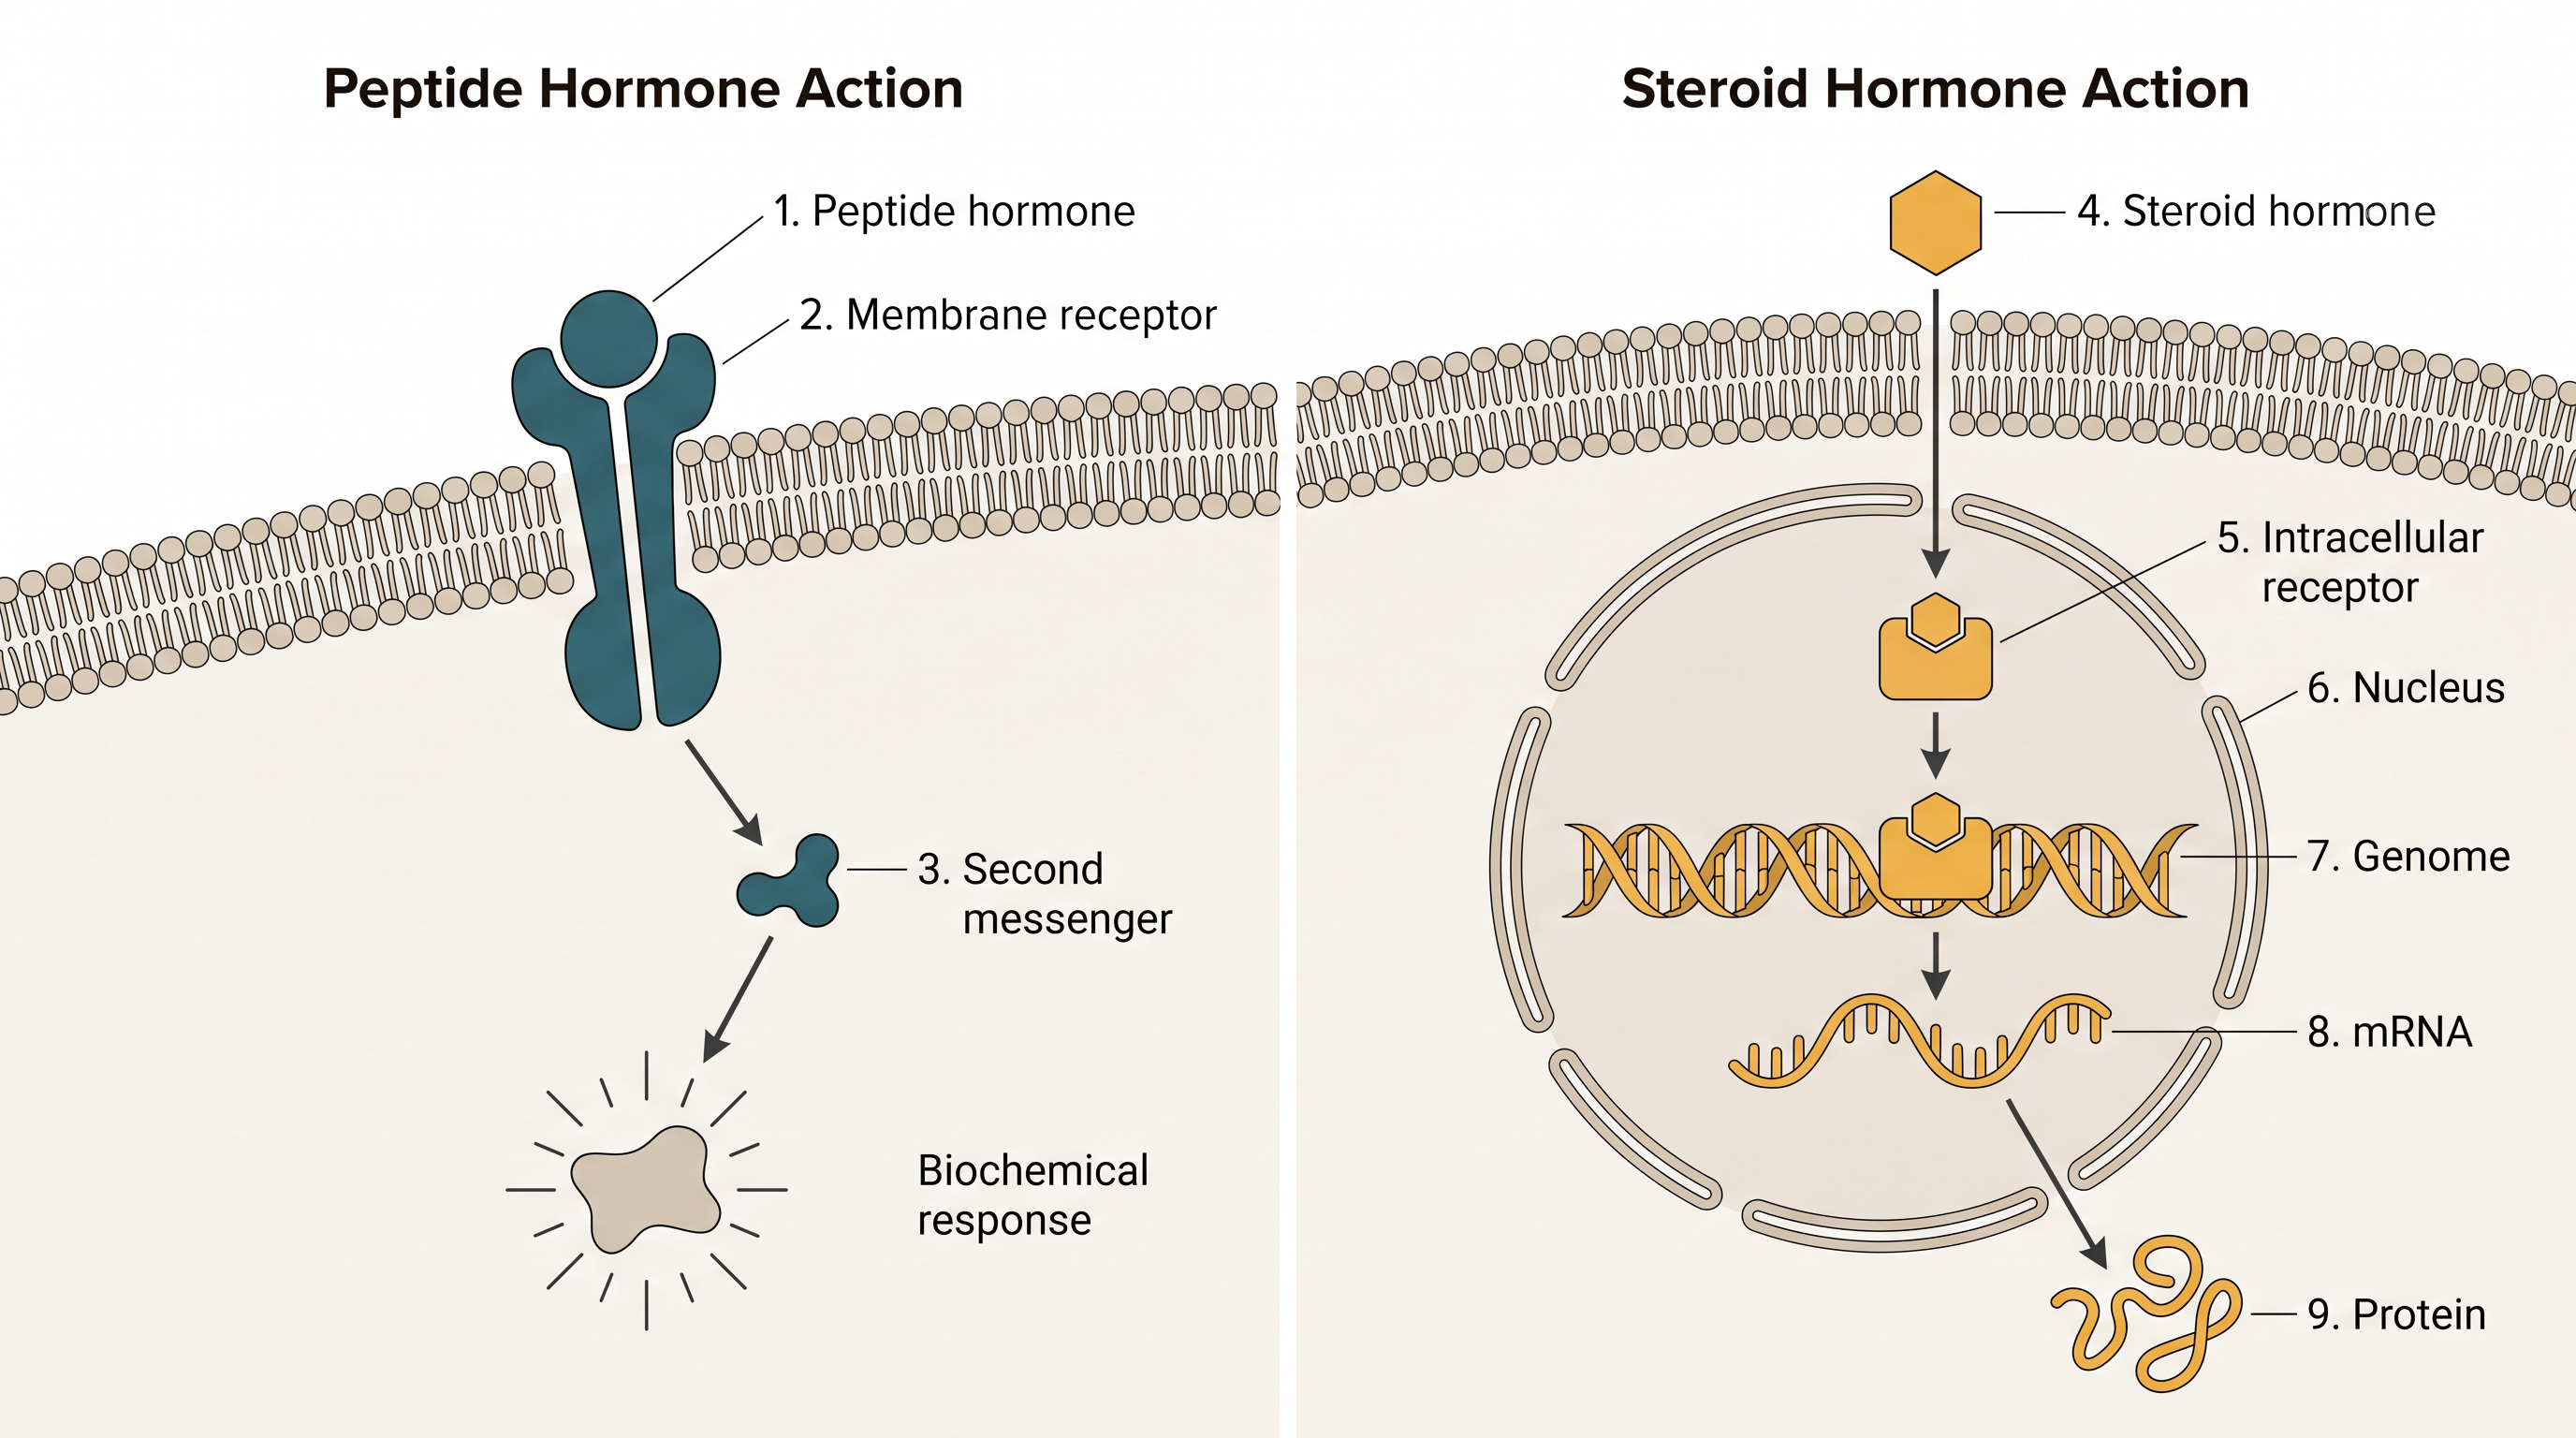
Fig. 19.5 – Mechanism of hormone action: (a) membrane-bound and (b) intracellular receptors.
19.5 Summary
Hormones are special chemicals that provide chemical coordination, integration, and regulation in the human body. They regulate the metabolism, growth, and development of our organs, the endocrine glands, and certain cells.
The endocrine system is made up of the hypothalamus, pituitary, pineal, thyroid, adrenal, pancreas, parathyroid, thymus, and the gonads (testis and ovary). Some other organs — such as the gastrointestinal tract, kidney, and heart — also produce hormones.
Flowchart
FC 19.7 – Central control axis of the endocrine system: hypothalamus (releasing / inhibiting hormones) → pituitary → peripheral endocrine glands (thyroid, adrenal cortex, gonads, etc.) → their hormones → target tissues → physiological effects.
The pituitary gland has three major parts: pars distalis, pars intermedia, and pars nervosa. The pars distalis produces six trophic hormones; the pars intermedia secretes only one hormone; and the pars nervosa (neurohypophysis) secretes two hormones. Pituitary hormones regulate the growth and development of body (somatic) tissues and the activities of the other (peripheral) endocrine glands.
The pineal gland secretes melatonin, which regulates the 24-hour (diurnal) rhythms of the body — for example, the cycles of sleep and wakefulness, and of body temperature.
Thyroid hormones help regulate the basal metabolic rate, the development and maturation of the central neural system, erythropoiesis (red blood cell formation), the metabolism of carbohydrates, proteins, and fats, and the menstrual cycle. A second thyroid hormone, thyrocalcitonin, lowers the level of calcium in the blood.
The parathyroid glands secrete parathyroid hormone (PTH), which raises blood \(Ca^{2+}\) levels and plays a major role in calcium homeostasis.
The thymus secretes thymosins, which help differentiate T-lymphocytes for cell-mediated immunity and also increase antibody production for humoral immunity.
The adrenal gland has a central adrenal medulla and an outer adrenal cortex. The medulla secretes epinephrine and norepinephrine, which increase alertness, pupilary dilation, piloerection, sweating, heart rate, strength of heart contraction, rate of respiration, and the breakdown of glycogen, fats, and proteins (glycogenolysis, lipolysis, proteolysis).
The adrenal cortex secretes glucocorticoids and mineralocorticoids. Glucocorticoids stimulate gluconeogenesis, lipolysis, proteolysis, erythropoiesis, the cardio-vascular system, blood pressure, and the glomerular filtration rate, and they suppress the immune response to reduce inflammation. Mineralocorticoids regulate the body’s water and electrolyte contents.
The endocrine pancreas secretes glucagon and insulin. Glucagon stimulates glycogenolysis and gluconeogenesis, causing hyperglycemia; insulin stimulates cellular glucose uptake, utilisation, and glycogenesis, causing hypoglycemia. Insulin deficiency and/or insulin resistance leads to diabetes mellitus.
The testis secretes androgens, which stimulate the development, maturation, and functions of the male accessory sex organs, the appearance of male secondary sex characters, spermatogenesis, male sexual behaviour, anabolic pathways, and erythropoiesis.
The ovary secretes estrogen and progesterone. Estrogen stimulates the growth and development of the female accessory sex organs and secondary sex characters. Progesterone helps maintain pregnancy and supports mammary gland development and lactation.
The atrial wall of the heart produces atrial natriuretic factor, which lowers blood pressure. The kidney produces erythropoietin, which stimulates erythropoiesis. The gastrointestinal tract secretes gastrin, secretin, cholecystokinin, and gastric inhibitory peptide, which regulate the secretion of digestive juices and help in digestion.
19.6 Points to Ponder
The same word “diabetes” names two very different disorders — diabetes insipidus (a water problem) and diabetes mellitus (a sugar problem). What does this shared name suggest about how diseases were once recognised and named, before their true causes were understood?
Insulin and glucagon push blood sugar in opposite directions. Why might a control system built on two opposing hormones be more reliable than one that relies on a single hormone to both raise and lower a value?
A hormone is carried in the blood to every cell, yet it acts on only a few. If a cell suddenly began making receptors for a hormone it normally ignores, how might its behaviour change — and what might that mean for the body as a whole?
The posterior pituitary releases two hormones that it does not make, while the hypothalamus makes hormones that it hands over rather than releasing into general circulation itself. What advantages might the body gain by separating the place where a hormone is made from the place where it is released?
Steroid hormones act by switching genes on or off inside the nucleus, whereas peptide hormones act through second messengers at the cell surface. Why might steroid hormones tend to produce slower, but longer-lasting, effects than peptide hormones?
Parathyroid hormone and thyrocalcitonin both influence blood calcium, but in opposite directions. Why might the body need the ability to actively both raise and lower calcium, rather than simply storing or releasing it whenever needed?
The thymus shrinks with age, and the immune defences of older people weaken as a result. If it were possible to keep the thymus fully active throughout life, what benefits — and what possible risks — might follow?
19.7 NCERT Questions
Define the following: (a) Exocrine gland (b) Endocrine gland (c) Hormone
Diagrammatically indicate the location of the various endocrine glands in our body.
List the hormones secreted by the following: (a) Hypothalamus (b) Pituitary (c) Thyroid (d) Parathyroid (e) Adrenal (f) Pancreas (g) Testis (h) Ovary (i) Thymus (j) Atrium (k) Kidney (l) G-I Tract
Fill in the blanks (name the target gland of each hormone): (a) Hypothalamic hormones — ______ (b) Thyrotrophin (TSH) — ______ (c) Corticotrophin (ACTH) — ______ (d) Gonadotrophins (LH, FSH) — ______ (e) Melanotrophin (MSH) — ______
Write short notes on the functions of the following hormones: (a) Parathyroid hormone (PTH) (b) Thyroid hormones (c) Thymosins (d) Androgens (e) Estrogens (f) Insulin and Glucagon
Give example(s) of: (a) Hyperglycemic hormone and hypoglycemic hormone (b) Hypercalcemic hormone (c) Gonadotrophic hormones (d) Progestational hormone (e) Blood pressure lowering hormone (f) Androgens and estrogens
Which hormonal deficiency is responsible for the following: (a) Diabetes mellitus (b) Goitre (c) Cretinism
Briefly mention the mechanism of action of FSH.
Match the following:
| Column I | Column II |
|---|---|
| a. T4 | i. Hypothalamus |
| b. PTH | ii. Thyroid |
| c. GnRH | iii. Pituitary |
| d. LH | iv. Parathyroid |
19.8 Check Your Concepts
For the assertion–reason questions (questions 1 to 3), choose one option: (a) Both A and R are true, and R is the correct explanation of A; (b) Both A and R are true, but R is not the correct explanation of A; (c) A is true but R is false; (d) A is false but R is true.
Assertion (A): The posterior pituitary is often said not to be a “true” hormone-synthesising gland. Reason (R): Oxytocin and vasopressin are synthesised by the hypothalamus and are only stored and released by the posterior pituitary.
Assertion (A): A long-term iodine-deficient diet can cause the thyroid gland to enlarge into a goitre. Reason (R): Without enough iodine, the thyroid cannot make sufficient T3 and T4, and the gland grows in an effort to compensate.
Assertion (A): A person with impaired ADH release passes large volumes of dilute urine. Reason (R): ADH normally promotes the reabsorption of water from the distal tubules of the kidney.
Why is the pituitary called the “master gland” even though it is itself controlled by the hypothalamus? Explain.
Explain why steroid hormones and protein (peptide) hormones act on their target cells through different mechanisms.
What would happen to the level of calcium in the blood if all four parathyroid glands were removed? Explain your reasoning.
Predict what would happen to blood glucose regulation if the β-cells of the Islets of Langerhans stopped functioning.
The thymus degenerates with age. Explain why this makes elderly people more vulnerable to infections.
Arrange the following events of the fight-or-flight response in the correct order: (i) glucose is released into the blood; (ii) a frightening event occurs; (iii) the adrenal medulla secretes adrenaline and noradrenaline; (iv) heart rate and breathing rate increase.
Arrange these events of ovarian hormone secretion in the correct sequence: (i) the corpus luteum secretes progesterone; (ii) the growing follicle secretes estrogen; (iii) ovulation releases the ovum; (iv) the ruptured follicle becomes the corpus luteum.
Put the steps of steroid-hormone action in the correct order: (i) the hormone-receptor complex interacts with the genome; (ii) the steroid hormone enters the target cell; (iii) gene expression changes and new proteins are made; (iv) the hormone binds an intracellular receptor.
Match each gland or cell type with the hormone it secretes:
| Column I | Column II |
|---|---|
| a. Pineal gland | i. Thymosins |
| b. Thymus | ii. Melatonin |
| c. α-cells of pancreas | iii. Glucagon |
| d. Adrenal medulla | iv. Adrenaline |
- Match each hormone with its chemical class:
| Column I | Column II |
|---|---|
| a. Insulin | i. Steroid |
| b. Cortisol | ii. Iodothyronine |
| c. Thyroxine (T4) | iii. Peptide / protein |
| d. Epinephrine | iv. Amino-acid derivative |
- Match each condition with its cause:
| Column I | Column II |
|---|---|
| a. Acromegaly | i. Iodine deficiency / low thyroid hormone |
| b. Goitre | ii. Excess growth hormone in adults |
| c. Addison’s disease | iii. Impaired ADH |
| d. Diabetes insipidus | iv. Underproduction of adrenal cortex hormones |
Draw a labelled diagram showing the pituitary gland and its relationship with the hypothalamus. Label the anterior pituitary, the posterior pituitary, the hypothalamic neurons, and the portal circulation.
Draw a section of the adrenal gland and label the adrenal cortex and the adrenal medulla. Name one hormone secreted by each part.
Distinguish between hypothyroidism and hyperthyroidism, giving one named example of each.
Distinguish between cell-mediated immunity and humoral immunity.
A middle-aged patient reports that their rings and shoes no longer fit and that their facial features have coarsened over several years. Which hormone disorder is most likely, and which gland is involved?
A patient with long-term kidney failure develops anaemia (a shortage of red blood cells). Which hormone deficiency explains this, and why?